Related Experiment Video
Updated: Oct 24, 2026
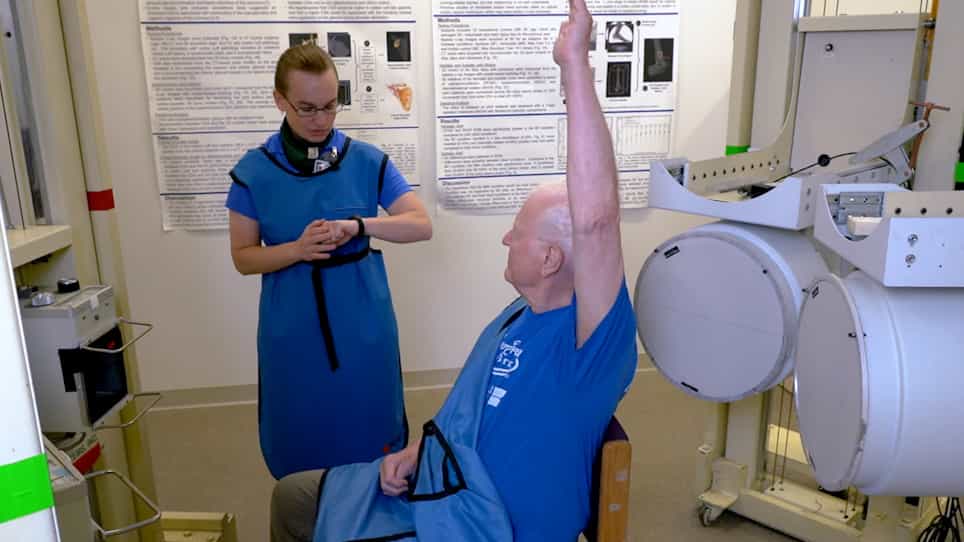
Measuring 3D In-vivo Shoulder Kinematics using Biplanar Videoradiography
Published on: March 12, 2021
Reference-signature projection framework for exercise transcriptomic directionality based on the IAV-DI reference
Anli Zhou1,2, Min Zhang1,2, Cheng Zhang1,2
1Center for Innovation in Sports-Medicine Integration, Capital University of Physical Education and Sports, Beijing, China.

Background:
Exercise is often described as medicine, but exercise and pharmacological interventions cannot be treated as clinically equivalent. This study developed a Reference Signature Projection Framework (RSPF) to evaluate the directional relationship of external disease and exercise transcriptomic responses relative to a predefined disease-treatment reference axis. The empirical analysis in this study was restricted to the IAV-DI reference axis defined by dimethyl itaconate (DI) treatment in the context of influenza A virus (IAV) infection.
Methods:
(1) Reference-signature construction: the IAV-DI reference direction was defined from transcriptional changes between DI-treated and untreated human peripheral blood mononuclear cells in the context of IAV infection. Drug-UP and Drug-DOWN directions were defined according to avg_log2FC, candidate genes were prioritized using random forest Mean Decrease Accuracy (MDA), and the MDA Top 100 was used as the main reference signature. (2) Reference-signature projection: Drug-UP and Drug-DOWN were projected separately onto complete gene-ranking lists for GSE243629 IA versus HC, cardiopulmonary exercise testing (CPX), and Marathon post- versus pre-exercise comparisons, and GSEA was used to calculate NES, nominal p, and FDR. (3) Robustness and supporting evaluation: gene-level similarity, TopN sensitivity, random gene-set negative controls, and pathway-level NES patterns were used to evaluate transcriptomic directionality, robustness, and interpretive boundaries.
Results:
(1) Reference-signature composition: the MDA Top 100 contained 24 Drug-UP and 76 Drug-DOWN genes. (2) External disease-direction evaluation: in GSE243629 IA versus HC, Drug-DOWN was significantly enriched toward the upregulated end (NES = 1.724, FDR = 4.00 × 10⁻⁸), whereas Drug-UP did not reach FDR< 0.05, indicating a clear opposite relationship of the external disease state relative to the IAV-DI reference axis, with statistical support driven mainly by the Drug-DOWN reference gene set. (3) Overall exercise-direction results: neither Drug-UP nor Drug-DOWN reached FDR< 0.05 in CPX or Marathon; therefore, their direction scores were interpreted only as exploratory directional indicators. Gene-level analysis likewise showed a weak overall directional relationship between CPX and IAV-DI. (4) Pathway-level results: selected functional modules showed the same NES sign for IAV-DI and CPX and the opposite sign for Marathon, but none of the CPX pathways reached FDR < 0.05; these results therefore represent only module-specific exploratory directional patterns.
Conclusion:
RSPF provides a computational framework for evaluating transcriptomic directional relationships relative to a predefined disease-treatment reference axis. In the current IAV-DI proof-of-concept analysis, the external influenza disease comparison showed a clear opposite relationship relative to the IAV-DI reference axis, whereas neither CPX nor Marathon showed statistically supported overall IAV-DI directional concordance; exploratory directional patterns were observed only in selected functional modules. Accordingly, the present findings apply only to the IAV-DI reference axis and cannot be generalized to a universal relationship between exercise and pharmacological interventions or used to infer therapeutic equivalence, drug substitution, or shared pharmacological mechanisms.

