Related Experiment Video
Updated: Oct 24, 2026
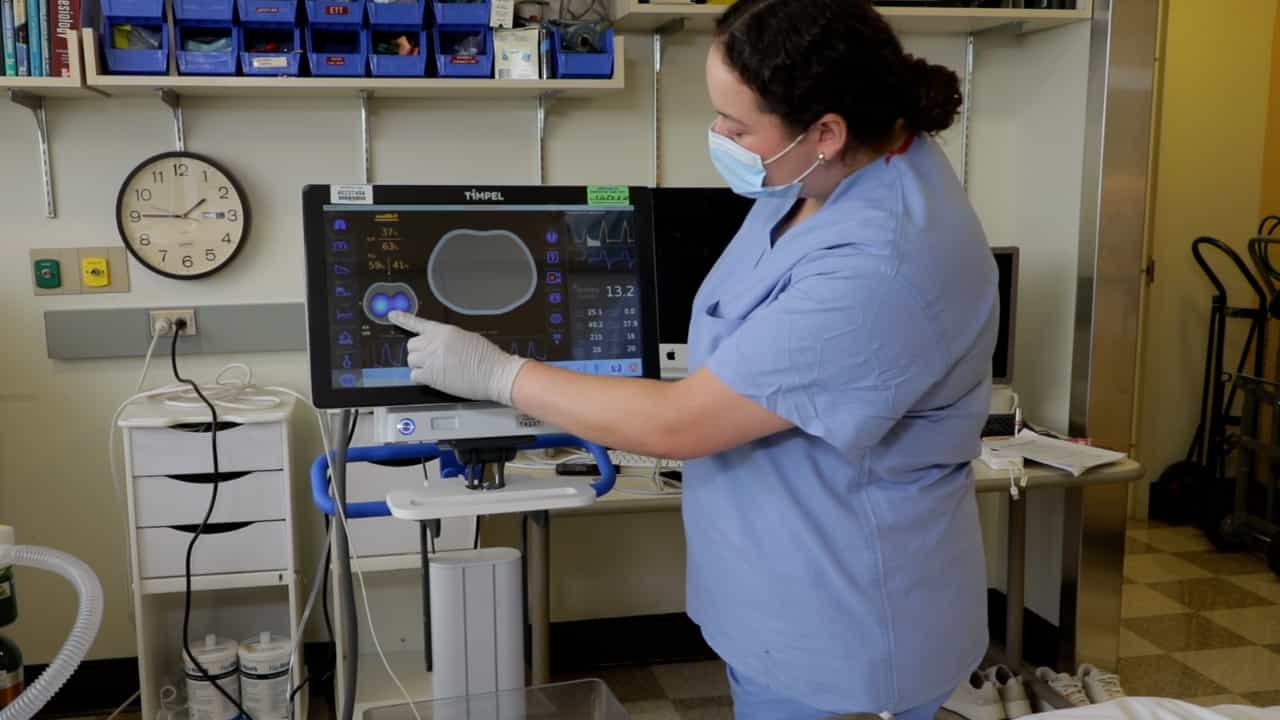
Monitoring Lung Function with Electrical Impedance Tomography in the Intensive Care Unit
Published on: September 6, 2024
Dynamic changes in regional ventilation distribution and end-expiratory lung impedance using electrical impedance
Minjia Wang1, Changyun Zhao1, Zhiheng Hao1
1Department of Critical Care Medicine, Zhejiang Hospital, Hangzhou, Zhejiang, China.

Background:
Accurately assessing the optimal timing for extubation remains a significant challenge in intensive care units (ICUs). The rapid shallow breathing index (RSBI) is widely used but lacks insight into regional lung physiology. This study aimed to characterize dynamic changes in regional ventilation distribution and end-expiratory lung impedance (EELI) using electrical impedance tomography (EIT) during spontaneous breathing trials (SBTs) and to explore their association with weaning and extubation outcomes.
Methods:
In this prospective observational study, 52 mechanically ventilated patients undergoing their first SBT were enrolled. EIT parameters, including the Global Inhomogeneity (GI) index, center of ventilation (COV), ventrodorsal ventilation asymmetry (|ROI V-D|), and changes in EELI (ΔEELI), were recorded at four time points. Weaning failure was defined as SBT failure, or as reintubation or noninvasive ventilation within 48 h after extubation. Extubation failure was defined as reintubation or rescue NIV within 48 h. Logistic models coded 1 = failure and 0 = success.
Results:
SBT failure (n = 19, 36.5%) was associated with progressive deterioration of ventilation, with a significant increase in the GI index (p < 0.001) and a notable spike in |ROI V-D| at T3 (p = 0.005). Extubation failure (n = 9, 27.3% of SBT successes) was associated with a greater cumulative loss of end-expiratory lung volume (ΔEELI T4-T1) compared with the success group (p < 0.001). In secondary exploratory analyses, a combined MLE model of T4 RSBI and T3 GI showed an apparent AUC of 0.923 (95% CI 0.840-0.986) for SBT failure (optimism-corrected AUC: 0.905). A combined model of T4 RSBI and ΔEELI (T4-T1) showed an apparent AUC of 0.875 (95% CI: 0.688-0.988) for extubation failure; with only 9 events, this estimate is hypothesis-generating and requires external validation.
Conclusions:
EIT-derived parameters offer insights into regional ventilation changes during the weaning process. Increased ventilation inhomogeneity and ventrodorsal mismatch are associated with SBT failure, while loss of end-expiratory lung impedance is associated with extubation failure. Adding EIT parameters to RSBI provided exploratory incremental information for discriminating SBT failure and extubation failure in this cohort. These secondary analyses require external validation before any clinical application can be considered.Clinical Trial Registration: https://www.chictr.org.cn, identifier ChiCTR2500108219.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:10
Atelectasis II: Pathophysiology
 01:29
Mechanical Ventilation I: Indication and Settings
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:24
Endotracheal Tube Extubation
Procedure
Extubation removes the endotracheal tube (ETT) from the patient on mechanical ventilation. It requires a well-coordinated, multidisciplinary approach involving physicians, nurses, respiratory therapists, and other healthcare professionals.
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: