Related Experiment Video
Updated: Oct 24, 2026

Optimized Management of Endovascular Treatment for Acute Ischemic Stroke
Published on: January 18, 2018
Dual-phase CTA filling pattern is associated with reperfusion-related complications after mechanical thrombectomy in
Truong Van Le1, Khanh T Ngoc Thach2, Tuyen Trong Nguyen1
1Department of Neurovascular Intervention, Institute of Neurology, 108 Military Central Hospital, Hanoi, Vietnam.

Objective:
To evaluate whether pre-treatment dual-phase computed tomography angiography (CTA) filling patterns are independently associated with reperfusion-related complications after late-window mechanical thrombectomy and whether they provide incremental prognostic value beyond conventional clinical and imaging variables.
Methods:
We conducted a prospective single-center cohort study including 80 consecutive patients with anterior circulation large-vessel occlusion who underwent mechanical thrombectomy within 6-24 h after stroke onset or last known well. Dual-phase CTA filling patterns were classified as good early filling, delayed filling, or persistent poor filling; delayed and persistent poor filling were combined for the primary analyses. The primary outcome was a composite of reperfusion-related complications within 72 h, including hemorrhagic transformation ≥HI2, malignant cerebral edema, or early neurological deterioration. Secondary outcomes were 90-day functional independence and all-cause mortality. Independent predictors were identified using Firth penalized logistic regression. Incremental model performance was evaluated using receiver operating characteristic analysis, bootstrap internal validation, reclassification metrics, and decision-curve analysis.
Results:
Reperfusion-related complications occurred in 28 patients (35%) and were significantly more frequent in patients with delayed or poor filling than in those with good early filling (56% vs. 20%; p < 0.001). Delayed or poor filling independently predicted reperfusion-related complications after adjustment for age, baseline NIHSS score, and ASPECTS (adjusted OR 3.97, 95% CI 1.22-14.10; p = 0.022). Older age was also independently associated with increased risk (adjusted OR 2.14 per 10-year increase, 95% CI 1.24-4.12; p = 0.005), whereas higher ASPECTS was protective (adjusted OR 0.35 per point, 95% CI 0.18-0.61; p < 0.001). The full model incorporating dual-phase CTA achieved excellent discrimination (AUC 0.895; optimism-corrected AUC 0.867). Addition of the dual-phase CTA filling pattern improved patient risk reclassification, although the increase in discrimination beyond the clinical-plus-ASPECTS model was not statistically significant. Patients with delayed or poor filling had substantially worse 90-day outcomes, including lower functional independence (24% vs. 70%) and higher mortality (38% vs. 4%) (both p < 0.001).
Conclusions:
Delayed or persistent poor filling on dual-phase CTA is an independent imaging marker of reperfusion-related complications following late-window mechanical thrombectomy. Although its incremental contribution to model discrimination was modest, dual-phase CTA may improve early risk stratification and help identify patients who may benefit from intensified post-procedural monitoring. External validation is warranted before routine clinical implementation.
Related Concept Videos
 01:15
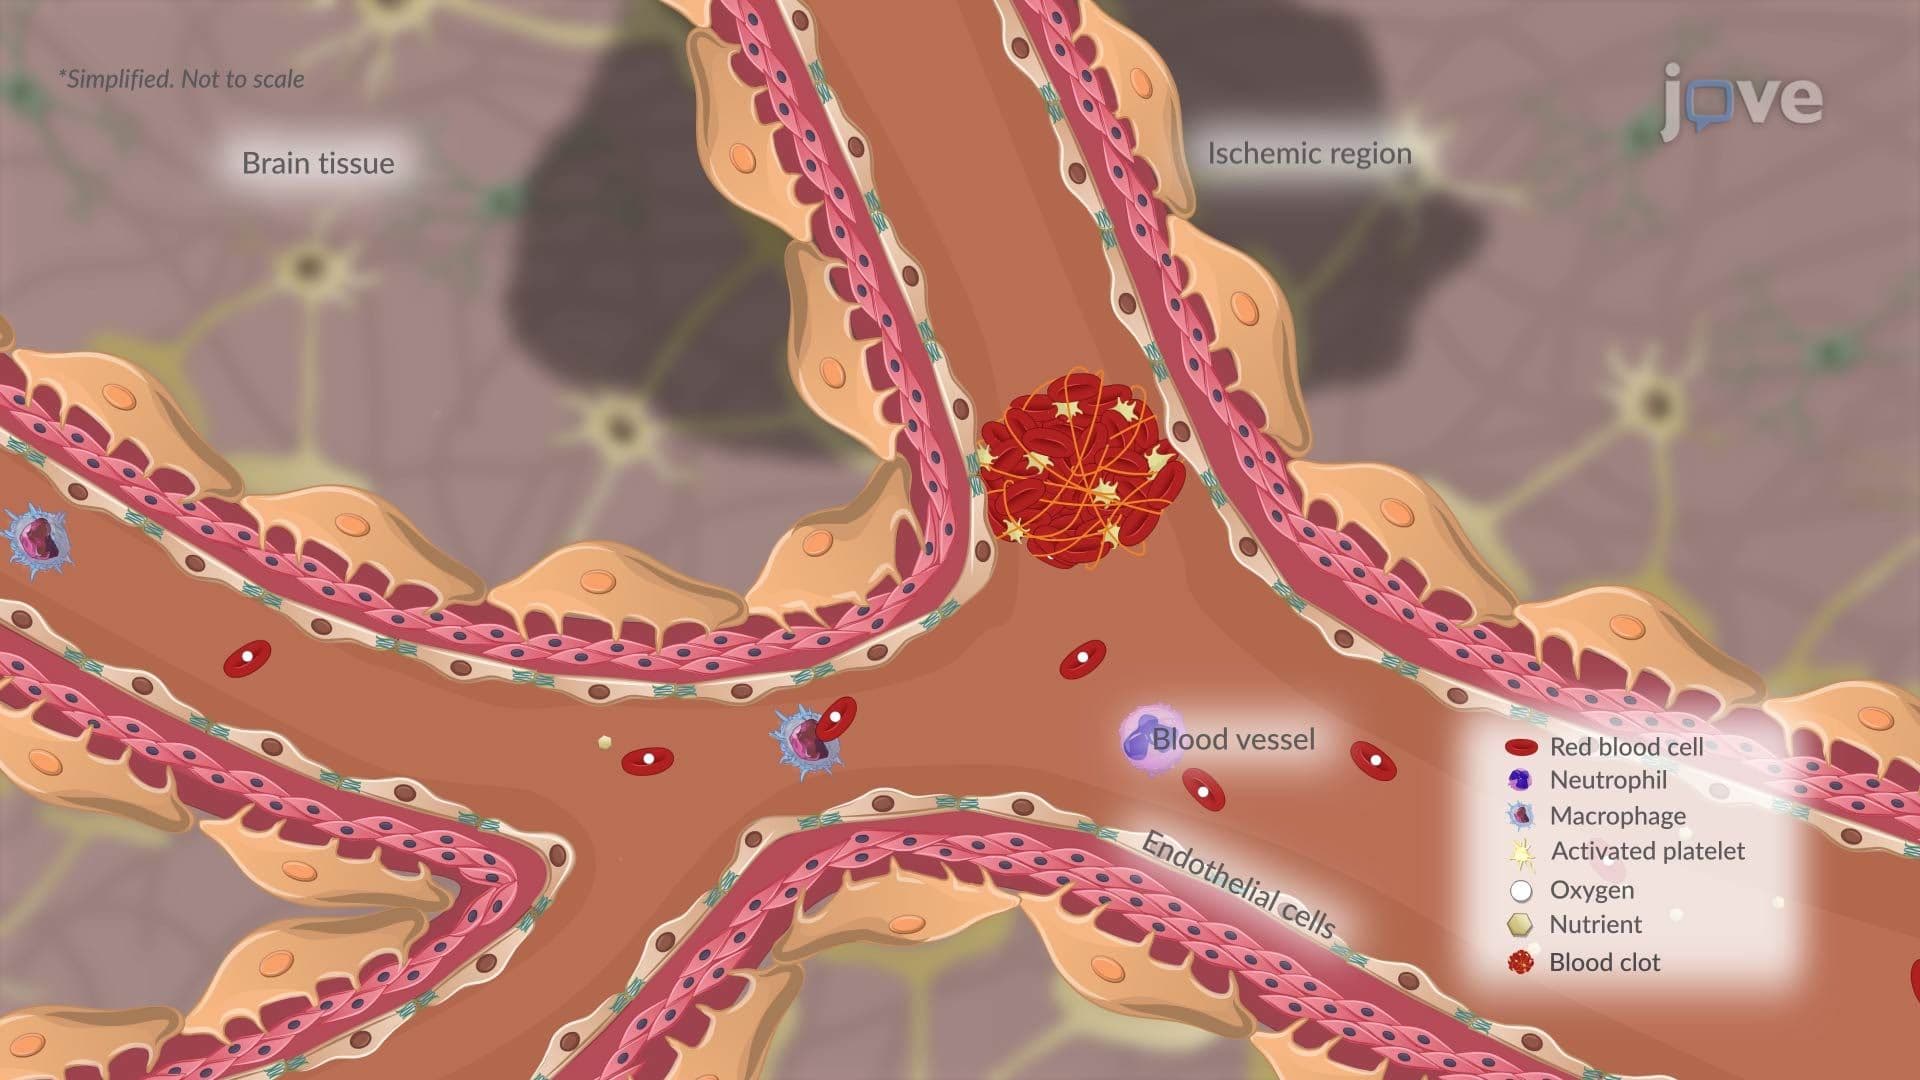
Ischemic Stroke ll: Pathophysiology
 01:26
Transient Ischemic Attack l: Introduction