Related Experiment Video
Updated: Oct 25, 2026
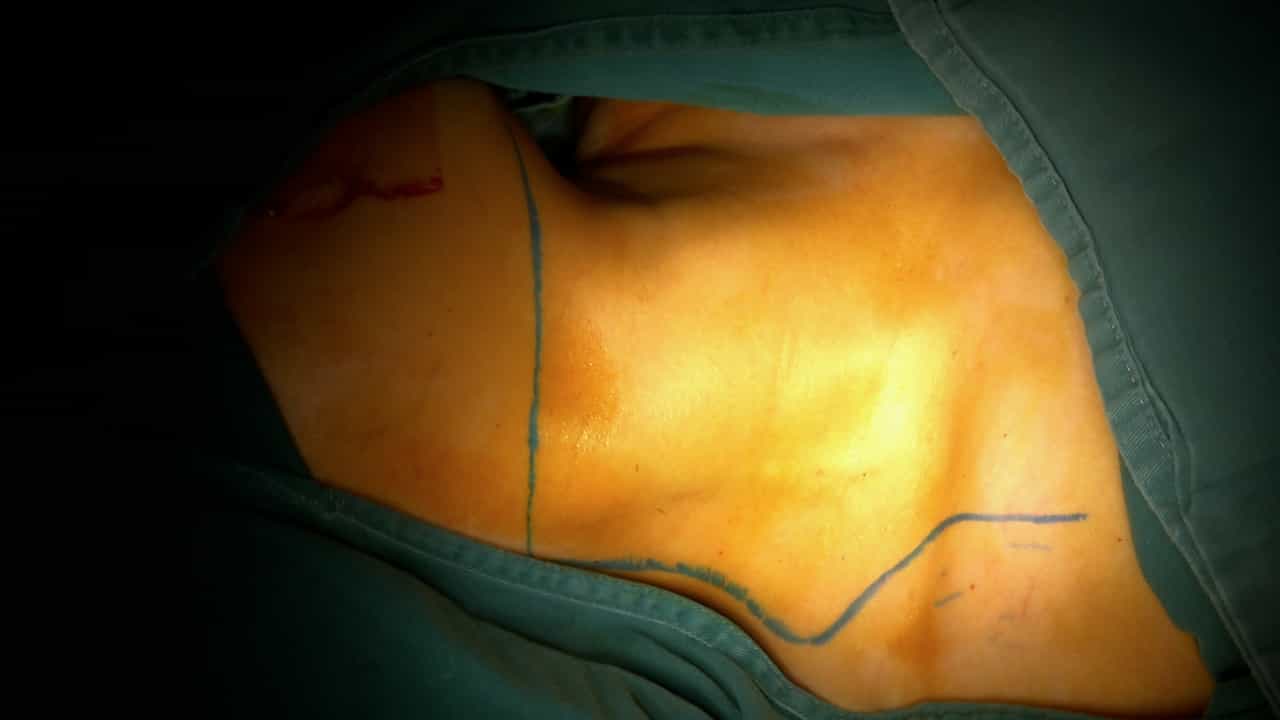
Modified Radical Neck Dissection for Cervical Metastasis
Published on: February 20, 2026
When not to explore: a combat-specific decision framework for selective neck exploration at Role 2
Dmytro Mialkovskyi1, Ihor Rusanov2,3, Iurii Mikheiev3,4
1Surgery, Zaporizhzhia Military Hospital, Zaporizhzhia, Zaporizhzhia oblast, Ukraine.

Abstract:
Current civilian algorithms for penetrating neck trauma assume access to definitive vascular reconstruction, endovascular intervention, advanced imaging, and specialist multidisciplinary care. These assumptions may not apply to Role 2 military facilities, where neck exploration can commit the surgeon to procedures that cannot be completed under optimal conditions. This position paper was developed through a focused narrative review of contemporary recommendations and literature on penetrating neck trauma, vascular and aerodigestive injury, temporary hemorrhage control, and combat casualty care, supplemented by targeted PubMed searches addressing penetrating carotid injury, temporary vascular shunting, carotid collateral circulation, aerodigestive trauma, balloon tamponade, and Role 2-to-Role 3 evacuation. We propose a combat-specific framework distinguishing injuries requiring immediate surgery from those in which temporary hemorrhage control, airway protection, stabilization, and evacuation may better preserve definitive treatment options. The framework challenges automatic application of selected civilian indications for neck exploration in stable patients when hemorrhage is controlled and safe evacuation is feasible, extends this selective approach to aerodigestive injuries, and incorporates transport conditions and en-route rescue capability into the decision to operate. We also propose hypotheses regarding common carotid artery shunting, including the potential effects of collateral cerebral perfusion, shunt position, configuration, monitoring limitations, and thromboembolic complications on neurological outcomes. Role 2 decision-making should incorporate surgical capability, physiology, airway security, effectiveness of temporary hemorrhage control, and evacuation feasibility. Safe evacuation depends not only on transport time but also on the reliability of temporary control and the ability to manage deterioration en route. Rather than replacing civilian algorithms, this framework adapts them to combat casualty care while introducing hypotheses requiring prospective clinical and experimental validation.
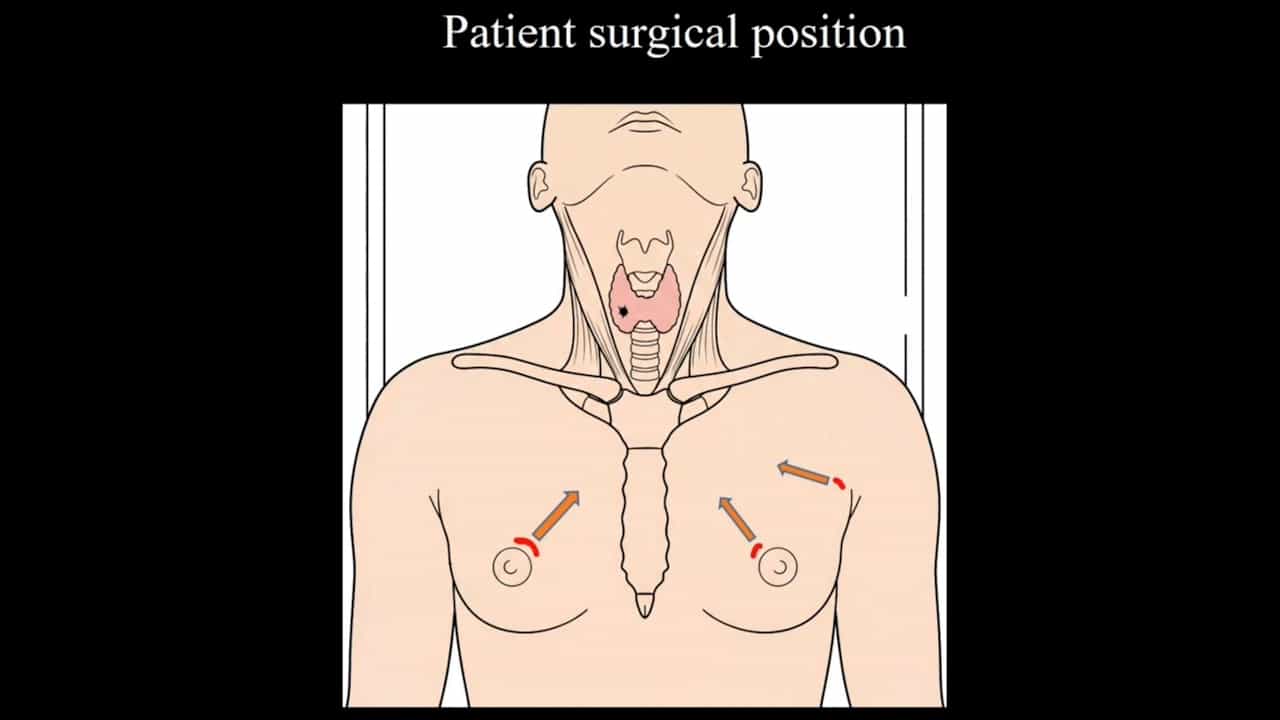
Related Concept Videos
 01:14
Decision Making: Traditional Method
First, a specific claim about the population parameter is decided based on the research question and is stated in a simple form. Further, an opposing statement to this claim is also stated. These statements can act as null and alternative hypotheses, out of which a null hypothesis would be a...
 01:26
Muscles of the Anterior Neck
 01:30
Ethical Dilemmas II
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:26
Arteries of the Head and Neck
The internal carotid arteries supply blood to the anterior portion of the cerebrum. They enter the...
 01:14
Frustration and Conflict: Avoidance-Avoidance, Double-Approach Avoidance