Related Experiment Video
Updated: Oct 25, 2026
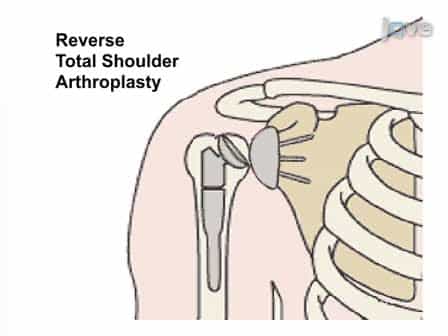
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Supraspinatus management in reverse total shoulder arthroplasty for proximal humerus fractures: current evidence and
Tanawan Kongmalai1, Pinkawas Kongmalai2
1Division of Endocrinology and Metabolism, Department of Medicine, Faculty of Medicine, Siriraj Hospital, Mahidol University, Bangkok, Thailand.

Background:
Reverse total shoulder arthroplasty (rTSA) has become an established treatment for complex proximal humerus fractures in older adults. Although tuberosity healing remains an important determinant of post-operative rotational recovery, management of the supraspinatus tendon during fracture rTSA remains controversial. Because the supraspinatus is attached to the greater tuberosity fragment in acute fracture settings, preservation may influence fragment stability, reduction tension, and functional outcome.
Methods:
A focused narrative review was performed to evaluate biomechanical studies, comparative clinical investigations, and fracture-specific rTSA outcome literature addressing supraspinatus management during rTSA for proximal humerus fractures. Particular attention was given to implant design, tuberosity healing, and post-operative rotational outcomes.
Results:
Available biomechanical evidence suggests that preservation of the supraspinatus tendon may increase displacement of the greater tuberosity fragment, particularly in medialized prosthetic designs. Limited comparative clinical studies demonstrate no consistent functional advantage with supraspinatus preservation and, in some series, improved external rotation following tenotomy or excision. Across the broader fracture rTSA literature, tuberosity healing remains associated with improved post-operative rotation and shoulder function, suggesting that supraspinatus management should be considered within the context of overall tuberosity reconstruction strategy rather than as an isolated technical step.
Conclusion:
Current evidence does not support routine preservation or routine excision of the supraspinatus tendon during fracture rTSA. Instead, management should be individualized according to implant design, fracture morphology, reduction tension, and tuberosity fixation strategy, with the primary objective of optimizing tuberosity healing and post-operative rotational recovery.
