Related Experiment Video
Updated: Oct 25, 2026
Isolation of Pulmonary Artery Smooth Muscle Cells from Neonatal Mice
Published on: October 19, 2013
FOXF1 and alveolar-vascular dysregulation in bronchopulmonary dysplasia-associated pulmonary hypertension
Xinyu Wang1, Jun Han1, Su Yang1
1Department of Neonatology, Children's Medical Center, The First Hospital of Jilin University, Changchun, China.

Abstract:
Bronchopulmonary dysplasia-associated pulmonary hypertension (BPD-PH) is a severe complication of prematurity characterized by arrested alveolarization, pulmonary vascular rarefaction, and progressive vascular remodeling. Increasing evidence suggests that disruption of alveolar-vascular development is a central mechanism underlying disease progression; however, the molecular regulators coordinating these processes remain incompletely understood. Forkhead box F1 (FOXF1) is a developmental transcription factor essential for pulmonary vascular growth, endothelial homeostasis, and alveolar development. Recent studies have identified FOXF1 as a key regulator of endothelial progenitor cell maintenance and alveolar-vascular coupling through interactions with multiple signaling pathways, including VEGF/FLK1, BMP9/ACVRL1, PDGF/TIE2, Notch, WNT5A, and Semaphorin-associated networks. Through these pathways, FOXF1 coordinates angiogenesis, vascular maturation, epithelial differentiation, and tissue repair during lung development. In this review, we summarize the developmental biology of FOXF1 and examine current evidence linking FOXF1 dysregulation to impaired alveolar-vascular development in BPD-PH. We discuss how reduced FOXF1 activity may contribute to endothelial dysfunction, defective angiogenic repair, disrupted epithelial-mesenchymal communication, and pathological vascular remodeling. We further evaluate emerging FOXF1-targeted therapeutic approaches, including nanoparticle-mediated gene delivery, adeno-associated virus (AAV)-based strategies, small-molecule FOXF1 stabilizers, and human vascularized lung organoid platforms. Collectively, available evidence supports a model in which FOXF1 functions as a molecular integrator of alveolar and vascular development, linking arrested alveolarization to pulmonary vascular remodeling in BPD-PH. Nevertheless, current knowledge is derived largely from experimental models and observational human studies. Future investigations integrating human multi-omics datasets, advanced organoid systems, and translational animal models will be essential to determine the causal role of FOXF1 and its potential as a biomarker and therapeutic target in BPD-PH.
Related Concept Videos
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
 01:24
Regulation of Angiogenesis and Blood Supply
 01:10
Atelectasis II: Pathophysiology
 01:23
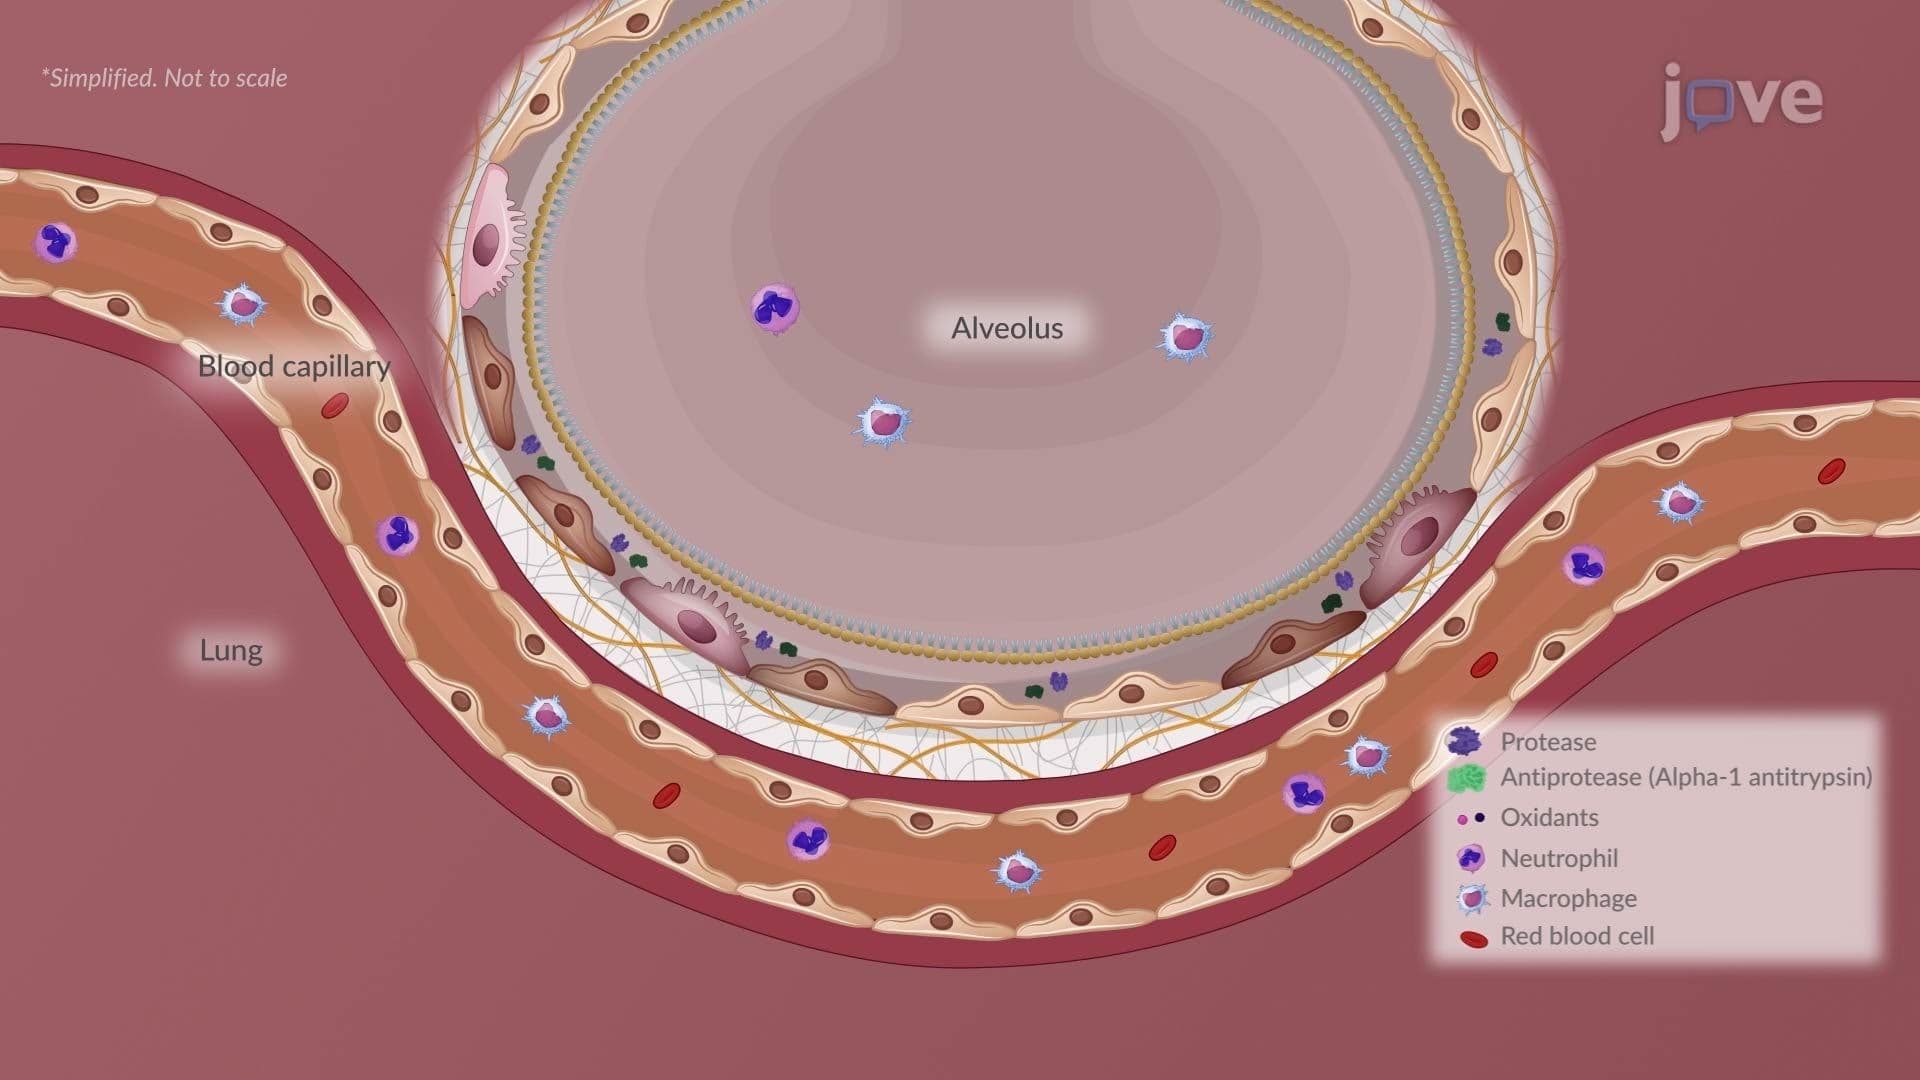
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:05
Breathing