Related Experiment Video
Updated: Oct 25, 2026
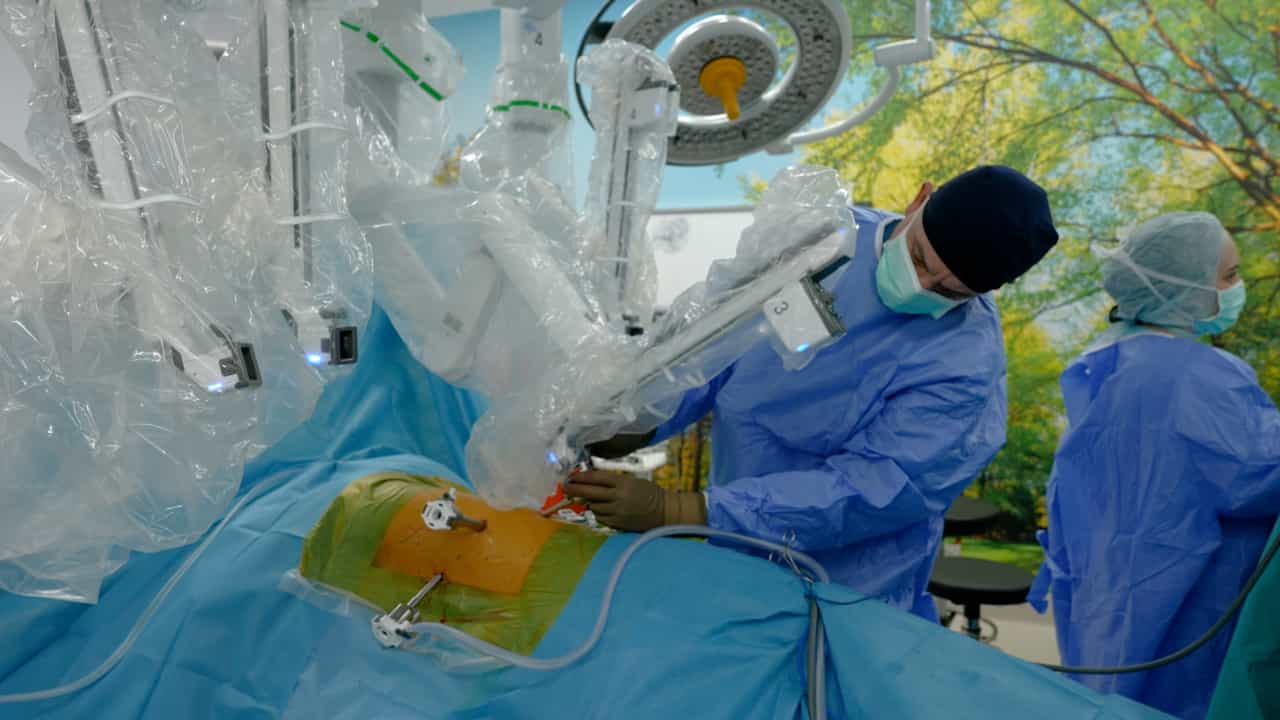
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Retrospective Nomogram Development for Postoperative Pulmonary Complications After Robotic-Assisted Anatomical
Shuai Shi1, Guangrui Wen1, Chengqiang Lei1
1Department of Cardiothoracic Surgery, The People's Hospital of Dazu Chongqing.

Abstract:
Postoperative pulmonary complications (PPCs) remain among the most common adverse events following thoracic surgery, contributing to increased morbidity and prolonged hospital stay. With the growing adoption of robotic-assisted thoracic surgery for anatomical segmentectomy, procedure-specific data on PPC risk stratification remain limited. This retrospective cohort study aimed to evaluate risk factors for PPCs in patients undergoing da Vinci robotic-assisted anatomical segmentectomy and to develop and chronologically validate a nomogram-based prediction model using a homogeneous robotic cohort. The study included 200 patients in the development cohort and 102 patients in the temporal validation cohort. Univariable and multivariable logistic regression analyses were performed in the development cohort, and a three-variable prediction model incorporating age ≥65 years, smoking history, and forced expiratory volume in 1 second (FEV1) <70% predicted was evaluated. Model discrimination was assessed using the area under the receiver operating characteristic curve (AUC), and calibration was assessed using the Hosmer-Lemeshow test and calibration slope. Overall, 64 of 302 patients (21.2%) developed PPCs. In the development cohort, age ≥65 years was independently associated with PPCs (adjusted odds ratio [OR] 2.65, 95% confidence interval [CI] 1.29-5.44, P = 0.008), whereas smoking history (adjusted OR 1.91, 95% CI 0.93-3.91, P = 0.079) and FEV1 <70% predicted (adjusted OR 1.51, 95% CI 0.74-3.10, P = 0.259) were not statistically significant after adjustment. The three-variable model had an AUC of 0.69 (95% CI 0.60-0.78) in the development cohort and 0.85 (95% CI 0.76-0.92) in the temporal validation cohort. These findings support the potential value of a simple preoperative risk model, but external multicenter validation is required before broader clinical application.