Related Experiment Video
Updated: Oct 25, 2026
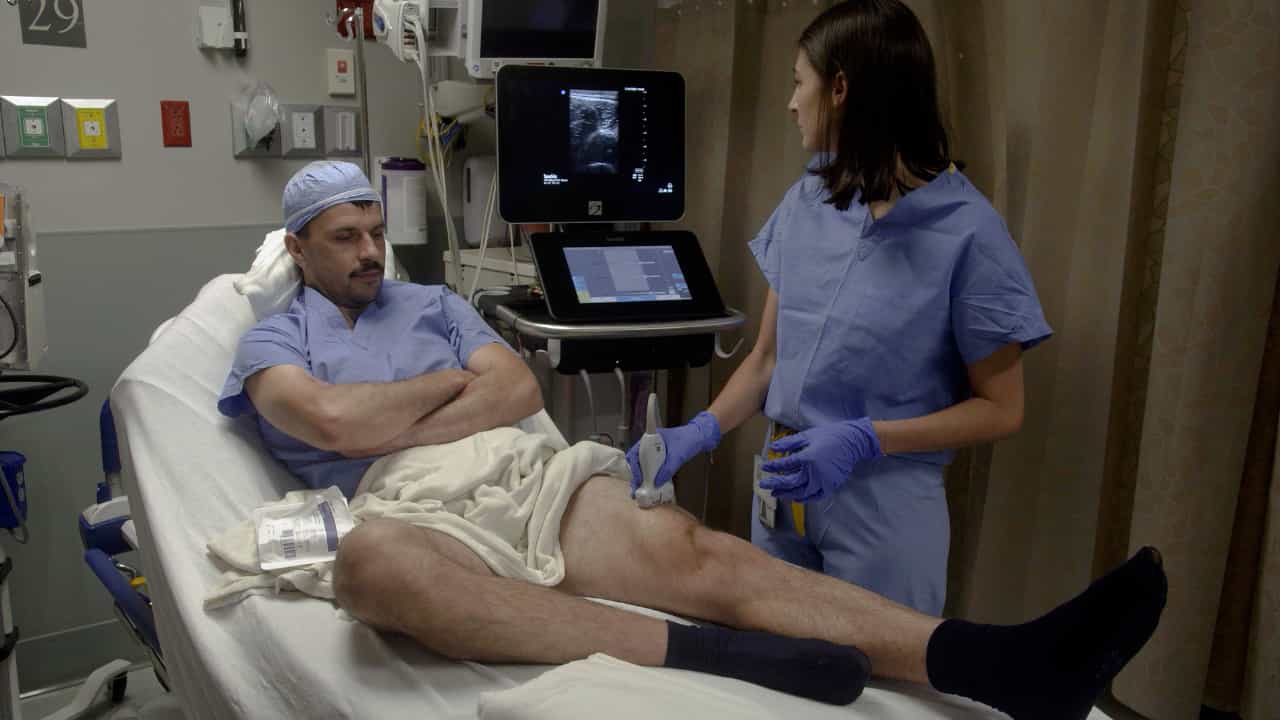
Identifying Frailty Using Point-of-Care Ultrasonography: Image Acquisition and Assessment
Published on: July 26, 2024
Frailty severity, survival and physician service costs among older adults: a linked cohort study from Nova Scotia,
Mohammad H Pulok1,2,3, Alexandra M van der Valk3, Luke Mondor4
1Primary Care Alberta - Health Intelligence, Evidence and Improvement (HIEI), Calgary, Alberta Canada.

Background:
Frailty is associated with greater healthcare use. Still, cost estimates can be biased when shorter survival among severely frail patients is not considered. This study estimated physician service costs across frailty levels, assessing how differential survival influenced expenditures.
Methods:
In this retrospective cohort study, 944 older adults received comprehensive geriatric assessment following emergency department (ED) referral to internal medicine. Frailty was measured using the Clinical Frailty Scale (CFS) and categorised as well, mildly frail, moderately frail and severely frail. Publicly funded physician service costs (2015 Canadian dollars[$]) during the subsequent year were obtained from provincial claims. A three-part regression model adjusted for age, sex and illness acuity separated differences attributable to service intensity from those attributable to survival.
Results:
Participants were ED patients (Mage 80.8 years; 521 women [55%]) referred to Internal Medicine; 41.6% died within 1 year. Physician costs were concentrated in the months immediately following ED presentation. Costs for mildly and moderately frail patients were ~ $300-$400 higher than for well patients, although differences were estimated imprecisely. Severely frail patients incurred $704 less than well patients over 1 year, primarily reflecting shorter survival. During periods patients were alive, all frailty groups incurred higher costs than the well group.
Conclusions:
Physician service costs varied non-linearly with frailty severity. Lower cumulative expenditure among severely frail patients does not necessarily imply lower healthcare need. Clinical pathways and health-system planning should consider differential survival and use frailty assessment to identify individuals who may benefit from proactive multidisciplinary, supportive or palliative care.

Related Concept Videos
 01:27
Pharmacodynamics in Geriatric Patients: Effects of Age
 01:30
Development of Human Microbiota
 01:00
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Distribution