Related Experiment Video
Updated: Oct 25, 2026
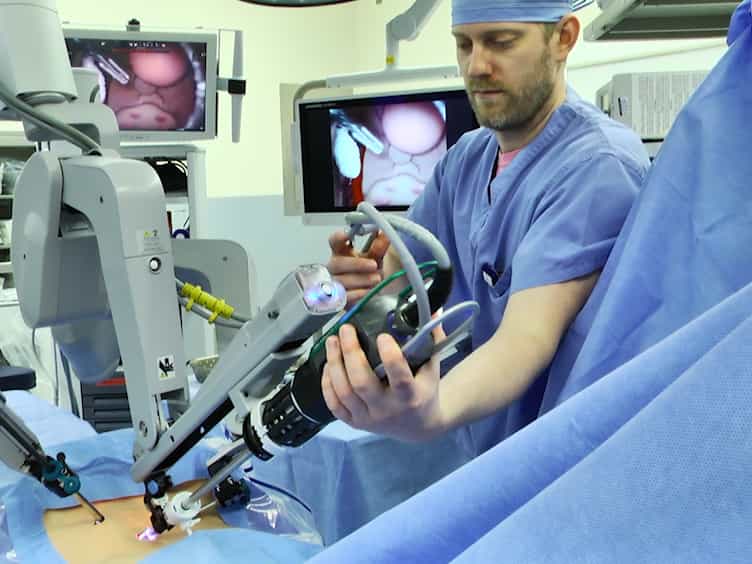
Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Patient-specific role-aware port planning for a bedside-distributed multi-arm surgical robot: simulation and phantom
Mei Feng1, Yalong Shi1, Kun Yang2
1School of Mechanical and Aerospace Engineering, Jilin University, Changchun, 130025, Jilin, China.

Abstract:
Preoperative port placement for multi-arm surgical robots must accommodate patient-dependent abdominal geometry, robot-specific remote-center-of-motion (RCM) constraints, and heterogeneous task requirements of instrument and endoscope arms. This study develops and physically evaluates a patient-specific, role-aware port-planning framework for a four-arm bedside-distributed surgical robot. Abdominal dimensions are extracted from three abdominal computed tomography (CT) volumes, and a case-specific planned lesion center is defined in each volume. These data are combined with literature-reported insufflation increments to construct case-specific planning surfaces. Full-surface candidates are restricted by arm-role eligibility and RCM positioning feasibility before task-level evaluation. Instrument ports preserve lesion-surface coverage and manipulability before secondary entropy-based ranking, whereas the endoscope branch prioritizes maximum visibility and uses kinematic criteria only for tied visibility. Across the three CT-derived cases, selected left-instrument ports increased sampled lesion-surface coverage from 70.2-80.6% to 100%, selected right-instrument ports increased normalized manipulability from 0.444-0.460 to 0.683-0.748, and endoscope visibility increased by 7.8-19.1 mm. Locked-cache ablation showed that removing instrument priority retention changed all six selections and reduced raw manipulability by 20.3-43.3%, whereas replacing entropy-derived weights after priority preservation produced smaller changes. Matched phantom experiments showed higher instrument manipulability in all six selected-versus-reference comparisons and higher endoscope visibility in all three. Within this three-case proof-of-concept cholecystectomy evaluation, these results support integrating patient-specific access geometry, robot feasibility, and explicit arm-role priorities in preoperative port planning while separating task-critical preservation from secondary ranking.
