Related Experiment Video
Updated: Oct 25, 2026

Voluntary Breath-hold Technique for Reducing Heart Dose in Left Breast Radiotherapy
Published on: July 3, 2014
Respiratory Instability-driven Cardiac Dose Deviation in Postmastectomy Deep Inspiration Breath-hold Volumetric
1Department of Radiation Oncology, Amrita School of Medicine, Amrita Vishwa Vidyapeetham, Faridabad, Haryana, India.

Aims:
Deep inspiration breath-hold (DIBH) reduces cardiac exposure during left-sided breast radiotherapy; however, treatment-day cardiac dose may differ from the planned dose because of variations in respiratory reproducibility and anatomy. The aim of this study was to develop and validate a framework for predicting fraction-level cardiac dose variation using routinely acquired respiratory, anatomical, and dosimetric information.
Materials And Methods:
A retrospective cohort of 150 patients treated with postmastectomy DIBH VMAT (volumetric modulated arc therapy) was analyzed. Models were developed using a 30-patient development cohort with patient-wise-nested cross-validation, externally validated in 20 independent patients using cone-beam CT-derived synthetic CT dose recalculation, and applied to a 100-patient deployment cohort. Separate models predicted deviation from planned per-fraction mean heart dose (ΔMHD) and left anterior descending coronary artery dose (ΔLADCA D0.03 cc) using treatment-day real-time position management (RPM)--derived respiratory features, planning computed tomography (CT)-derived geometric variables, and plan-derived dosimetric parameters. SHAP-based analysis was performed to identify influential predictors.
Results:
The final Gradient Boosting model for ΔMHD achieved an internal validation mean absolute error (MAE) of 0.541 ± 0.035 centigray (cGy) and coefficient of determination (R2) of 0.642 ± 0.069. The Ridge Regression model for left anterior descending coronary artery (ΔLADCA) achieved an MAE of 23.413 ± 1.617 cGy and R2 of 0.413 ± 0.082. External validation demonstrated good agreement for ΔMHD (MAE 0.58 cGy, R2 = 0.641), whereas ΔLADCA showed lower performance (MAE 24.14 cGy, R2 = 0.435). Stability index and baseline drift were key predictors.
Conclusion:
Treatment-day-respiratory characteristics combined with anatomical and dosimetric variables can estimate fraction-level cardiac dose variation during DIBH radiotherapy. The framework may support verification-based clinical review, with further validation required before implementation.
Related Concept Videos
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:15
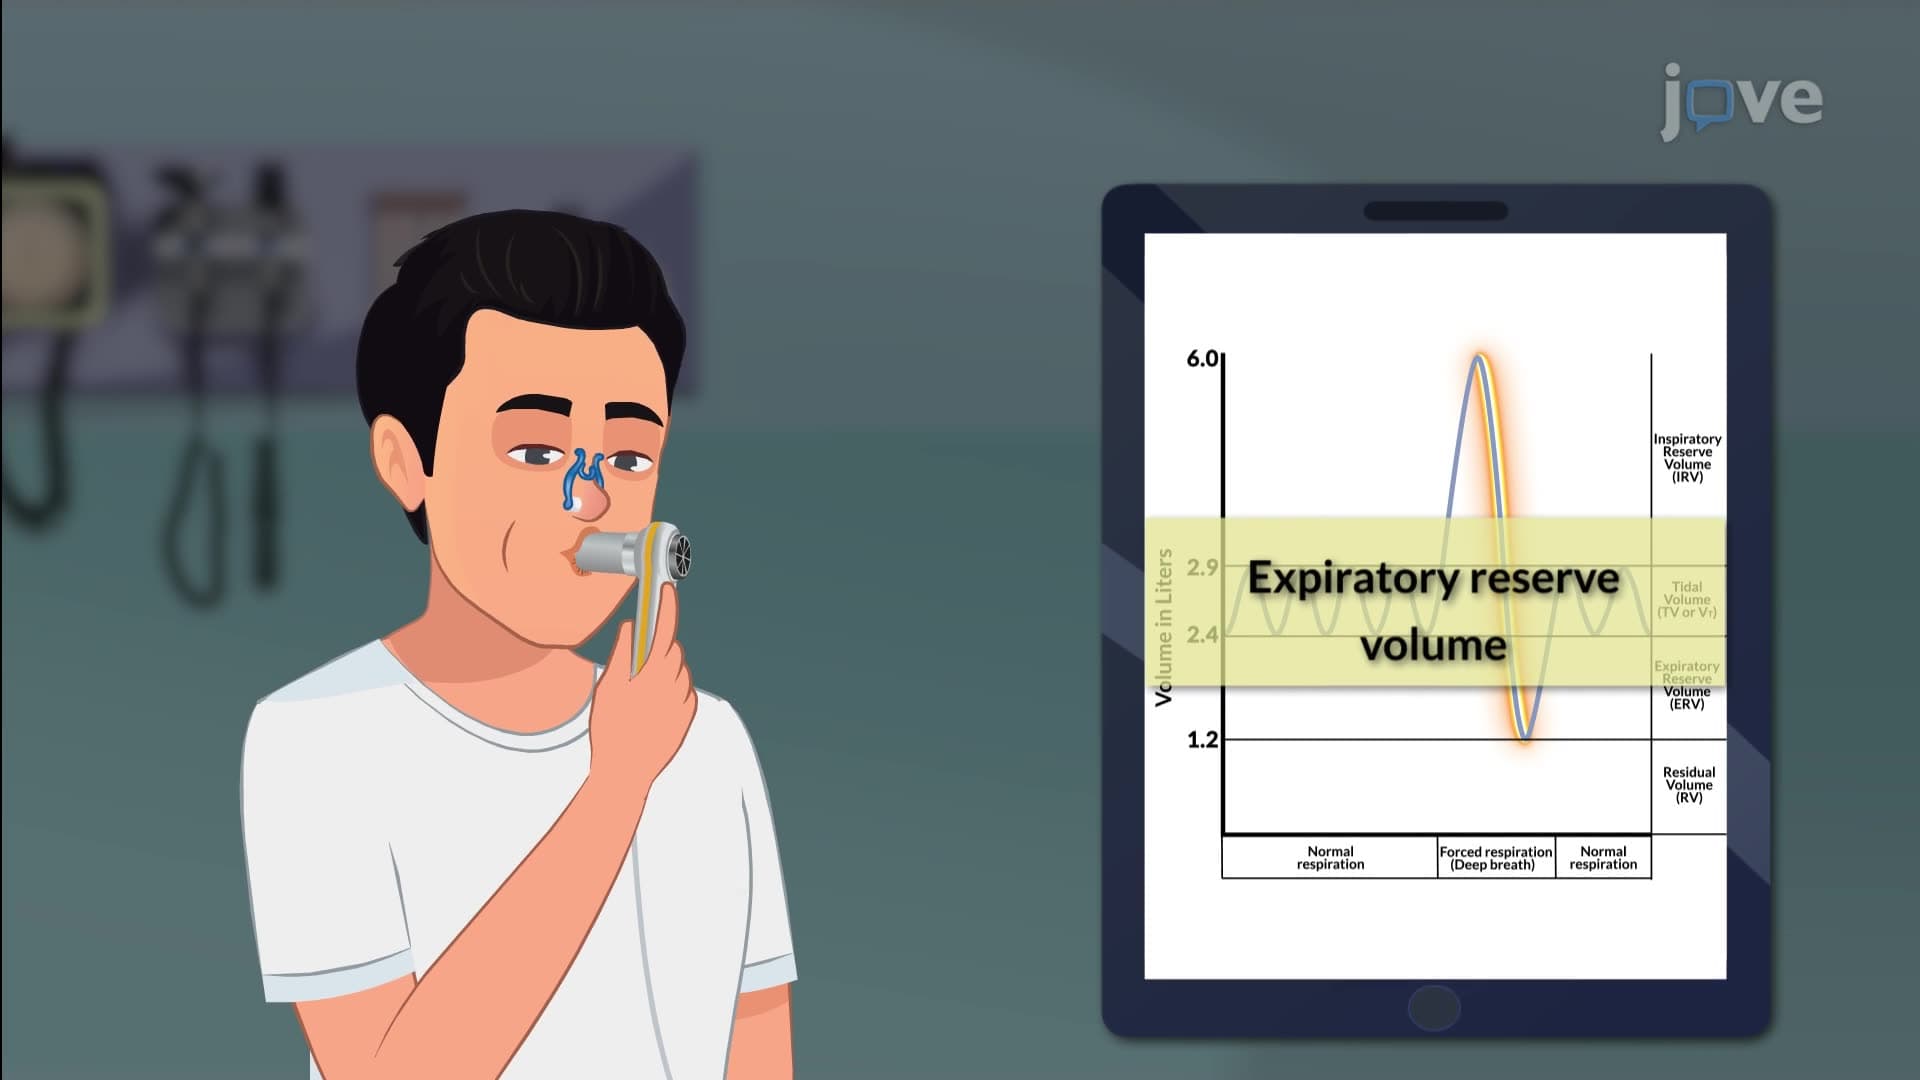
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:26
Respiratory Volumes and Capacities I