Related Experiment Video
Updated: Oct 25, 2026
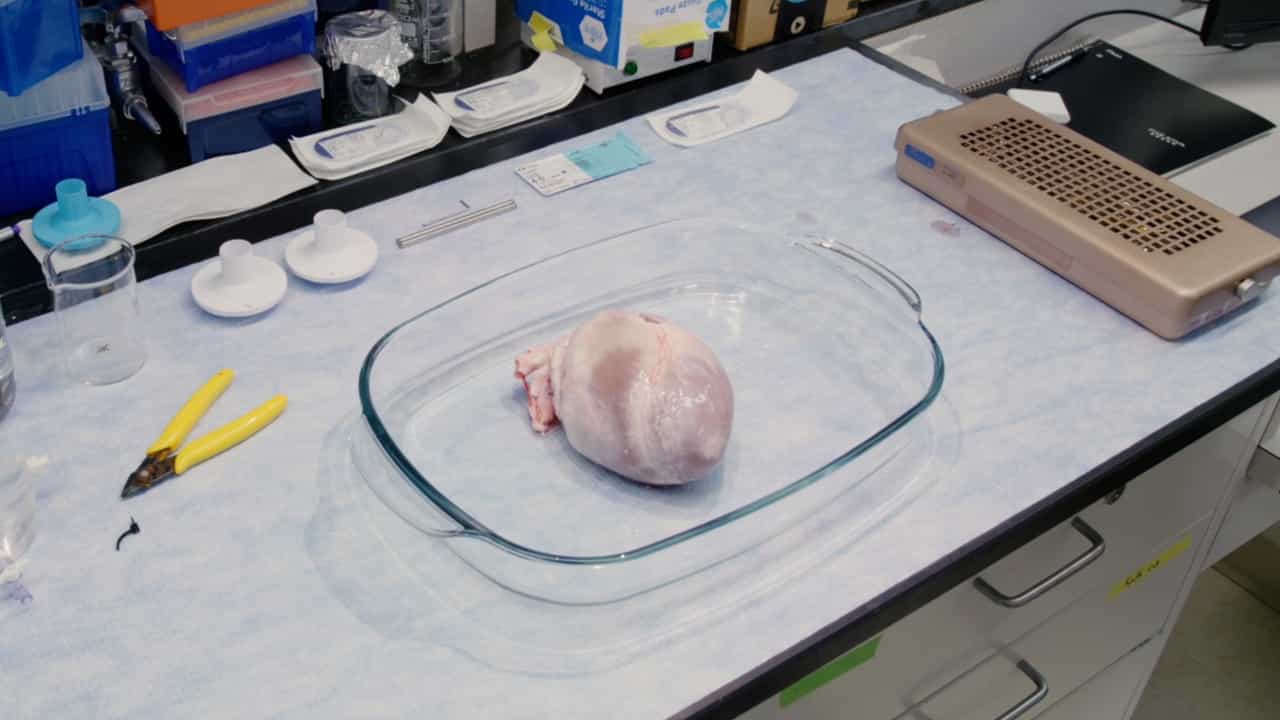
An Ex Vivo Porcine Model for Hydrodynamic Testing of Experimental Aortic Valve Procedures and Novel Medical Devices
Published on: August 25, 2023
Computational Modeling Reduces Leaflet Modification Rates in Valve-In-Valve and Redo Transcatheter Aortic Valve
Nicholas J Valle1, Omar A Saleh2, Omar Jafar1
1Department of Internal Medicine, Macon and Joan Brock Virginia Health Sciences at Old Dominion University, Eastern Virginia Medical School, Norfolk, Virginia, USA.

Background:
Coronary obstruction (CO) complicates valve-in-valve (ViV) and redo transcatheter aortic valve replacement (TAVR) at higher rates than native TAVR. Leaflet modification mitigates this risk but increases procedural burden. Traditional computed tomography angiography (CTA)-based risk stratification relies on static parameters that may overestimate risk; computational predictive modeling (CPM) uses patient-specific data to refine risk assessment.
Objectives:
The study aims to characterize leaflet modification rates in conventional ViV TAVR and redo-TAVR and evaluate the impact of CPM preprocedural planning augmentation on leaflet modification rates.
Methods:
A total of 157 consecutive ViV TAVR or redo-TAVR patients treated from 2022 to 2025 were retrospectively analyzed. CO risk status was derived from traditional CTA parameters. Leaflet modification rates among CTA high-risk subgroups (non-CPM, n = 62; and CPM, n = 29) were compared using Boschloo's one-sided exact test. CPM risk-reclassification patterns were studied using counterfactual binomial analysis.
Results:
Leaflet modification occurred in 26.3% of ViV TAVR and 24.1% of redo-TAVR procedures that used only conventional CTA-based planning methods. Among patients deemed high risk for CO by conventional methods, leaflet modification was significantly lower in the CPM-augmented subgroup vs that in the non-CPM subgroup (24.1% vs 46.8%; OR: 2.76; 95% CI: 1.03-7.40; P = 0.021). CPM-augmented planning reclassified 82.8% of patients to low-risk status, and 79.2% of reclassified patients were managed without leaflet modification. No COs occurred during the study period.
Conclusions:
Among ViV TAVR and redo-TAVR patients at high risk of CO based on conventional CTA-based planning, the use of CPM to augment standard risk assessment was associated with a significant reduction in leaflet modification procedures.
