Related Experiment Video
Updated: Oct 25, 2026
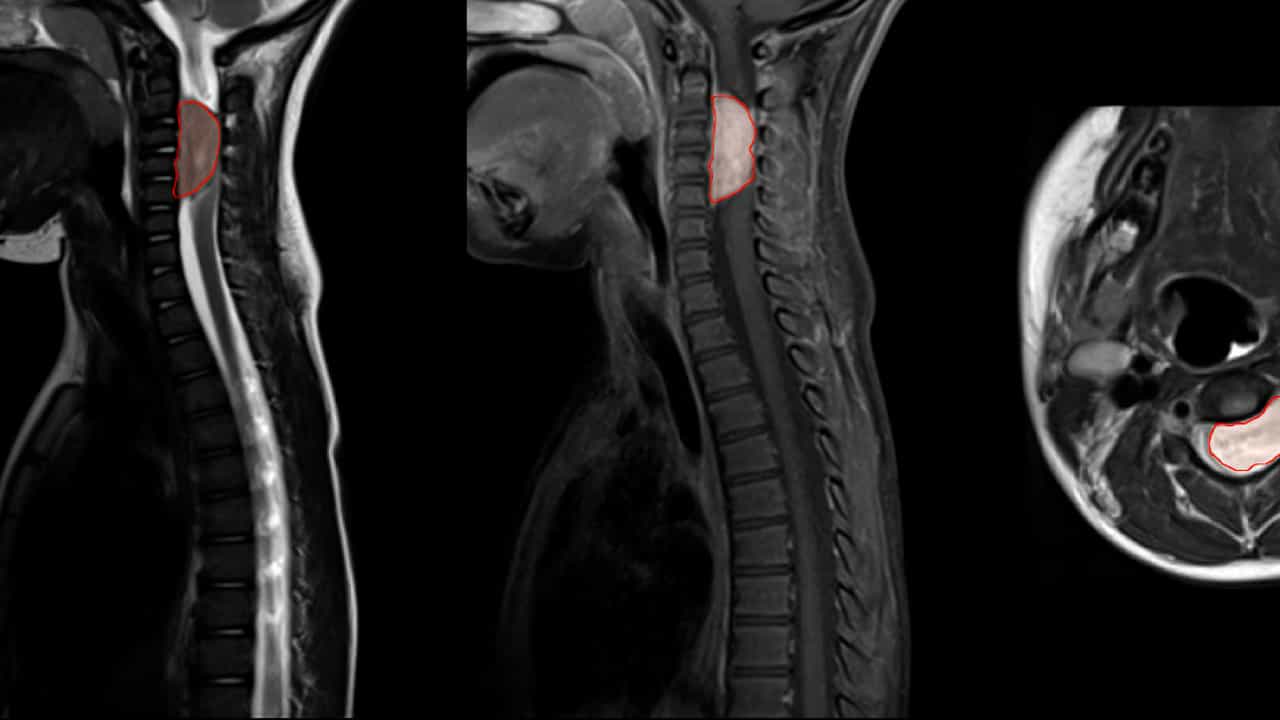
Posterior Approach for Microsurgical Resection of a Ventrolateral Cervical Ganglioneuroma: an Illustrative Case and Technical Report
Published on: August 4, 2026
S2 Sacral root Schwannoma: Laparoscopic Excision with ICG
Hakan Kula1, Rumeysa B Gumus2, Sefa Kurt2
1Endometriosis Foundation of America, New York, USA.

Objective:
To demonstrate intravenous ICG-assisted fluorescence mapping as an assistive tool for improving surgical precision and tissue differentiation during laparoscopic S2 root schwannoma excision.
Setting:
Tertiary center specializing in an advanced laparoscopic surgery.
Participants:
A 63-year-old woman presented with severe left-sided S2 dermatomal and pudendal pain and progressive neurologic findings. Her surgical history was notable for prior excision of endometriosis. Preoperative T2-weighted pelvic MRI demonstrated a 3-cm intrapelvic mass arising from the left S2 sacral root, consistent with a schwannoma.
Interventions:
Laparoscopic excision of the S2 sacral root schwannoma was performed with intravenous ICG fluorescence mapping (0.25 mg/kg, 15 minutes pre-dissection) (1). Intraoperatively, the schwannoma demonstrated unexpectedly low fluorescence intensity relative to surrounding peripheral nerves and vascular structures, diverging from previously reported patterns of tumor hyperfluorescence. This hypofluorescence provided additional visual contrast alongside standard anatomic landmarks during dissection, without complication. At 6-month follow-up, electric shock-like pain had decreased and pudendal pain had improved from baseline. Deep tendon reflexes remained intact, and MRI confirmed no residual mass.
Conclusion:
Pelvic schwannomas involving deep sacral nerve roots are rare and diagnostically challenging (2,3). This case highlights a stepwise neuropelveological approach (4) - from anatomic identification of the S2 root to interfascicular neurolysis and nerve-sparing excision - as a reproducible framework for safe laparoscopic management. Notably, ICG fluorescence mapping did not follow the expected pattern of tumor hyperfluorescence (5); the schwannoma instead appeared hypofluorescent relative to adjacent vascularized tissue.