Related Experiment Video
Updated: Oct 25, 2026
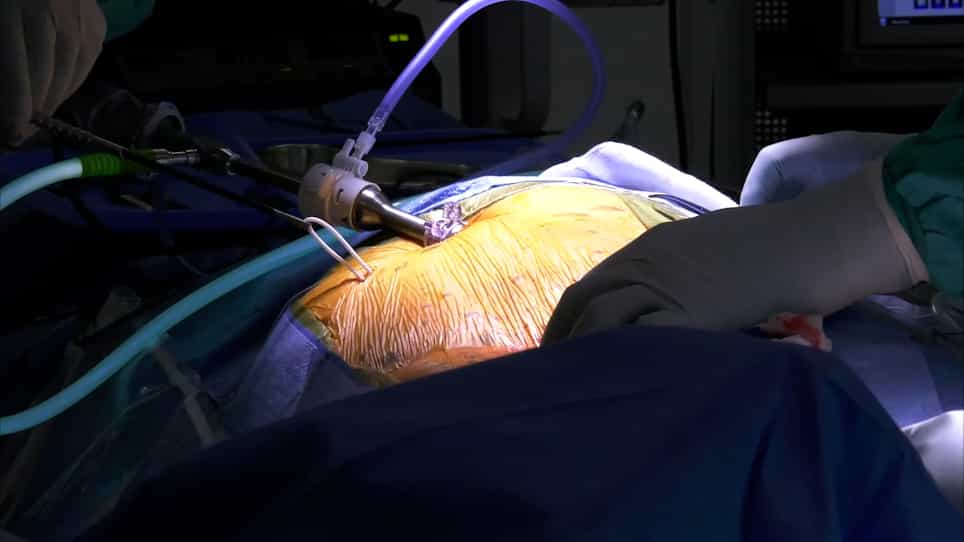
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Diagnostic accuracy of CSF tap-test parameters in predicting shunt responsiveness in normal pressure hydrocephalus: a
Sagar Poudel1, Deepa Dash2, Alfonso Fasano3,4
1Department of Medicine, All India Institute of Medical Sciences, New Delhi, India.

Background:
The cerebrospinal fluid tap test (CSF-TT) is widely used as an ancillary test to select patients with idiopathic normal pressure hydrocephalus (iNPH) for ventriculoperitoneal (VP) shunt surgery; however, its diagnostic utility remains unclear.
Objectives:
To evaluate the diagnostic utility of CSF-TT in predicting outcomes following VP shunts.
Methods:
Patients with probable iNPH underwent assessments of gait, urinary, and cognitive function using the Dutch gait scale, timed up and go (TUG) gait score, iNPH grading scale, and modified Rankin Scale (mRS) at baseline and 24 h after CSF-TT. They were offered VP shunt surgery based on the clinico-radiological profile, regardless of CSF-TT outcome. Postoperative outcomes were evaluated at 24 weeks, and patients who showed ≥ 1-point improvement in mRS were classified as shunt responders. We also assessed the diagnostic accuracy of the tap test for predicting ≥ 1-point improvement in iNPH at 24 weeks. The diagnostic performance of various baseline tests was assessed using the area under receiver operating characteristic curves (AUROCs).
Results:
24 patients underwent VP shunting, 15 (62.5%) were classified as shunt responders. A one-point reduction in the mRS at 24 h post-CSF-TT had a sensitivity of 53.3% (95% CI: 26.6-78.7) and specificity of 66.7% (95% CI: 29.9-92.5) in predicting shunt responsiveness based on mRS as outcome. A one-point reduction in the iNPH scale at 24 h post CSF-TT had a sensitivity of 64.3% (95%CI 35.1-87.2) and a specificity of 66.7% (95% CI 22.3-95.7) to predict a one-point improvement in the iNPH scale at 24 weeks post VP shunt. Changes in mRS, Dutch gait score, TUG test score, and iNPH score were not valid predictors, as the confidence intervals of the AUROCs crossed 0.5.
Conclusion:
CSF-TT parameters show limited accuracy in predicting shunt responsiveness in patients with iNPH. Our results suggest that about one-third of positive tap tests were false positives, and the test has poor diagnostic performance as a standalone predictor of postoperative shunt outcomes.