Related Experiment Video
Updated: Oct 25, 2026

Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Jejunal intussusception following distal gastrectomy with Billroth I anastomosis: a case report
Jing Guo1,2, Runjie Hou1,2, Yuan Zhang1,3
1Gastrointestinal Surgery Department, Baotou Central Hospital, Baotou, Inner Mongolia, China.

Abstract:
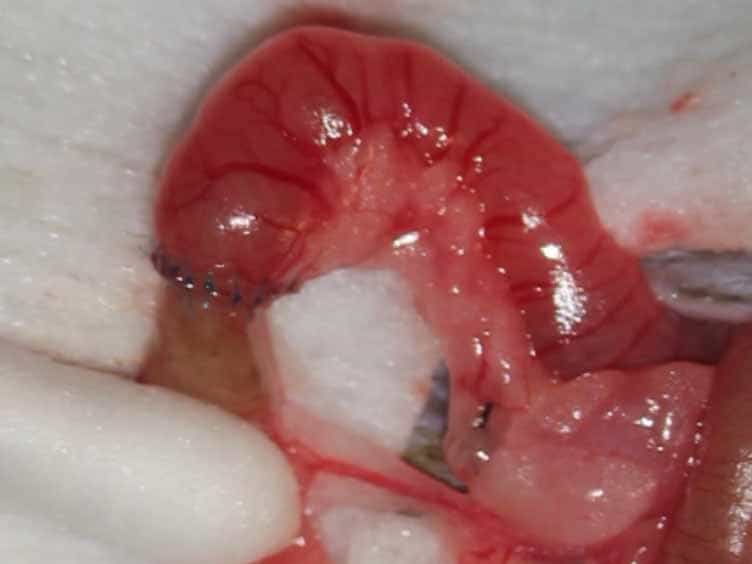
A 41-year-old male patient presented with acute persistent abdominal pain for 4 h and was admitted to our hospital in October 2023. The patient had a height of 178 cm and a weight of 55 kg, with a precisely calculated body mass index (BMI) of 17.4 kg/m² and a body surface area of 1.73 m². He was diagnosed with acute gastric perforation and underwent emergency distal gastrectomy combined with Billroth I gastroduodenal anastomosis and intraoperative jejunal feeding tube placement. On postoperative day (POD) 19, the patient developed aggravated abdominal distension and paroxysmal abdominal pain without fever, vomiting, or diarrhea. Laboratory tests showed slightly elevated inflammatory markers and normal serum lactate, while abdominal computed tomography (CT) revealed typical intestinal intussusception and partial intestinal obstruction. Emergency re-laparotomy confirmed antegrade jejunojejunal intussusception located approximately 20 cm distal to the Treitz ligament, with an intussusception length of approximately 40 cm. Manual reduction was successfully performed without intestinal resection or intraoperative complications. The patient achieved uneventful gastrointestinal function recovery and was discharged on POD 12 after reoperation. No recurrence of intussusception was observed during 6 months of outpatient follow-up. This study reports a rare case of late-onset antegrade jejunojejunal intussusception following Billroth I gastrectomy. Combined effects of low BMI-related loose mesentery, intra-abdominal postoperative adhesions, and indwelling jejunal feeding tube were identified as potential associative risk factors rather than definitive causal factors. We aim to summarize the clinical characteristics, diagnostic strategies, and standardized prevention and treatment protocols of this rare postoperative complication to supplement relevant clinical evidence.
Related Concept Videos
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube through...
 01:29
Intestinal Obstruction I: Introduction
 01:25
Peptic Ulcer Disease V: Surgical Management and Nursing Care
Surgical Interventions for Peptic Ulcer Disease
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:07
Intestinal Obstruction II: Pathophysiology