
Transient ST-T Changes During Submaximal Exercise Revealing Anomalous Right Coronary Artery Origin in an Asymptomatic
Vojtěch Illinger1, Jan Kovanda2, Kryštof Slabý1
1Department of Rehabilitation and Sports Medicine Second Faculty of Medicine Charles University in Prague and Motol and Homolka University Hospital Prague Czech Republic.

Background:
Anomalous aortic origin of a coronary artery is a recognised structural cause of sudden cardiac death in athletes younger than 35 years. Most affected individuals are asymptomatic prior to cardiac events, and resting and exercise electrocardiography (ECG) findings are frequently normal or non-specific, limiting the effectiveness of preparticipation screening.
Case Summary:
We report a case of a 22-year-old asymptomatic athlete in whom preparticipation screening revealed transient ST-segment depression and T-wave inversions during submaximal exercise and recovery, whereas findings at peak exercise remained normal. Point-of-care echocardiography performed by a sports medicine specialist raised suspicion of an anomalous origin of the right coronary artery from the left aortic sinus of Valsalva, which was subsequently confirmed by computed tomography coronary angiography. High-risk anatomical features included an acute ostial angle and an interarterial course of the right coronary artery. Functional testing with exercise myocardial stress scintigraphy showed no inducible perfusion defect. Following multidisciplinary consultation, a conservative management strategy with activity modification and close follow-up was adopted.
Discussion:
This case highlights the potential clinical significance of transient ST-T abnormalities occurring during submaximal exercise and recovery, even in the absence of symptoms or abnormalities at peak workload. In this patient, recognition of this reproducible but non-specific ECG pattern prompted further structural evaluation leading to the diagnosis of AAOCA. It also underscores the limitations of current guidelines in managing asymptomatic athletes with high-risk coronary anatomy but without evidence of inducible ischaemia, supporting the need for individualised decision-making.
More Related Videos
 13:10
Direct Re-implantation of Left Coronary Artery into the Aorta in Adults with Anomalous Origin of Left Coronary Artery from the Pulmonary Artery (ALCAPA)
Published on: April 24, 2017
 07:02
Operating Transverse Aortic Constriction with Absorbable Suture to Obtain Transient Myocardial Hypertrophy
Published on: September 9, 2020
Related Concept Videos
 01:30
Acute Coronary Syndrome I: Introduction
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
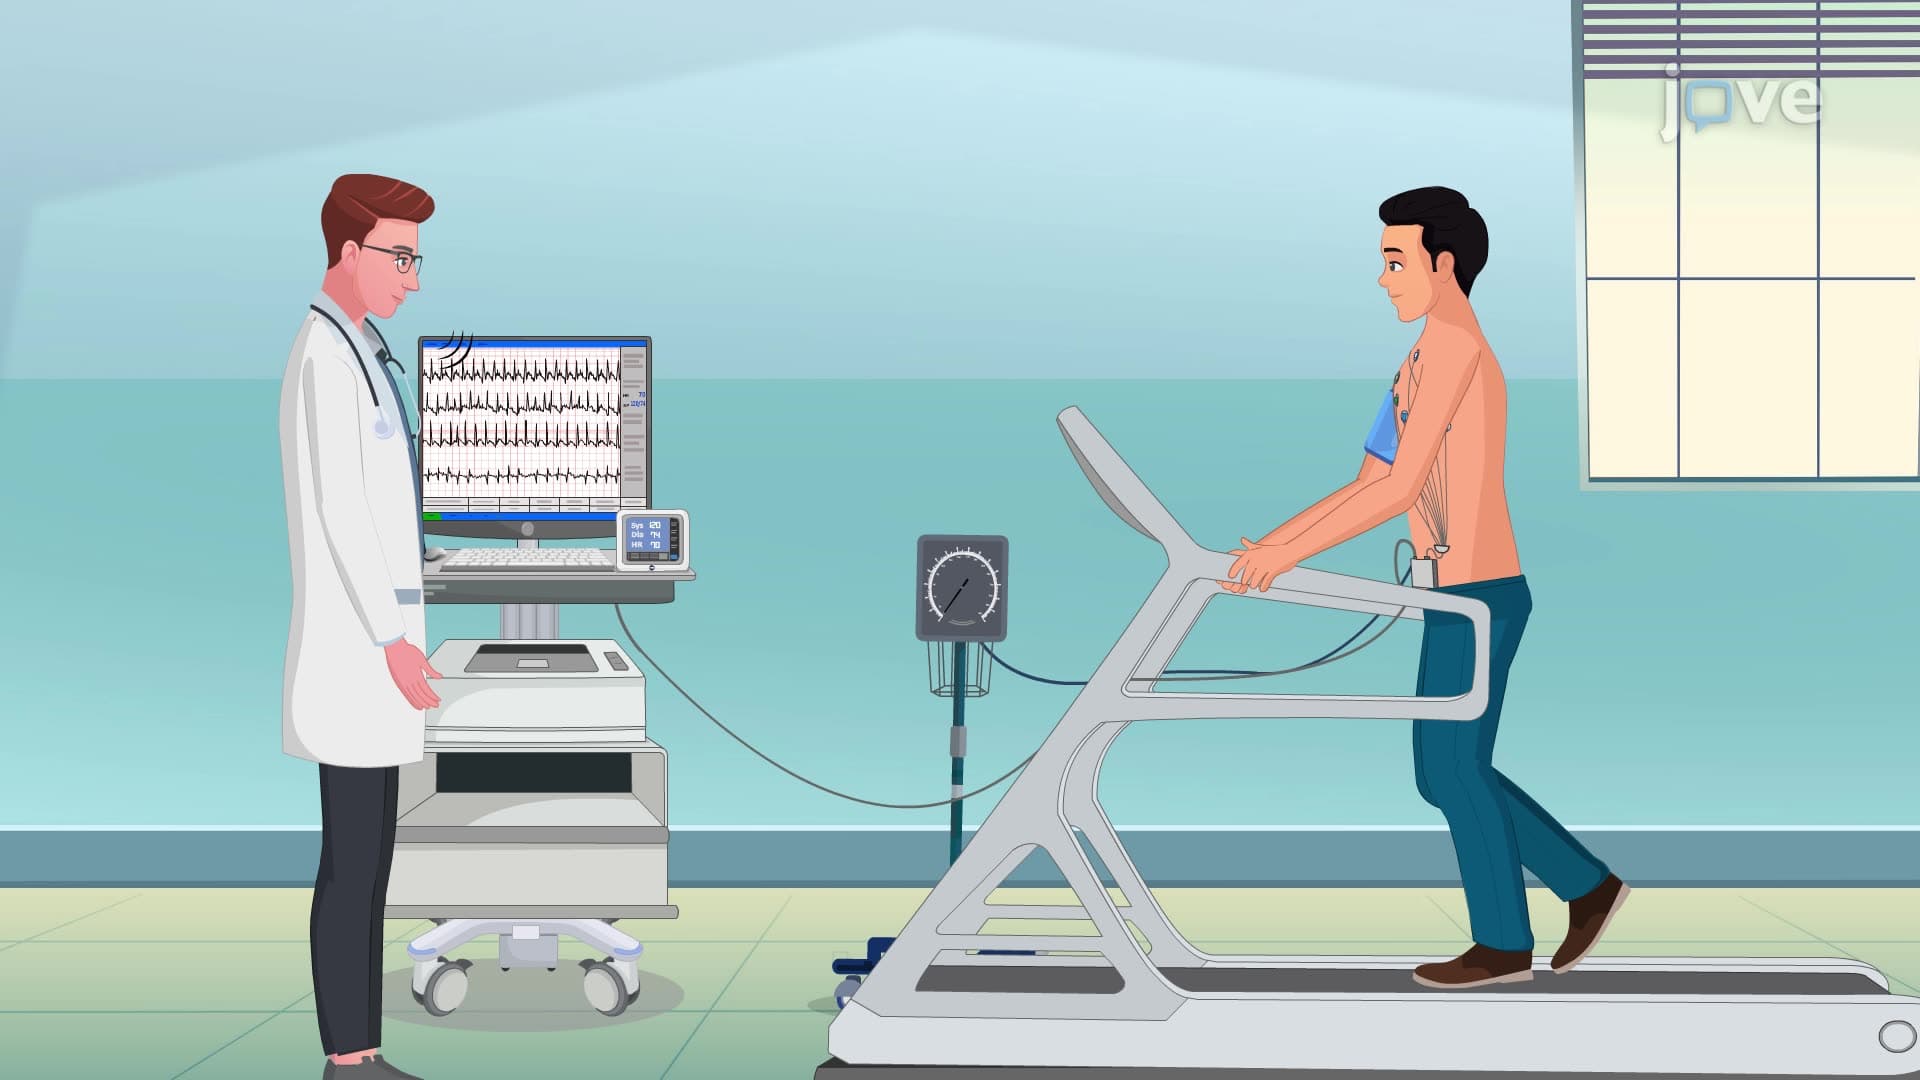 01:26
Exercise Stress Test
Exercise stress testing, commonly known as a treadmill test, is a noninvasive procedure used to evaluate cardiovascular function and diagnose heart conditions.
Definition
An exercise stress test measures the heart's response to exertion using a treadmill or stationary bicycle. Chest electrodes record the heart's electrical activity through an ECG, and blood pressure is monitored regularly.
Purposes
 01:21
Coronary Circulation
Coronary circulation begins at the base of the aorta, where two main arteries arise—the left and right coronary arteries. These arteries encircle the heart in the coronary sulcus and supply the...
 01:19
Acute Coronary Syndrome II: Pathophysiology and Clinical Manifestations
 01:18
Physiology of the Heart: The Cardiac Cycle
Diastole: The Relaxation Phase
During diastole, all four heart chambers relax. The atrioventricular (AV) valves open, and the semilunar valves close. This phase sees the lowest chamber pressures, promoting ventricular filling. Venous blood enters the heart through the...