Related Experiment Video
Updated: Oct 26, 2026
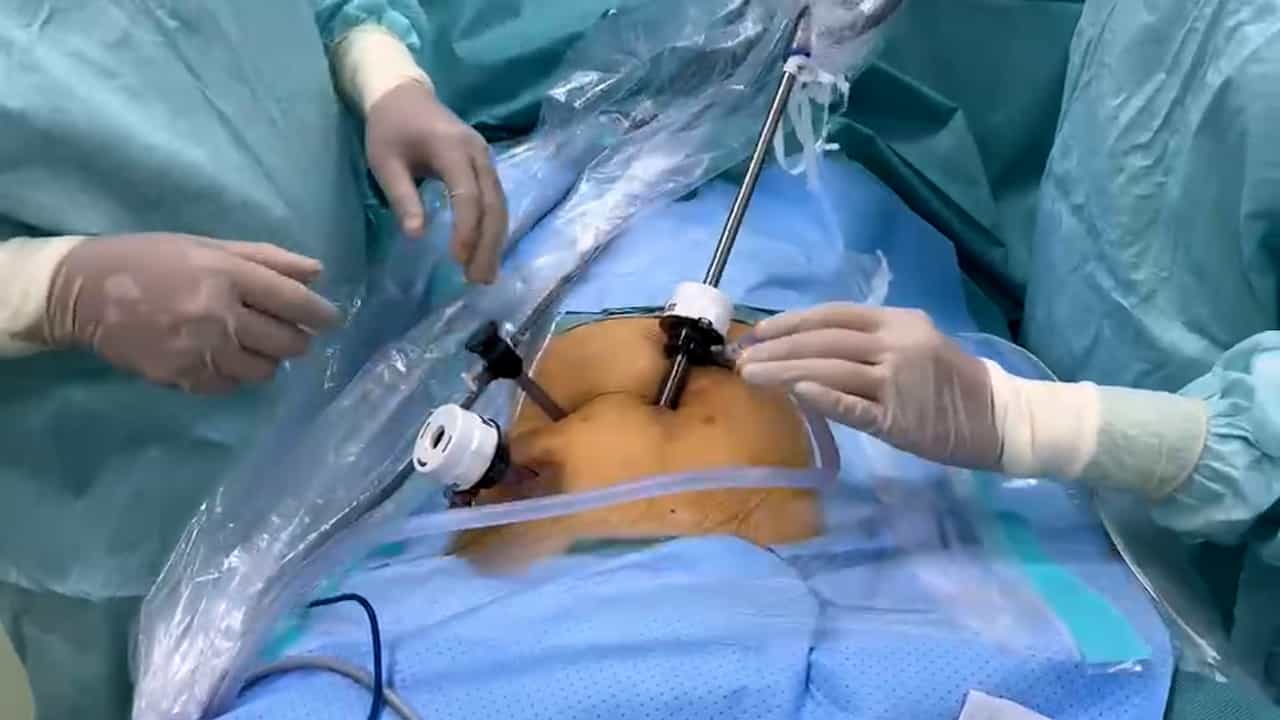
Clinical Application of Single-Surgeon, Three-Port, Laparoscopic Resection for Colorectal Cancer with Natural Orifice Specimen Extraction
Published on: March 24, 2023
Stepwise surgical management of rectal foreign bodies: a multicenter operative case series and systematic review
In Kyu Park1, Kyung Uk Jung2, Songsoo Yang1
1Department of Surgery, Ulsan University Hospital, University of Ulsan College of Medicine, Ulsan, Republic of Korea.

Background:
Most rectal foreign bodies (RFBs) are removed non-operatively; operative management after failed transanal extraction remains poorly standardized. We describe a multicenter series of surgically managed RFBs and a systematic review of case series to quantify how often abdominal access avoids opening the bowel.
Methods:
All patients who underwent operating-room extraction of an RFB at three institutions over 5 years (2019-2023) were reviewed; bedside and endoscopy-suite removals were not captured, so the cohort represents surgically managed RFBs. The review (PubMed/MEDLINE, Embase, Scopus, Web of Science; Preferred Reporting Items for Systematic reviews and Meta-Analyses 2020; retrospective registration) included case series of five or more patients in any language, with extracted values checked against primary reports wherever available and source-level qualifications documented explicitly; all included series were appraised item by item with the Joanna Briggs Institute Critical Appraisal Checklist for Case Series.
Results:
In total, 22 patients (19 men; median age 49 years) were included, all self-inserted. Fourteen were managed transanally or by transanal minimally invasive surgery (TAMIS) (transanal 12, TAMIS 2) and eight by an abdominal approach (five open, two hand-assisted laparoscopic, and one laparoscopic); two minimally invasive attempts were converted. Two proximal objects were delivered per anum by milking without a deliberate bowel incision. Of the other six abdominal cases, three underwent resection, two required deliberate extraction enterotomies that were closed primarily, and one pre-existing contained perforation was managed by lavage and primary repair without diversion; a stoma was formed in three, all with perforation. There were no deaths. Abdominal cases more often involved objects above the rectosigmoid junction (7/8 vs. 2/14) and perforation (4/8 vs. 0/14), but not larger objects; all comparisons were exploratory and unadjusted. The review included 60 series from 26 countries (1976-2026). Among the 42 series that explicitly distinguished milking from bowel opening, 64 of 181 abdominal procedures were completed by milking without an enterotomy. Post-extraction endoscopy was performed in 0%-100% of patients across series.
Conclusions:
A stepwise, organ-preserving strategy-transanal or TAMIS extraction, then laparoscopic or hand-assisted milking, and then enterotomy, with resection and stoma reserved for perforation with severe injury or contamination-was executable in this cohort. In the published series that record the distinction, abdominal access did not entail opening the bowel in approximately one-third of procedures.
Related Concept Videos
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:25
Urinary Tract Calculi VI: Surgical Management
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...