Related Experiment Video
Updated: Oct 26, 2026
Single Incision Plus One Port Laparoscopic Proximal Gastrectomy with Double Channel Anastomosis for Gastric Cancer Treatment
Published on: December 27, 2024
Combined laparoscopic and endoscopic technique for safe percutaneous endoscopic gastrostomy in a patient with
David Hakimian1,2, Anat Hershko Moshe1,2, Joshua Zev Gottesman3
1Institute of Gastroenterology and Hepatology, Hadassah Medical Center, Jerusalem, Israel.

Background And Aims:
PEG is the standard method for long-term enteral access but may fail when anatomical distortion or visceral interposition prevents safe placement. Laparoscopic-assisted PEG combines laparoscopic exposure with endoscopic guidance, providing a minimally invasive rescue technique in such cases.
Methoods:
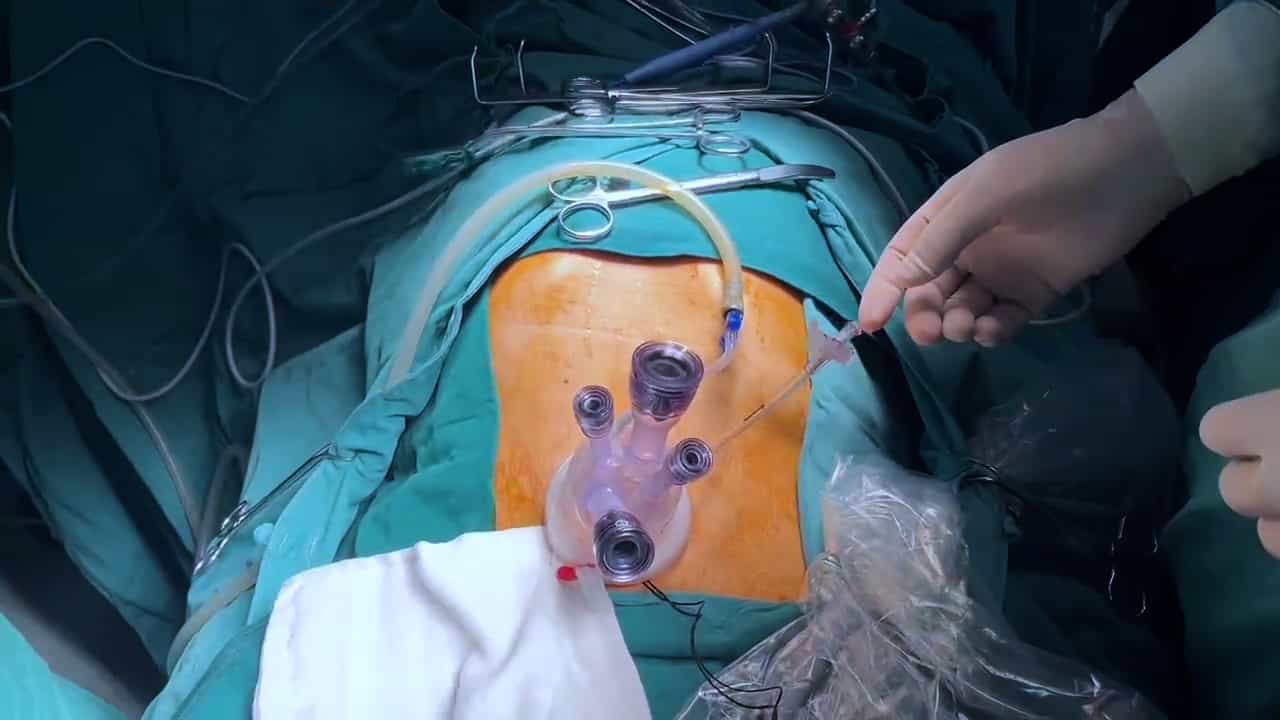
We report a 69-year-old man with advanced mixed salivary gland carcinoma (T4N3bM0) previously treated with bilateral neck dissection and radiotherapy. He developed severe dysphagia secondary to a postradiation esophageal stricture and bilateral vocal cord paralysis, leading to significant malnutrition with weight decline from 72 to 58 kg over 1 year. Long-term enteral feeding was indicated. Two conventional PEG attempts failed because of absent transillumination, and a radiologic gastrostomy attempt was aborted because the transverse colon was interposed between the abdominal wall and the stomach. With the patient under general anesthesia via tracheostomy, laparoscopic-assisted PEG was performed. Laparoscopy identified a superiorly displaced transverse colon overlying the stomach, which was mobilized to create a safe window. A 14F pull-type PEG tube was successfully inserted under combined laparoscopic and endoscopic visualization, confirming intragastric positioning.
Results:
Enteral feeding began the same day, and recovery was uneventful. Laparoscopic-assisted PEG enabled safe gastrostomy placement after multiple failed approaches.
Conclusions:
Laparoscopic-assisted PEG is a minimally invasive alternative that avoids the morbidity of formal surgical gastrostomy when PEG or radiologic interventional gastrostomy are not feasible.
