Related Experiment Video
Updated: Oct 26, 2026
Endoscopic Third Ventriculostomy and Pineal Biopsy from a Single Entry Point
Published on: June 28, 2024
Anatomical and clinical characteristics of pediatric endoscopic third ventriculostomy performed with a small-diameter
David Mesa Collantes1, Rosa María Maestre López2, Javier Manuel Saceda Gutiérrez3
1Department of Neurosurgery, Hospital Universitario Puerta del Mar, Cádiz, Spain. david.mesac97@gmail.com.

Background:
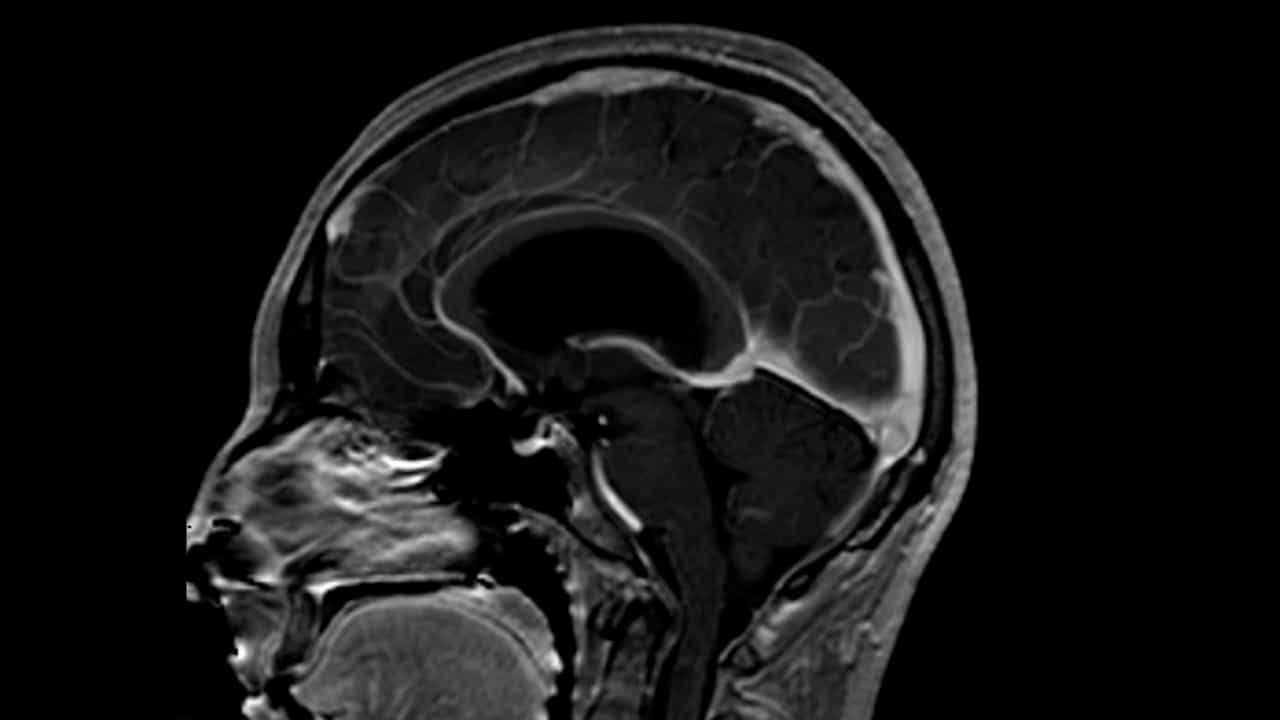
Endoscopic third ventriculostomy (ETV) is an established treatment for selected pediatric patients with obstructive hydrocephalus. Although the foramen of Monro constitutes the principal anatomical corridor to the third ventricle, its preoperative radiological characterization has been scarcely investigated. This study aimed to describe the radiological characteristics of the foramen of Monro in a consecutive pediatric ETV cohort treated with a small-diameter rigid neuroendoscope and to explore its relationship with ventricular morphology and clinical outcome.
Methods:
A retrospective observational study was performed including the complete consecutive series of 17 pediatric patients who underwent ETV at our institution between March 2022 and November 2024. All procedures were performed using the PaediScope® neuroendoscope. The radiological diameter of the right foramen of Monro was measured on axial T2-weighted MRI together with the Evans Index and third ventricular diameter. Clinical, radiological, and operative variables were retrospectively collected. Correlations between radiological parameters and clinical outcome were analyzed using non-parametric statistical methods.
Results:
The mean radiological diameter of the right foramen of Monro was 2.79 ± 0.81 mm. Moderate positive correlations were observed between the foramen of Monro diameter and the preoperative Evans Index (ρ = 0.588, p = 0.013), preoperative third ventricular diameter (ρ = 0.606, p = 0.010), and postoperative third ventricular diameter (ρ = 0.568, p = 0.017). No significant association was found between the radiological diameter of the foramen of Monro and the subsequent requirement for definitive ventriculoperitoneal shunt placement or postoperative ventricular reduction. Three patients (17.6%) required definitive ventriculoperitoneal shunting during the available clinical follow-up. These patients had significantly lower Endoscopic Third Ventriculostomy Success Scores than patients who maintained ETV function (p = 0.016). Intraoperative visualization was good in 16/17 procedures and moderate in one, and no major intraoperative complications were recorded.
Conclusions:
The radiological measurement of the foramen of Monro correlated with ventricular morphology but was not associated with clinical outcome after pediatric ETV. Rather than representing the true anatomical diameter of the surgical corridor, this measurement should be interpreted as a standardized radiological descriptor of ventricular anatomy. The small diameter neuroendoscope was technically applicable across the range of ventricular anatomy represented in this complete consecutive cohort, although the absence of a comparator precludes conclusions regarding device-specific benefit. The study demonstrates the feasibility of obtaining this measurement from routine preoperative MRI and provides preliminary anatomical data that may support future prospective studies evaluating technical planning for pediatric ventricular endoscopy.