Tailored Strategy for Laparoscopic Anatomical Extended Right Posterior Sectionectomy Including the Dorsal Right
Jimin Son1, Ji Hoon Kim2,3
1Center for Liver and Pancreatobiliary Cancer, National Cancer Center, Ilsandonggu, Goyang-si, Gyeonggi-do, Korea.

Background:
Laparoscopic extended right posterior sectionectomy (eRPS), including the dorsal segment of the right anterior section (RAS), is a technically demanding but parenchyma-preserving alternative to right hepatectomy. Its success depends on accurate identification of the anatomically variable intersegmental plane. This study describes a tailored Glissonean approach according to the presence or absence of the anterior fissure vein (AFV).
Patients And Methods:
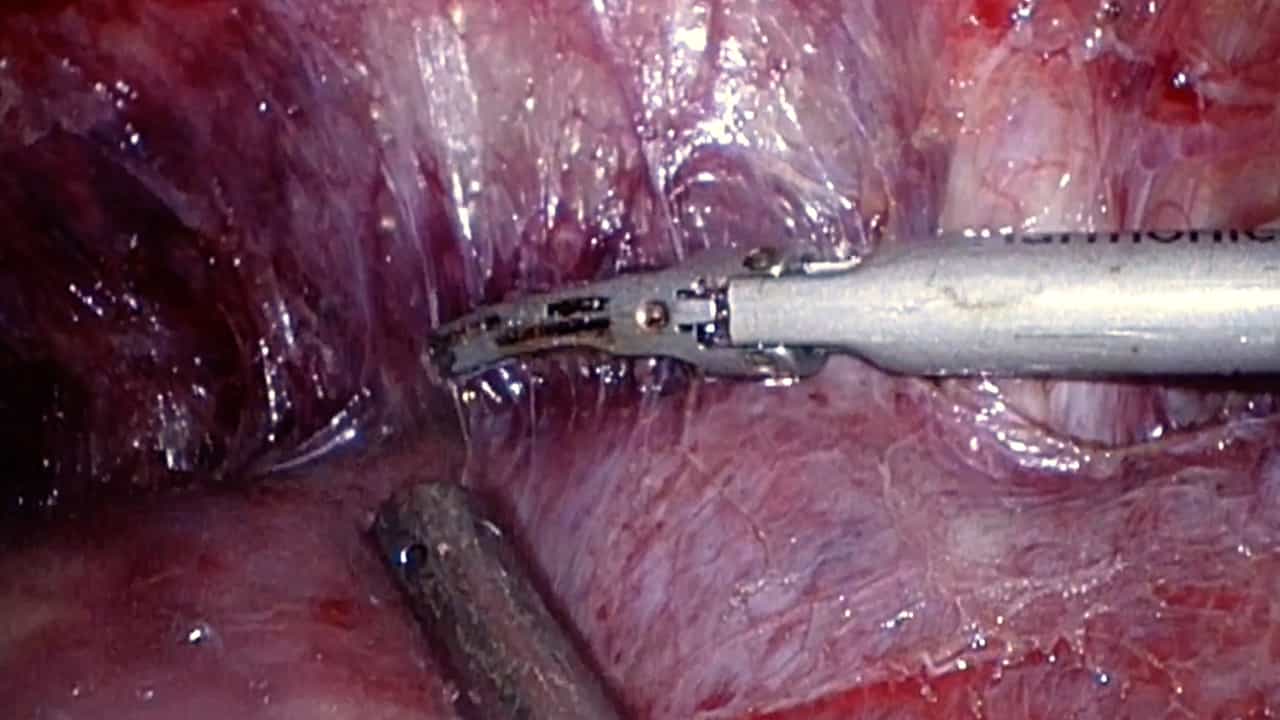
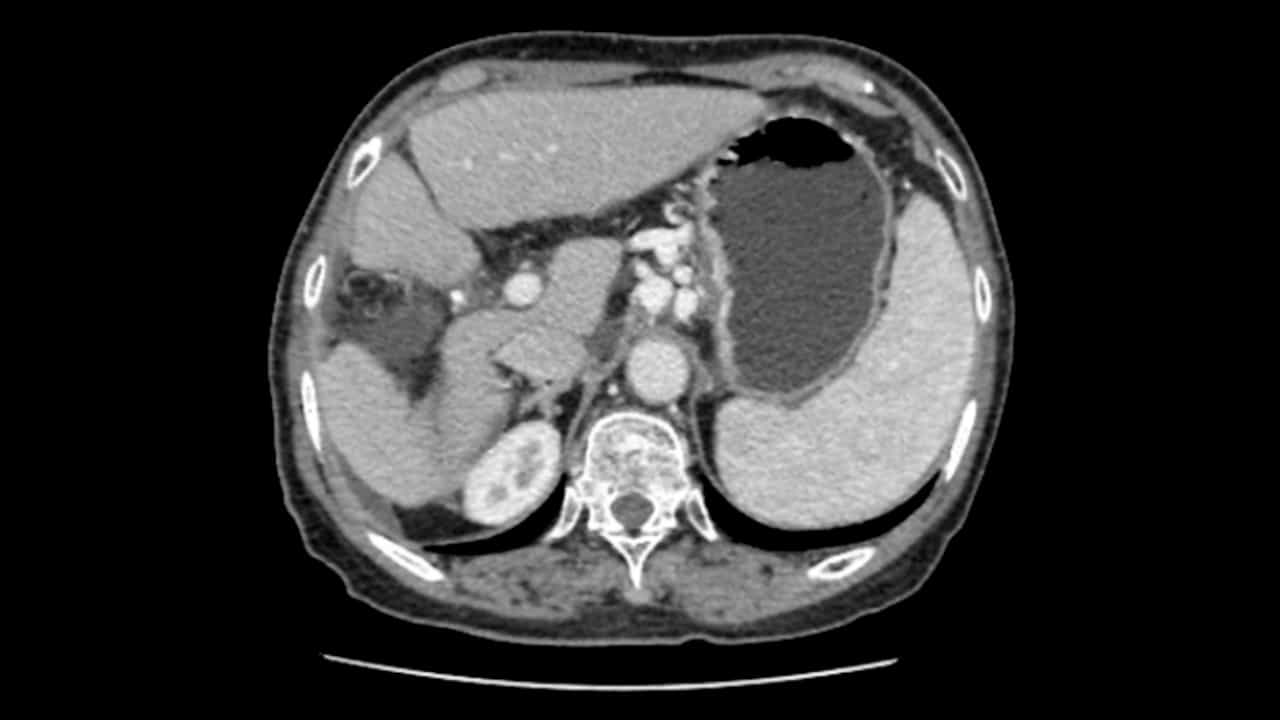
Between December 2020 and July 2023, six consecutive patients underwent laparoscopic eRPS including the dorsal RAS. Preoperative three-dimensional (3D) reconstruction was used to evaluate the right anterior Glissonean pedicle (RAG) branching pattern and presence of a definite AFV. When an AFV was identified, an AFV-guided transfissural approach was used; when absent, an intrahepatic Glissonean approach using the RAG as an intraparenchymal landmark was performed. Indocyanine green (ICG) fluorescence confirmed the ischemic boundary after target pedicle ligation.
Results:
Median operative duration was 260 min and median blood loss was 175 mL, with no transfusions. A definite AFV was identified in five of six patients (83.3%). Median tumor size was 31 mm (range 15-52 mm), and all cases achieved R0 resection. Median hospital stay was 6.5 days (range 5-21 days). One patient (16.7%) experienced postoperative ileus, with no perioperative mortality.
Conclusions:
A tailored Glissonean approach guided by preoperative 3D reconstruction and complemented by ICG fluorescence provides a practical framework for laparoscopic eRPS. Careful case selection remains essential.