Related Experiment Video
Updated: Oct 26, 2026
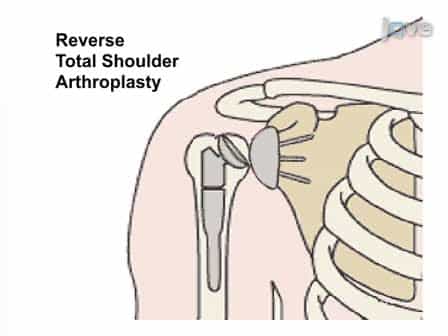
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Comparing outcomes of onlay humeral stem designs in reverse total shoulder arthroplasty: a systematic review
Nicholas Daher1, Mahdi Mazeh1, Joshua P Castle1
1Henry Ford Health, Detroit, MI, USA.

Background:
Since the development of the original Grammont implant, reverse shoulder arthroplasty (rTSA) has evolved, with onlay and inlay humeral designs emerging as the 2 main options. Onlay designs have gained popularity due to modularity and adaptability, allowing conversion from anatomic total shoulder arthroplasty to rTSA. While differences in medialization and lateralization of the glenoid and humeral stem have been studied, little is known about the impact of these features in various onlay implants. This systematic review aims to compare the clinical outcomes of lateralized humeral (LH) and medialized humeral (MH) onlay designs in rTSA.
Methods:
The review followed Preferred Reporting Items for Systematic Reviews and Meta-Analyses guidelines. A comprehensive search was conducted in PubMed, Ovid MEDLINE, Embase, and Web of Science to identify studies comparing clinical outcomes of onlay designs. The primary outcomes of interest were patient-reported outcomes and shoulder range of motion.
Results:
Of 1,005 studies reviewed, 14 met the inclusion criteria, including 14,427 patients. Range of motion comparisons revealed no significant difference in forward flexion between LH and MH designs (135.08° vs. 137.07°, P = .2929). Similarly, abduction did not significantly differ (113.02° vs. 116.42°, P = .1387). Both internal rotation and external rotation were significantly greater in the LH group (6.62 vs. 5.84, P = .0063) (41.21° vs. 31.94°, P < .0001), respectively. American Shoulder and Elbow Surgeons scores were higher in the LH group (77.89 vs. 75.33, P = .255), though not statistically significant. Visual analog scale pain scores were significantly lower in the LH group (0.724 vs. 1.613, P = .0015). Conversely, the MH group demonstrated significantly higher Constant scores (66.51 vs. 60.37, P < .0001). Complication rates were significantly higher in the MH group (13.8%) compared to the LH group (2.0%) (P < .001; χ2 test).
Conclusion:
The LH and MH configurations for onlay rTSA demonstrate distinct domain-specific advantages. LH implants were associated with significantly lower visual analog scale pain scores (0.724 vs. 1.613; P = .0015), superior internal rotation (6.62 vs. 5.84; P = .0063), and markedly greater external rotation (41.21° vs. 31.94°; P < .0001). However, only the external rotation difference exceeded the Minimal Clinically Important Difference. MH implants demonstrated higher Constant scores (66.51 vs. 60.37; P < .0001), though forward flexion and abduction did not significantly differ between groups. Importantly, complication rates were significantly higher in the MH group (13.8% vs. 2.0%; P < .0001). These nuanced differences underscore the importance of individualized surgical planning.