Related Experiment Video
Updated: Oct 26, 2026
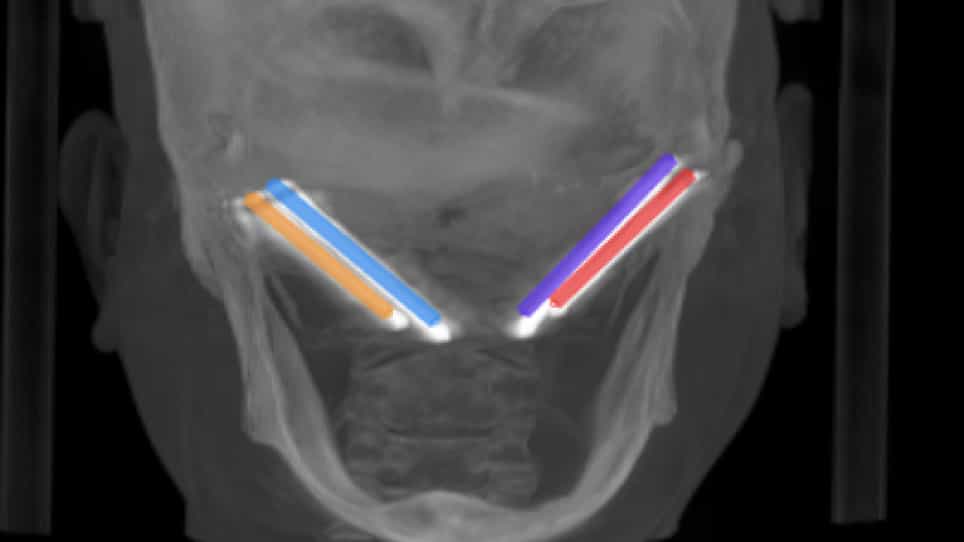
Real-Time Dynamic Navigation System for the Precise Quad-Zygomatic Implant Placement in a Patient with a Severely Atrophic Maxilla
Published on: October 18, 2021
Short Implants Versus Sinus Floor Elevation With Standard Implants in the Atrophic Posterior Maxilla: A Systematic
Salma Abdallaoui Maane1, Cesar Muelas Sanchez1, Manuel Lanciego1
1Periodontics, Implantology, and Oral Surgery, Universidad San Pablo CEU, Madrid, ESP.

Abstract:
Posterior maxillary atrophy is a significant challenge in implant dentistry because of limited subantral bone height and proximity to the maxillary sinus. The two main therapeutic options are sinus floor elevation with standard implants (>8 mm) and short implants (≤6 mm). This systematic review and meta-analysis compared both techniques in terms of implant survival, marginal bone loss, and complication rates, following Preferred Reporting Items for Systematic Reviews and Meta-Analyses (PRISMA) 2020 guidelines. Electronic searches were conducted in PubMed/MEDLINE, Scopus, Web of Science, and Cochrane Central, including randomized controlled trials with at least one-year follow-up, published between 2014 and 2025. Eligibility was deliberately restricted to trials in which the control arm involved sinus floor elevation, excluding studies that compared short implants with longer implants placed in native bone of adequate height or in bone augmented by other techniques. Four publications corresponding to three independent cohorts were included (174 randomized patients); a fifth report of one of these cohorts could not be retrieved and contributes no data. All data were re-extracted in duplicate directly from the source publications. Survival was analyzed at the patient level; one cohort recorded no implant failures in either arm and therefore contributes no information to a risk ratio (RR), leaving 154 patients (83 short implants/71 standard implants) in the primary pooled analysis. Cumulative patient-level survival across the three cohorts was 97.8% for short implants and 98.8% for standard implants. Meta-analysis yielded a pooled RR of 1.00 (95% CI: 0.56-1.76, Hartung-Knapp adjustment; unadjusted interval 0.91-1.09, p = 0.92). On the failure scale, three failures occurred in total, 2/93 with short implants and 1/81 with standard implants, giving a Peto odds ratio of 1.70 (95% CI: 0.17-16.86). Substantial between-study heterogeneity was present (I² = 59%), with the two pooled cohorts pointing in opposite directions: 100% versus 95.0% in one and 96.0% versus 100% in the other. Marginal bone loss favored short implants in one cohort by a margin below clinical relevance and did not differ between groups in the other; the data were not pooled because radiographic methods and reporting formats differed across trials. Biological complications were consistently less frequent with short implants, with every failure recorded in a standard-implant arm attributable to graft-related complications. The review cannot determine whether the two techniques differ in implant survival. With three failures among 174 randomized patients and two contributing trials, the confidence interval is compatible with a substantial advantage to either approach. The most consistent finding concerns morbidity rather than survival.