Related Experiment Video
Updated: Oct 26, 2026
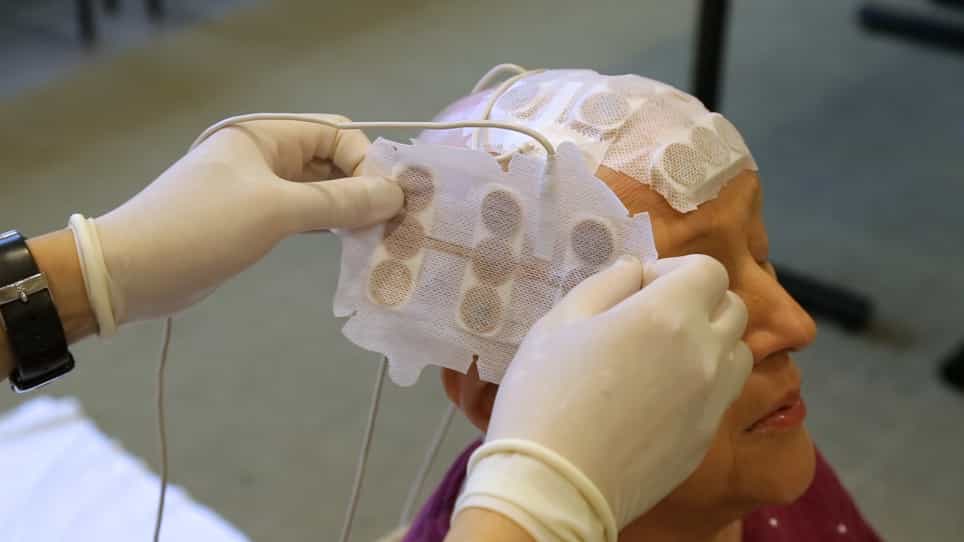
The Clinical Application of Tumor Treating Fields Therapy in Glioblastoma
Published on: April 16, 2019
Protective effects of testosterone replacement therapy on brain tumor outcomes: The Mayo Clinic experience
Manuel M Bettencourt1, Shreya Gandhi1,2,3, Archis Bhandarkar1
1Department of Neurologic Surgery, Mayo Clinic, Rochester, Minnesota, USA.

Background:
Biological sex and endocrine signaling influence cancer biology, immune response, and therapeutic outcomes. Recent evidence suggests that testosterone signaling may exert brain-context-dependent protective effects in glioblastoma (GBM) through the hypothalamic-pituitary-adrenal axis, reduced glucocorticoid-mediated immune suppression, and altered tumor-immune interactions. We assessed whether testosterone replacement therapy (TRT) exposure was associated with survival in solid tumor central nervous system (CNS) metastases and glioblastoma (GBM, IDH-wildtype, WHO grade 4), settings in which post-diagnosis survival and TRT timing can be clinically defined.
Methods:
We performed a retrospective Mayo Clinic cohort study of adult patients with molecularly confirmed GBM and solid tumor CNS metastases confirmed from neuroimaging reports using large language model-assisted adjudication. TRT exposure was defined by testosterone-specific prescription evidence within prespecified peri-diagnostic windows. Overall survival was evaluated using propensity score-matched Cox models, 24-month administratively censored Cox models, time-dependent Cox sensitivity analyses, and 24-month restricted mean survival time.
Results:
In the pooled solid tumor CNS metastasis cohort, TRT exposure was associated with improved overall survival after propensity score matching (HR 0.80, 95% CI, 0.65-0.98, P = .029) and a 3.22-month improvement in 24-month restricted mean survival time. In GBM, TRT exposure was similarly associated with improved overall survival after propensity score matching (HR 0.38, 95% CI, 0.14-0.98, P = .046) and a 5.81-month improvement in 24-month restricted mean survival time.
Conclusions:
TRT exposure was associated with improved survival in CNS metastases and glioblastoma. These hypothesis-generating findings support prospective studies incorporating TRT timing, hormone levels, corticosteroid exposure, immune correlates, and tumor-specific stratification.
