Related Experiment Video
Updated: Oct 27, 2026

Robot-assisted Total Mesorectal Excision and Lateral Pelvic Lymph Node Dissection for Locally Advanced Middle-low Rectal Cancer
Published on: February 12, 2022
[Organ-preserving hemipelvic exenteration for low locally advanced rectal cancer]
1Department of Colorectal Surgery, The Second Affiliated Hospital of Naval Medical University (Shanghai Changzheng Hospital), Shanghai 200003, China.

Abstract:
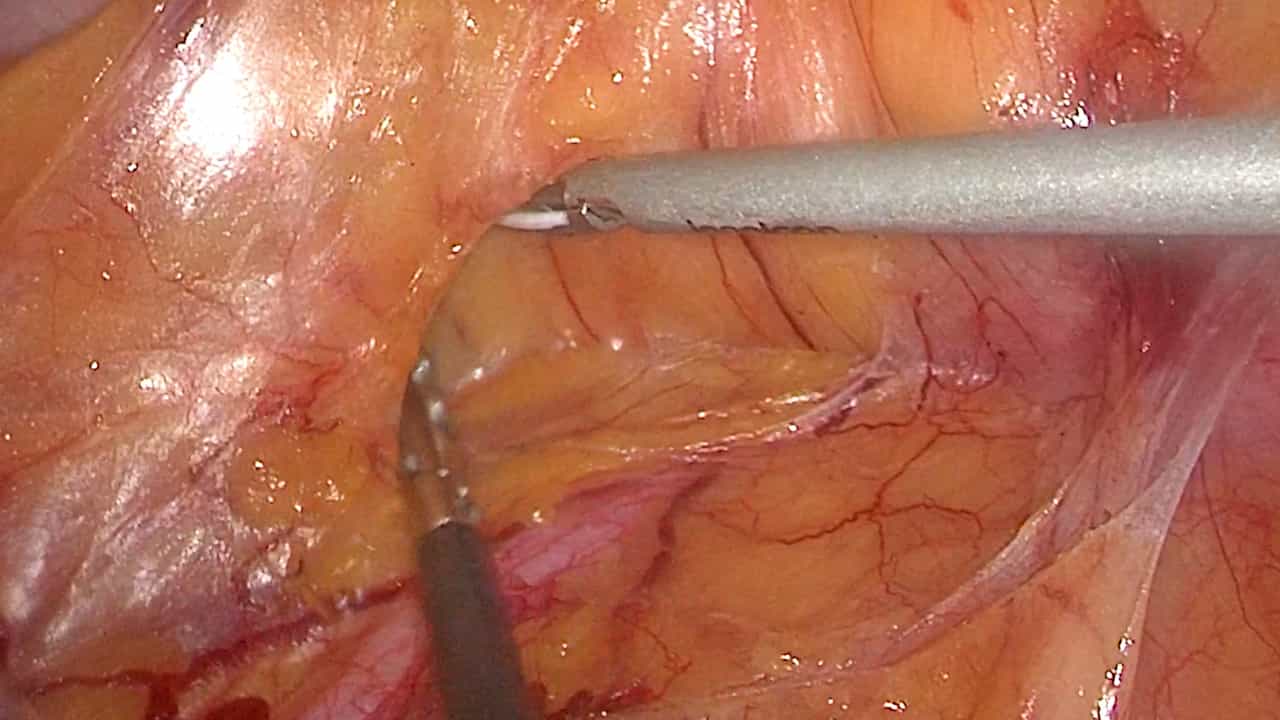
Objective: To investigate the safety and clinical feasibility of hemi-pelvectomy in the treatment of low locally advanced rectal cancer. Methods: The surgical procedure comprised the following steps: (1) Laparoscopic exploration: no gross abnormalities were observed in the abdominopelvic peritoneum, liver, gallbladder, stomach, small intestine, or mesentery. (2) Open surgery: via the Marcille triangle approach, sequential resections were performed, including lateral pelvic wall resection, presacral dissection, pelvic floor resection, and intrapelvic lesion excision. En bloc resection encompassed the "low rectum + uterus/cervix + left hemipelvis (complete resection of the pelvic plexus nerves, with preservation of the left superior vesical artery and left S1-S5 nerve roots) + anterior S3/S4 presacral tissue," while the right pelvic plexus nerves were completely preserved. (3) Tissue reconstruction and pelvic wound closure: a modified Bacon procedure was employed for digestive tract reconstruction, a pedicled omental flap was used to isolate the anastomotic sites, and a biological mesh was applied to separate the abdominopelvic cavity. (4) Second-stage surgery: the prolapsed bowel segment was resected one month postoperatively.A retrospective analysis was performed on the clinical data (including the intra- and postoperative, and follow-up outcomes of the patients) of a 25-year-old female patient with low locally advanced rectal cancer who underwent hemi-pelvectomy at the Department of Colorectal Surgery, The Second Affiliated Hospital of Naval Medical University in November 2024. Results: The patient underwent an uneventful operation, with an operative time of approximately 6.5 hours and an estimated blood loss of approximately 400 ml. No intraoperative blood transfusion was required, and the patient returned safely to the general ward postoperatively. Postoperative pathology confirmed R0 resection, and no additional adjuvant chemoradiotherapy was administered. Postoperative recovery was favorable, with no severe complications such as abdominopelvic infection, empty pelvis syndrome (EPS), or intestinal obstruction. A second-stage operation was performed at 1 month postoperatively to resect the prolapsed bowel. At 6 months postoperatively, bladder function was normal, the Williams anal function score was grade B, and the quality-of-life score returned to the preoperative baseline. At 12 months postoperatively, the patient had 1-4 bowel movements per day and reported good satisfaction. At 18 months postoperatively, molecular residual disease (MRD) testing remained persistently negative, with no evidence of local recurrence. Conclusion: This preliminary experience suggests that hemi-pelvectomy for low locally advanced rectal cancer demonstrates acceptable clinical feasibility and safety.