Related Experiment Video
Updated: Oct 27, 2026
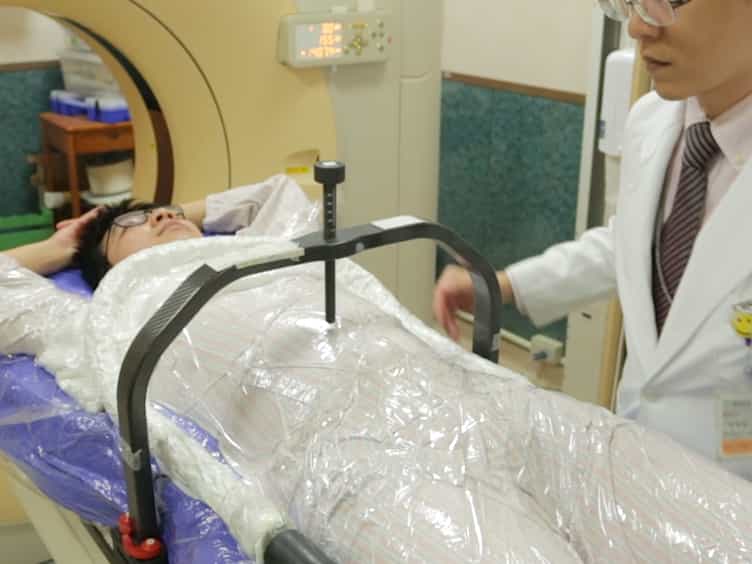
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Prognostic stratification by the ESTRO/EORTC oligometastatic classification and simplified binary approaches in lung
Dan Yao1, Xue-Ru Zhu1, Jin-Dong Guo1
1Department of Radiation Oncology, Shanghai Chest Hospital, School of Medicine, Shanghai Jiao Tong University, Shanghai, 200030, China.

Background:
The ESTRO/EORTC classification categorizes oligometastatic disease (OMD) into de-novo, repeat, and induced OMD based on prior disease history and treatment status. However, its prognostic relevance in lung cancer patients treated with stereotactic ablative radiotherapy (SABR) remains incompletely characterized in real-world settings. This study evaluated the ESTRO/EORTC classification and two simplified binary stratification approaches derived from its decision framework.
Methods:
This single-center retrospective study included 648 lung cancer patients with 1-5 metastases treated with SABR between 2015 and 2021. Patients were categorized according to the ESTRO/EORTC classification. Two simplified binary stratification approaches derived from the ESTRO/EORTC decision framework were additionally explored: (1) a history-based approach distinguishing patients with prior polymetastatic disease from those without, and (2) a therapy-dependent progression approach distinguishing oligometastatic progression during active systemic therapy from other OMD states. Survival outcomes were analyzed using Kaplan-Meier and Cox regression, and prognostic discrimination was assessed using Harrell's C-index.
Results:
With a median follow-up of 54.5 months, 325 deaths and 552 progression events were observed. Induced OMD was associated with significantly worse outcomes compared with de-novo OMD (OS: 35.7 vs. 68.9 months; PFS: 8.6 vs. 15.5 months; both p < 0.001) and repeat OMD (OS: 35.7 vs. 60.2 months; PFS: 8.6 vs. 14.4 months; both p < 0.001). No significant differences were observed between de-novo and repeat OMD. The therapy-dependent progression stratification approach demonstrated distinct survival separation (median OS 34.4 vs. 86.4 months; PFS 8.4 vs. 16.4 months; both p < 0.001), although the difference in discriminatory performance was modest (C-index 0.596 for OS) compared with the ESTRO/EORTC classification (0.565) and the history-based approach (0.563). Differences in discriminatory performance were modest and not statistically significant after multiple-testing correction and bootstrap resampling.
Conclusions:
The ESTRO/EORTC classification is associated with survival outcomes in lung cancer patients with OMD treated with SABR, with induced OMD conferring the poorest prognosis. Simplified binary stratification approaches derived from this framework may provide a pragmatic and clinically accessible approach for risk stratification. These approaches should be considered complementary to, rather than replacements for, the full ESTRO/EORTC classification. Prospective validation is warranted.