Related Experiment Video
Updated: Oct 27, 2026
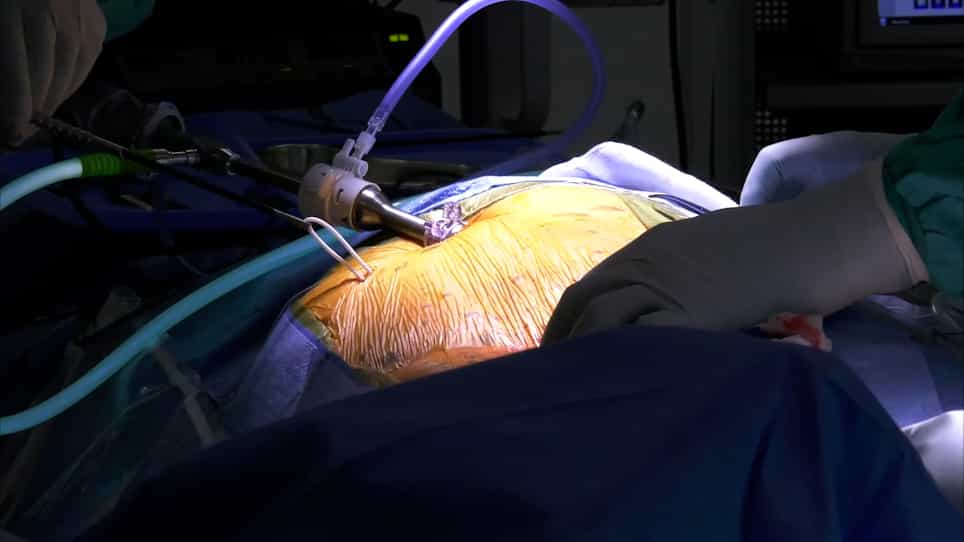
Neuronavigation and Laparoscopy Guided Ventriculoperitoneal Shunt Insertion for the Treatment of Hydrocephalus
Published on: October 14, 2022
Laparoscopic versus open approaches for ventriculoperitoneal shunt placement in children: a systematic review and
Shitong Hu1, Yehang Zhu2, Qingqing Deng3
1Department of Pediatrics, First Affiliated Hospital of Huzhou Normal University, Huzhou, 313000, China.

Purpose:
Ventriculoperitoneal (VP) shunt placement is the standard treatment for pediatric hydrocephalus. While the open approach has been traditionally used, laparoscopic-assisted techniques have gained increasing attention. This study aimed to compare the efficacy and safety of laparoscopic versus open approaches for VP shunt placement in children through a systematic review and meta-analysis.
Methods:
A systematic literature search was conducted in PubMed, Embase, Web of Science, and the Cochrane Library up to March 2026. Comparative studies evaluating laparoscopic versus open VP shunt placement in pediatric patients were included. Primary outcomes included operative time and length of hospital stay. Secondary outcomes included distal revision rate, overall revision rate, infection rate, and overall complications. Pooled mean differences (MD) and odds ratios (OR) with 95% confidence intervals (CI) were calculated using Review Manager 5.4.
Results:
A total of 8 studies involving 9184 patients (1151 laparoscopic and 8033 open) were included. There were no significant differences in operative time or length of hospital stay. The distal revision rate and infection rate were also comparable between groups. However, laparoscopic surgery was associated with a significantly lower overall revision rate (OR = 0.64, 95% CI: 0.45-0.92; P = 0.02) and fewer overall complications (OR = 0.62, 95% CI: 0.44-0.88; P = 0.008).
Conclusions:
Laparoscopic-assisted VP shunt placement is a safe and effective alternative to the open approach in pediatric patients. It may reduce overall revision rates and postoperative complications without increasing operative time or infection risk. Further high-quality prospective studies are needed to confirm these findings.