Related Experiment Video
Updated: Oct 27, 2026
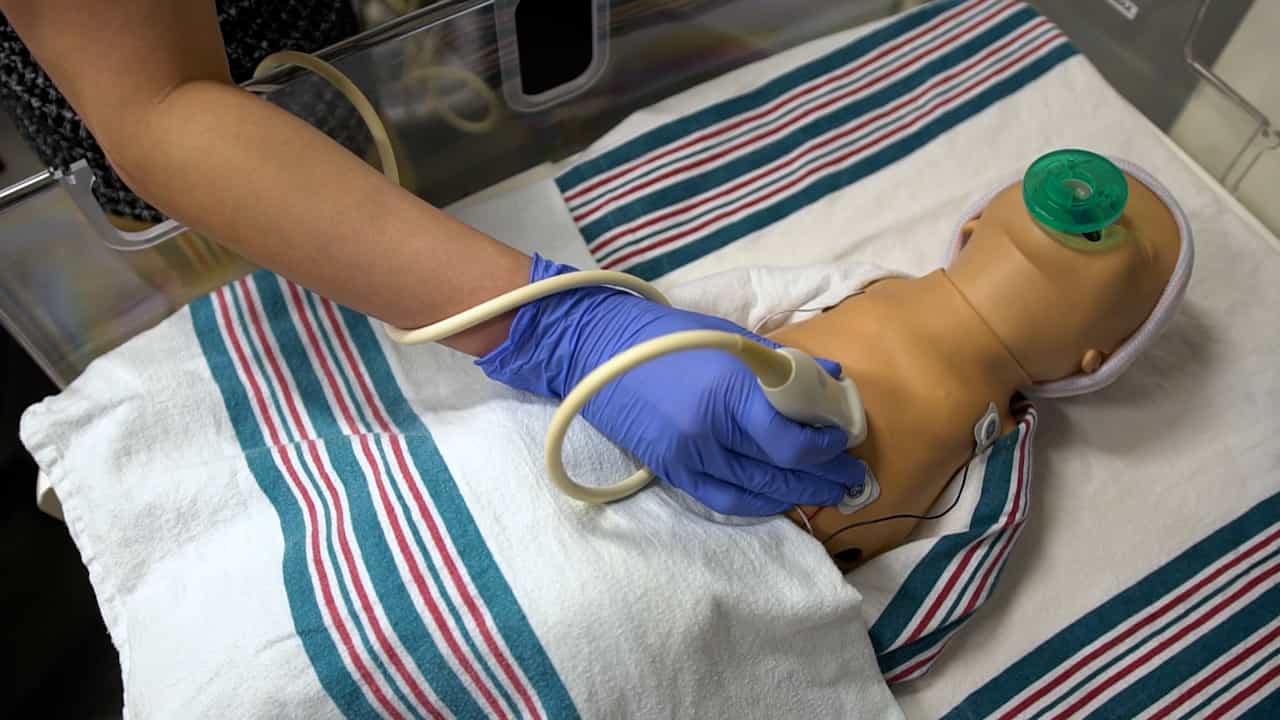
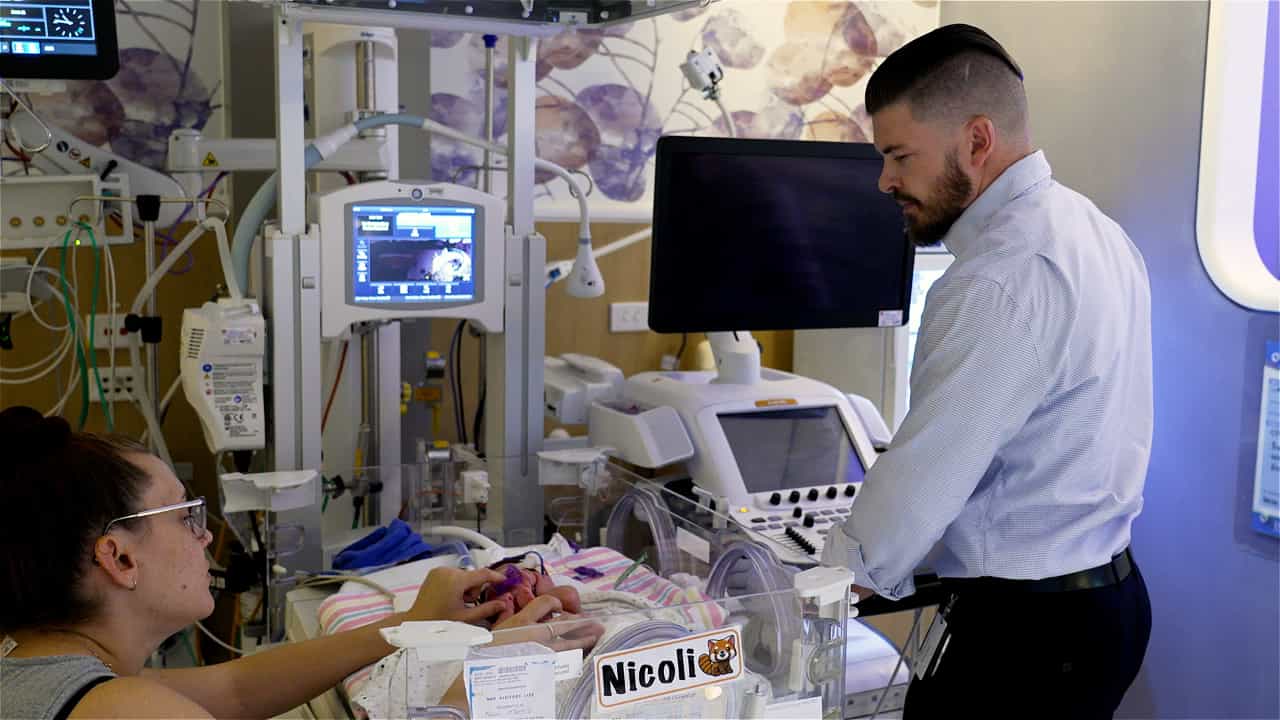
Hemodynamic Precision in the Neonatal Intensive Care Unit using Targeted Neonatal Echocardiography
Published on: January 27, 2023
Comparison of visual estimation of ventricular systolic function with quantitative echocardiographic markers in
Sujith S Pereira1,2, Beena Yeldo3, Rachael Fleming4
1Neonatal Unit, Homerton University Hospital, Homerton Healthcare NHS Foundation Trust, London, UK. s.s.pereira@qmul.ac.uk.

Background:
Neonatologist-performed echocardiography (NPE) is increasingly practiced. NPE operators typically use visual estimation of systolic function and, if indicated, confirm function using quantitative echocardiographic markers. This exploratory study aims to compare the concordance between qualitative and quantitative echocardiographic markers among NPE and non-NPE operators.
Methods:
We studied a cohort of newborn infants, undergoing routine NPE by the authors at Homerton University Hospital and Aberdeen Maternity Hospital from April 2024 to October 2024. Blinded NPE and non-NPE operators independently assessed left and right ventricular systolic function visually. We compared visual estimation with standard quantitative echocardiographic markers such as shortening fraction, Simpson's ejection fraction and global longitudinal strain for left ventricle and tricuspid annular plane systolic excursion and fractional area change for right ventricle. We examined the concordance between visual estimation and quantitative echocardiographic markers for biventricular systolic function.
Results:
Sixty infants with a mean (SD) gestation and birth weight of 34 (6.2) weeks and 2311 (1319) grams respectively were examined. Sensitivity testing for all echocardiographic parameters ranged from 25% to 80% whereas specificity ranged from 38% to 78%. Sensitivity increased with worsening grades of LV dysfunction defined using shortening fraction. While concordance between NPE and non-NPE operator was generally limited across most echocardiographic parameters, test-retest reliability was acceptable for several quantitative measures, including Simpson's ejection fraction, global longitudinal strain and right ventricular fractional area change.
Conclusion:
Visual estimation may be a useful bedside tool for detecting severe ventricular dysfunction in newborn infants; however; quantitative echocardiographic measures are likely to improve the assessment of mild to moderate dysfunction. Further studies should confirm these findings in a larger cohort with a higher representation of infants with ventricular dysfunction.