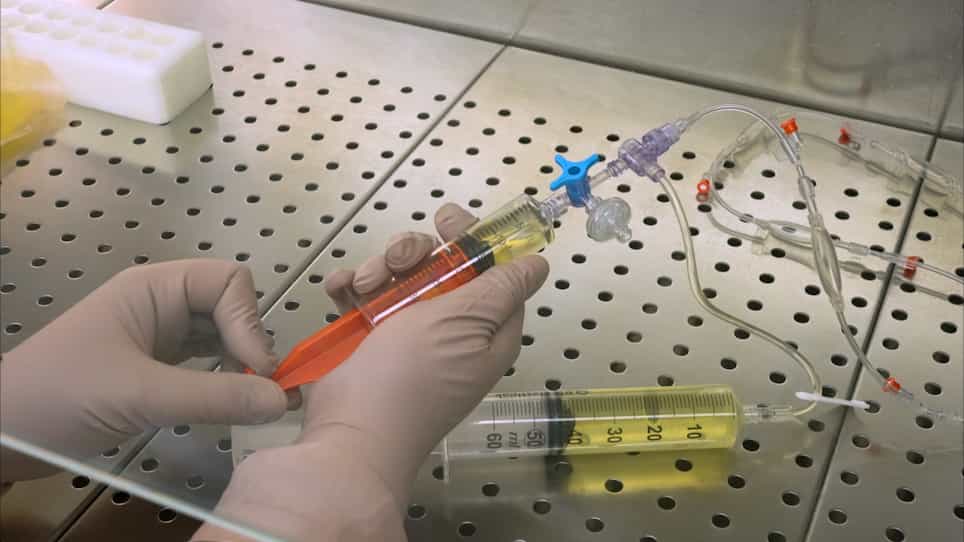
Related Experiment Video
Updated: Oct 27, 2026
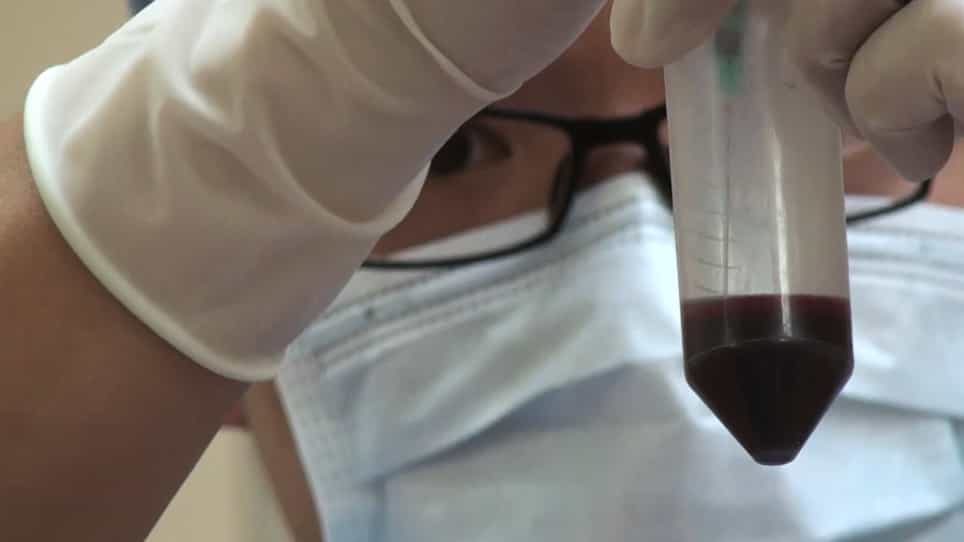
Preparation, Procedures and Evaluation of Platelet-Rich Plasma Injection in the Treatment of Knee Osteoarthritis
Published on: January 4, 2019
Clinical Pathway Management for Platelet-Rich Plasma Therapy in Kellgren-Lawrence Grade I and II Knee Osteoarthritis:
Shunjie Yang1,2,3, Hui Wang2,4,5, Yan Liu5
1Huaxi Magnetic Resonance Research Center, Institute of Radiology and Medical Imaging, Department of Radiology, West China Hospital, Sichuan University, Chengdu, China.

Background:
Clinical outcomes after platelet-rich plasma (PRP) treatment for knee osteoarthritis are inconsistent, and some well-designed trials show no benefit. Whether a standardized multicomponent pathway improves outcomes relative to conventional PRP care is uncertain.
Purpose:
To compare the efficacy, safety, satisfaction, and costs of a standardized PRP pathway versus physician-directed conventional PRP care in Kellgren-Lawrence grade I and II knee osteoarthritis.
Study Design:
Randomized controlled trial; Level of evidence, 1.
Methods:
At 3 hospitals, 240 patients were randomized 1:1 to a standardized PRP clinical pathway (PRP-CP; n = 120) or physician-directed conventional PRP care (PRP-C; n = 120). PRP-CP combined standardized selection, quality-controlled leukocyte-poor PRP, ultrasound-guided injections, staged rehabilitation, and systematic follow-up. Primary 12-month outcomes were visual analog scale (VAS) pain, Western Ontario and McMaster Universities Osteoarthritis Index (WOMAC) total, and International Knee Documentation Committee (IKDC) scores; secondary outcomes included achievement of the minimal clinically important difference, satisfaction, adverse events, and costs.
Results:
At 12 months, PRP-CP produced greater changes than PRP-C in VAS (mean difference [MD], -2.98 [95% CI, -3.64 to -2.32]), WOMAC total (MD, -8.63 [95% CI, -11.35 to -5.90]), and IKDC (MD, 10.25 [95% CI, 8.37 to 12.13]) scores (all P < .001). Achievement of the minimal clinically important difference favored PRP-CP at 3, 6, and 12 months for the VAS and at 6 and 12 months for the IKDC and WOMAC (P < .05). Satisfaction was greater with PRP-CP (odds ratio, 1.79 [95% CI, 1.11-2.89]; P = .017). An adverse event occurred in 17 of 115 patients in the PRP-CP group (14.8%) versus 36 of 113 patients in the PRP-C group (31.9%) (Fisher exact test: P = .003). Mean costs were CN¥15,199.9 versus CN¥14,754.4, respectively; the incremental cost-effectiveness ratio was CN¥66.0 per WOMAC point. Effects were generally consistent across centers, and blinding was maintained.
Conclusion:
The standardized multicomponent pathway produced greater 12-month improvements in pain and function than conventional PRP care, with fewer adverse events. Because components were bundled and no placebo group was included, the trial does not establish PRP efficacy or component-specific effects.