Related Experiment Video
Updated: Oct 27, 2026
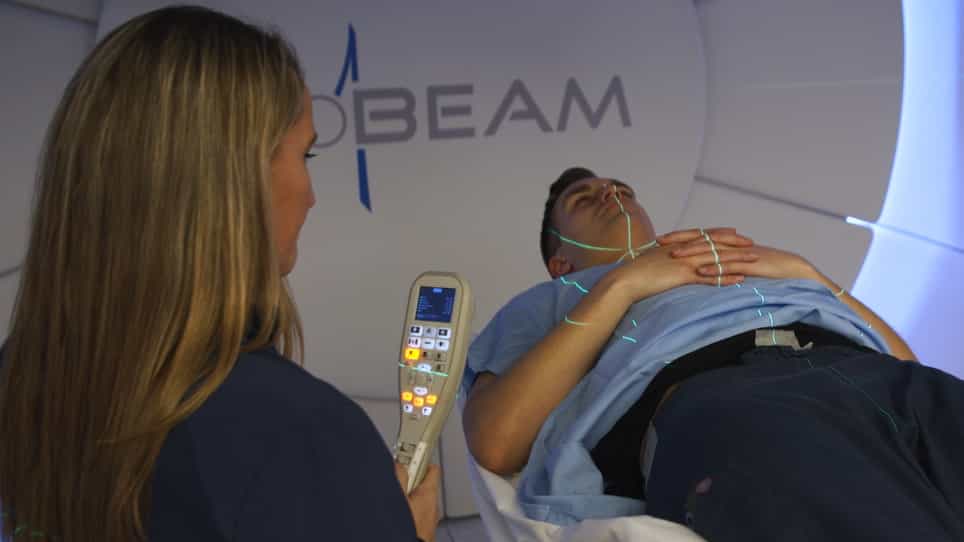
Proton Therapy Delivery and Its Clinical Application in Select Solid Tumor Malignancies
Published on: February 6, 2019
Secondary Intracranial Hypertension During ATRA/ATO Therapy in High-Risk Acute Promyelocytic Leukemia: A Case Report
Luca Roeh1,2, Nigel Schaeper1, Sebastian Schröder1
1Department of Hematology, Oncology and Tumor Immunology, Charité Campus Mitte, Charité-Universitätsmedizin Berlin, Corporate Member of Freie Universität Berlin and Humboldt-Universität zu Berlin, 10117 Berlin, Germany.

Abstract:
All-trans retinoic acid (ATRA) combined with arsenic trioxide (ATO) is the standard of care for acute promyelocytic leukemia (APL), including high-risk disease. Secondary intracranial hypertension (SIH), historically termed pseudotumor cerebri (PTC), is a recognized but uncommon and potentially therapy-limiting complication of retinoid exposure, reported predominantly in pediatric and young-adult patients and most frequently during induction. We report a 31-year-old man with high-risk microgranular APL in whom SIH was diagnosed during the first ATRA/ATO consolidation cycle. The clinical course included progressive headache, ocular pain, pulsatile tinnitus, focusing difficulties, visual deterioration, and diplopia. Ophthalmological assessment demonstrated bilateral papilledema with marked peripapillary retinal nerve fiber layer thickening despite preserved central visual acuity. Magnetic resonance imaging showed bilateral optic nerve sheath distension, prominent optic nerve heads, mild pituitary flattening, and bilateral transverse sinus stenosis. Lumbar puncture demonstrated an opening pressure of 32 cm H2O with otherwise unremarkable cerebrospinal fluid; removal of approximately 30 mL resulted in immediate symptomatic improvement. Management consisted of temporary ATRA interruption, therapeutic lumbar punctures, acetazolamide, and individualized ATRA rechallenge and dose titration. Repeated attempts at dose escalation reproduced symptoms, and ATRA was ultimately maintained at a maximally tolerated dose of 30 mg/m2/day while full-dose ATO was continued. Molecular remission was achieved after the first consolidation cycle and remains sustained at 18-month follow-up. This case highlights the importance of recognizing ATRA-associated SIH throughout the treatment course and illustrates a pragmatic strategy for preserving ATRA exposure when standard-dose treatment is limited by neurological toxicity. However, the oncological equivalence of reduced-dose ATRA cannot be inferred from a single case.
