Related Experiment Video
Updated: Oct 28, 2026
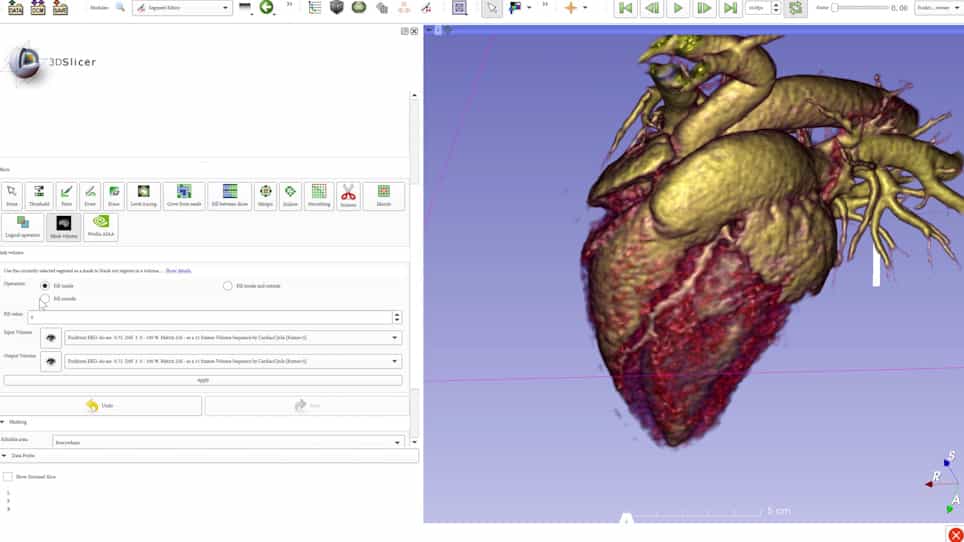
Four-Dimensional Computed Tomography-Guided Valve Sizing for Transcatheter Pulmonary Valve Replacement
Published on: January 20, 2022
Coexisting Moderate-to-Severe Tricuspid Regurgitation and Renal Dysfunction Identify a High-Risk Group After
Philipp Lauten1,2, Birgit Markus1, Georgios Chatzis1
1Department of Cardiology, Angiology, and Intensive Care Medicine, Philipps-Universität Marburg, Baldingerstraße, 35043 Marburg, Germany.

Background:
Moderate-to-severe tricuspid regurgitation (TR) and renal dysfunction are each associated with adverse outcomes after transcatheter aortic valve replacement (TAVR). We investigated whether their coexistence identifies a clinically relevant high-risk group.
Methods:
In this retrospective two-centre cohort, patients undergoing TAVR were classified into four groups according to moderate-to-severe TR and preprocedural estimated glomerular filtration rate < 45 mL/min/1.73 m2. The primary outcome was one-year all-cause mortality. Multivariable logistic regression adjusted for prespecified clinical covariates, and multiplicative interaction between TR and renal dysfunction was assessed.
Results:
Among 2227 patients, 1456 had neither condition, 324 isolated renal dysfunction, 315 isolated TR, and 132 both conditions. Patients with the combined phenotype had the highest rates of in-hospital mortality, 30-day mortality, acute kidney injury, and renal replacement therapy (all p < 0.001). One-year mortality increased progressively across groups (6.7%, 10.6%, 11.3%, and 22.9%; p < 0.001). After adjustment (n = 1704), the combined phenotype was associated with higher one-year mortality compared with neither condition (OR 2.91, 95% CI 1.62-5.23; p < 0.001), isolated TR (OR 2.17, 95% CI 1.16-4.07; p = 0.015), and isolated renal dysfunction (OR 2.32, 95% CI 1.16-4.61; p = 0.017). No significant multiplicative interaction was observed (p = 0.187).
Conclusions:
Coexisting moderate-to-severe TR and renal dysfunction identify a clinically relevant high-risk group after TAVR, with higher adjusted one-year mortality than either condition alone. Combined assessment of TR and renal function may improve preprocedural risk stratification.
Related Concept Videos
 01:25
Aortic Regurgitation III: Medical Management
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:25
Mitral Regurgitation III: Medical Management
 01:17
Aortic Regurgitation IV: Nursing Management
 01:20
Mitral Regurgitation I: Introduction