Related Experiment Video
Updated: Oct 28, 2026
Clinical Efficacy of Ultrasound-Assisted Scoliosis-Specific Exercise in Mild-Grade Adolescent Idiopathic Scoliosis
Published on: December 2, 2025
Does Inspiratory Lung Volume Help Explain the Association Between Thoracic Deformity and Pulmonary Dysfunction in
Kun Wang1,2, Yong Sun1,2, Wentao Wang1,2
1The Second Clinical Medical College, Lanzhou University, Lanzhou, PR China.

Background:
Adolescent idiopathic scoliosis (AIS) is often associated with restrictive pulmonary dysfunction, but the mechanistic pathway linking thoracic deformity to impaired lung function remains unclear. Although prior studies have used dynamic MRI to assess lung volumes or chest-wall motion, it remains unclear how MRI-derived lung volumes relate to three-dimensional thoracic deformity and pulmonary function and whether inspiratory lung volume accounts for part of these associations.
Questions/Purposes:
(1) What are the pulmonary function and dynamic lung volume characteristics in patients with AIS? (2) What are the spinal and thoracic deformity characteristics in patients with AIS? (3) What are the associations among spinal and thoracic deformity, dynamic lung volume, and pulmonary function? (4) Does total inspiratory lung volume help explain the association between thoracic deformity parameters and pulmonary function?
Methods:
In this retrospective cross-sectional study, all patients were evaluated before surgery and were candidates for surgical correction at the time of study inclusion. Of 183 patients with AIS screened, 62.3% (114) met the inclusion criteria and were included (age range 10 to 18 years; 72.8% [83 of 114] female). All patients underwent standing radiographs, low-dose chest CT, dynamic chest MRI at end inspiration and end expiration, and pulmonary function testing. Patients were classified into two groups: those with restrictive dysfunction (61% [69]) and those with normal pulmonary function (39% [45]). There were no differences between the groups in age, sex, or BMI. Deformity parameters included the main thoracic curve Cobb angle, main thoracic curve rib-vertebral angle difference, space available for lung, posterior hemithoracic symmetry ratio, thoracic rotation, and sagittal diameter. Lung volumes (right, left, total) were reconstructed from MRI. Because several continuous variables were not normally distributed, we used the Mann-Whitney U test to compare the two groups for pulmonary function, lung volumes, and deformity parameters. We assessed correlations among these variables using Spearman analysis. We performed mediation analysis with 5000 bootstrap resamples to evaluate whether inspiratory lung volume helps explain the association between thoracic deformity and pulmonary function. Mediation analysis tested the role of an intermediate factor in the relationship between two variables.
Results:
Data are presented as medians (range) unless otherwise specified. Of the 114 patients, 61% (69) had restrictive ventilatory dysfunction and 39% (45) had normal pulmonary function. Patients with restrictive ventilatory dysfunction had lower percent predicted forced vital capacity (FVC%) (median [range] 68% [36% to 80%] versus 90% [81% to 117%], difference of medians -22 percentage points; p < 0.001) and percent predicted forced expiratory volume in 1 second (FEV1%) (66% [30% to 87%] versus 87% [81% to 106%], difference of medians -21 percentage points; p < 0.001). Total median (range) inspiratory and expiratory lung volumes were also lower (2168 mL [1012 to 4733] versus 2807 mL [1012 to 4716], difference of medians -639 mL; p < 0.001 and 1300 mL [400 to 2899] versus 1604 mL [793 to 3161], difference of medians -304 mL; p = 0.006), but we could not demonstrate a difference in total inspiratory-expiratory volume change (767 mL [185 to 2622] versus 1002 mL [219 to 2889], difference of medians -235 mL; p = 0.32). They also had greater median [range] main thoracic Cobb angles (86° [42° to 121°] versus 54° [41° to 81°], difference of medians 32°; p < 0.001), greater main thoracic rib-vertebral angle differences (52° [16° to 78°] versus 17° [2° to 40°], difference of medians 35°; p < 0.001), and smaller sagittal thoracic diameters (69 mm [38 to 148] versus 88 mm [56 to 144], difference of medians -19 mm; p = 0.04). Because this study did not establish patient-level thresholds for MRI-derived lung volumes or thoracic measurements, the clinical importance of these differences remains uncertain. Greater rib-vertebral asymmetry was associated with lower FVC% and FEV1% (rs = -0.84 and -0.81, respectively; both adjusted p < 0.001), whereas larger total inspiratory lung volume was associated with higher FVC% and FEV1% (rs = 0.65 and 0.59, respectively; both adjusted p < 0.001). Thus, pulmonary function was related to both thoracic shape and inspiratory lung volume, but whether these measurements improve clinical assessment was not evaluated. Total inspiratory lung volume accounted for part of the observed relationship between thoracic deformity and pulmonary function. For FVC%, indirect effects were observed for the main thoracic Cobb angle (-0.15 [95% confidence interval (CI) -0.28 to -0.004]), thoracic rotation (-0.20 [95% CI -0.40 to -0.06]), and sagittal thoracic diameter (0.24 [95% CI 0.12 to 0.36]), with mediation proportions of 38.6%, 26.9%, and 76.6%, respectively; for FEV1%, an indirect effect was observed only for thoracic rotation (-0.16 [95% CI -0.40 to -0.04]; mediation proportion 20.4%). Because all measurements were obtained at one time point, these findings do not show that reduced inspiratory lung volume causes poorer pulmonary function.
Conclusion:
In patients with AIS, greater thoracic deformity was associated with smaller lung volumes and poorer pulmonary function. Mediation analysis suggested that total inspiratory lung volume partly accounted for the association between thoracic deformity and pulmonary function. As a radiation-free imaging modality, dynamic MRI may complement radiographic deformity assessment and routine pulmonary function testing by quantifying inspiratory and expiratory lung volumes across the respiratory cycle. Prospective longitudinal validation using posture-matched imaging and pulmonary function testing, including postoperative follow-up, is needed to determine whether these measurements improve clinical assessment and treatment planning.
Level Of Evidence:
Level III, prognostic study.

Related Concept Videos
 01:15
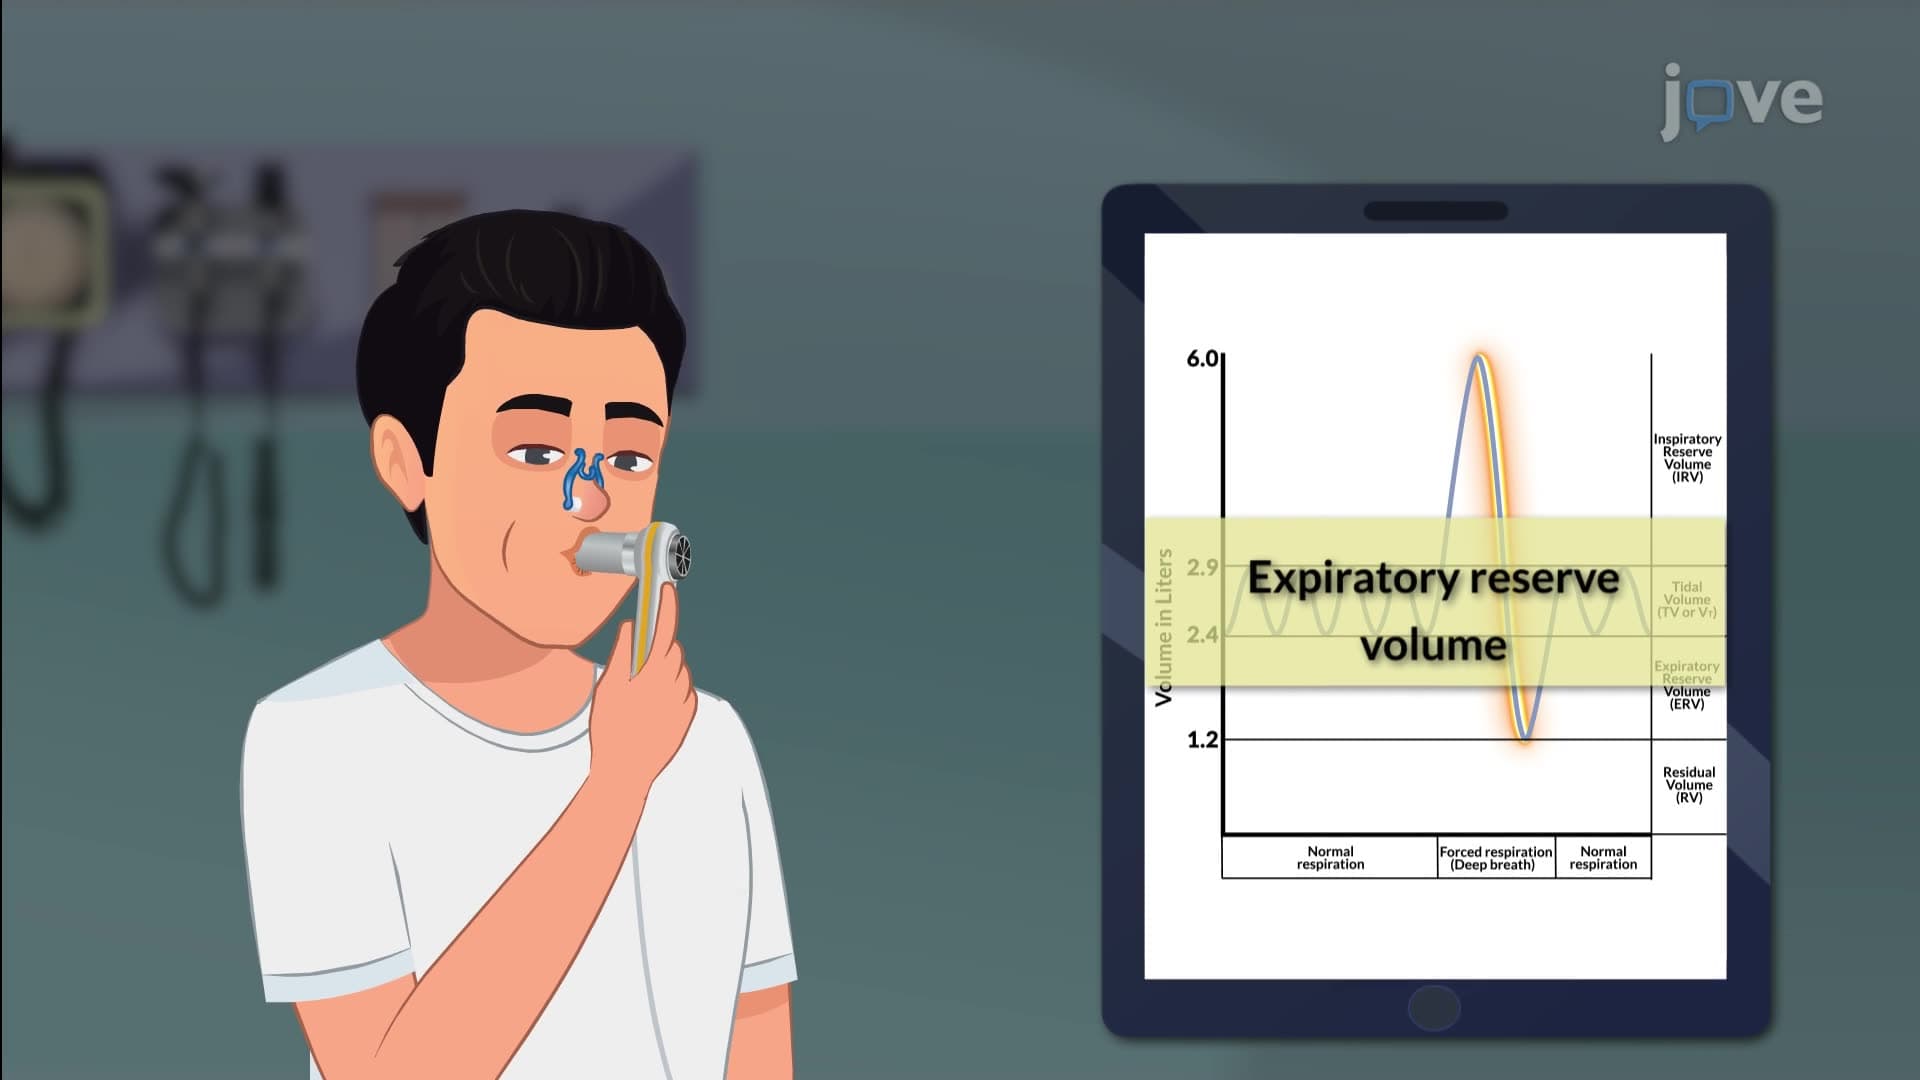
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:24
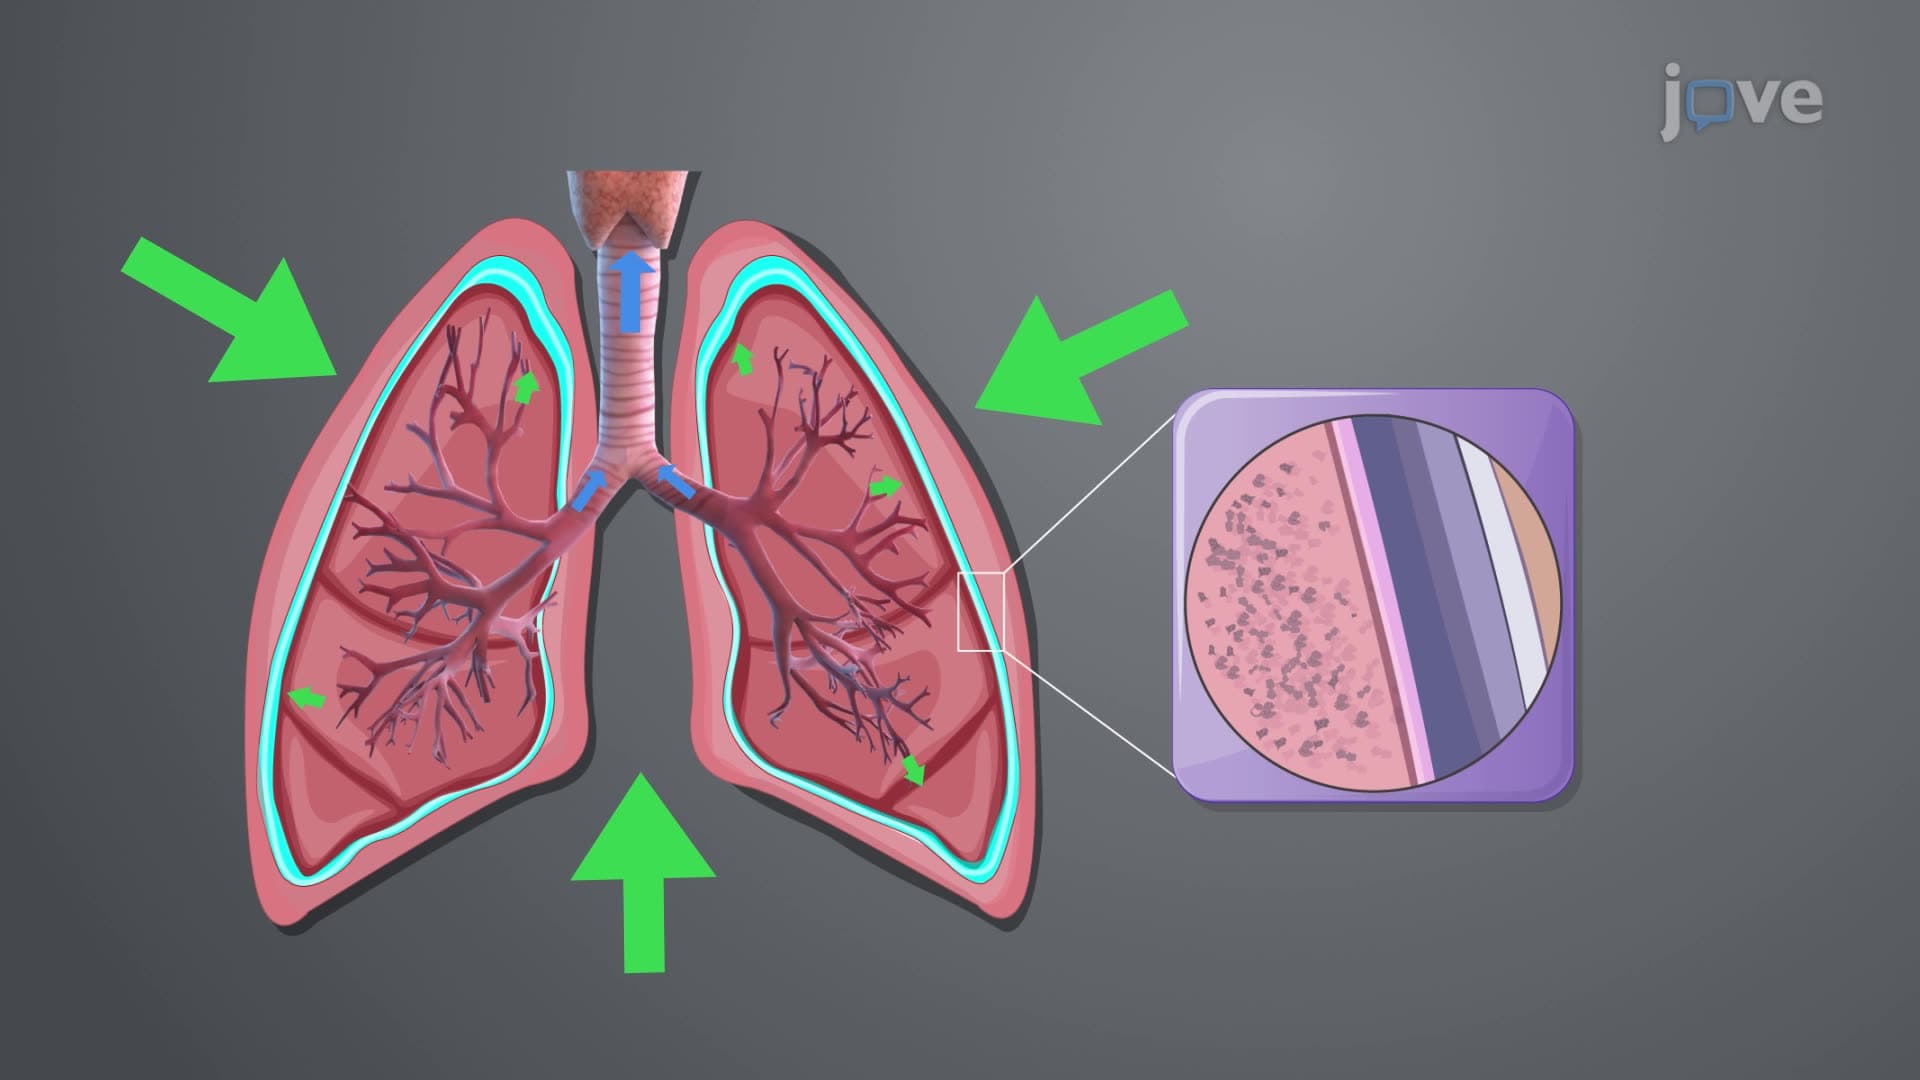
Pressure Relationships in Thoracic Cavity
Breathing Mechanisms
Both intra-alveolar and intrapleural pressures rely on specific lung properties. The ability to breathe—allowing air to enter the lungs during...
 01:27
Physical Assessment of the Respiratory Tract II: Inspection
Chest Configuration
The chest configuration can...
 01:24
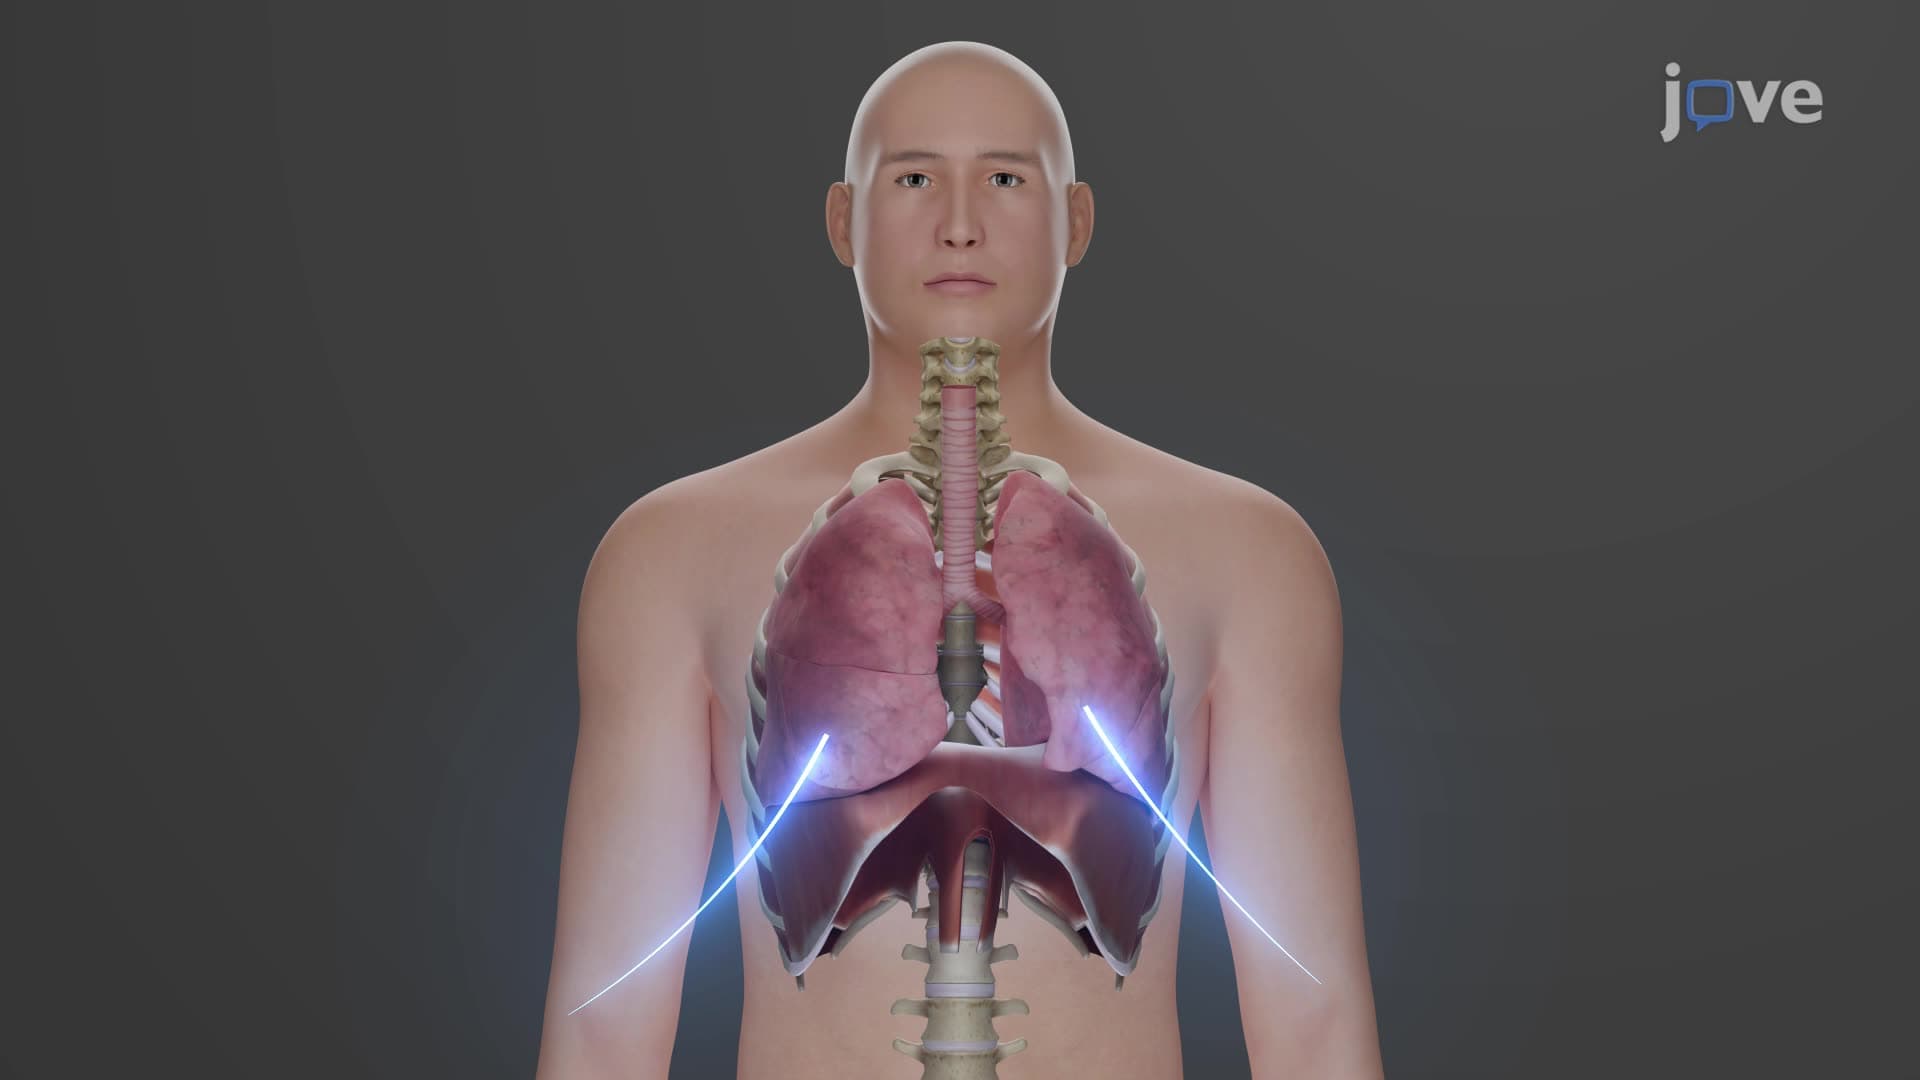
Pulmonary Ventilation: Inhalation
Boyle's law becomes particularly pertinent when examining respiratory...
 01:26
Respiratory Volumes and Capacities I
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...