Related Experiment Video
Updated: Oct 28, 2026
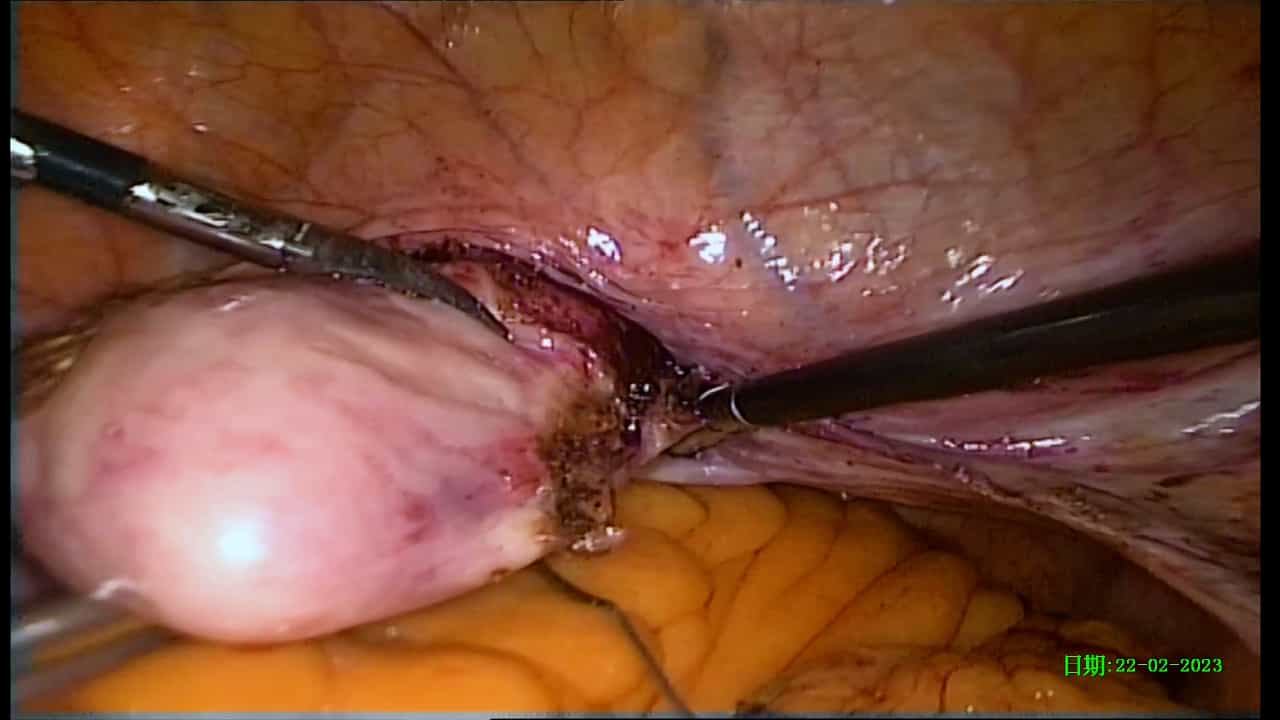
Laparoscopic Non-Mesh Cerclage Pectopexy with Uterine Preservation for Pelvic Organ Prolapse
Published on: October 25, 2024
Survey of Peritoneal Closure Practices During Minimally Invasive Sacrocolpopexy
Ashlee Weaver1,2, Erin Seifert Lavelle3,4,5, Jessica C Sassani3,4,5
1Women's Institute and Department of Obstetrics & Gynecology, Allegheny Health Network, Pittsburgh, PA, USA. amweaver0329@gmail.com.

Introduction And Hypothesis:
Minimally invasive sacrocolpopexy (MISC) is a commonly performed surgery for pelvic organ prolapse. Peritoneal closure ("reperitonealization") after mesh placement is at surgeon discretion and not standardized. Our primary objective was to assess practice patterns regarding reperitonealization during MISC among urogynecologists.
Methods:
A survey was designed to assess reperitonealization practices. The survey was assessed for face validity by a group of urogynecologists and then underwent an iterative process to improve content and readability. The survey was distributed by the American Urogynecologic Society.
Results:
There were 291 survey respondents with a 34% response rate. The majority held primary certification by The American Board of Obstetrics and Gynecology (96.9%) and completed fellowship in Urogynecology and Reconstructive Pelvic Surgery (82.1%). Most were moderate to high volume surgeons, with 37.1% performing 5-25 MISC yearly and 59.1% performing more than 25 yearly. Most participants reported "always" reperitonealizing in cases with and without concomitant hysterectomy (84.9% and 85.6% respectively). Only 2.8% reported never reperitonealizing during MISC with concomitant hysterectomy. Fewer respondents performed sacrohysteropexy but of those who did, 83.3% "always" reperitonealize mesh. Most providers reported using a running suture (88.9%) with a near-even mix between short-acting and delayed absorbable suture. Desire to avoid bowel complications was the most cited reason for mesh reperitonealization, endorsed by 91.3% of participants.
Conclusions:
Most urogynecologists participating in this survey report always reperitonealizing during MISC, although differences exist in suture type and technique. As future evidence is available on best surgical practices, this survey may generate hypotheses for future work on this subject.
