Related Experiment Video
Updated: Oct 28, 2026
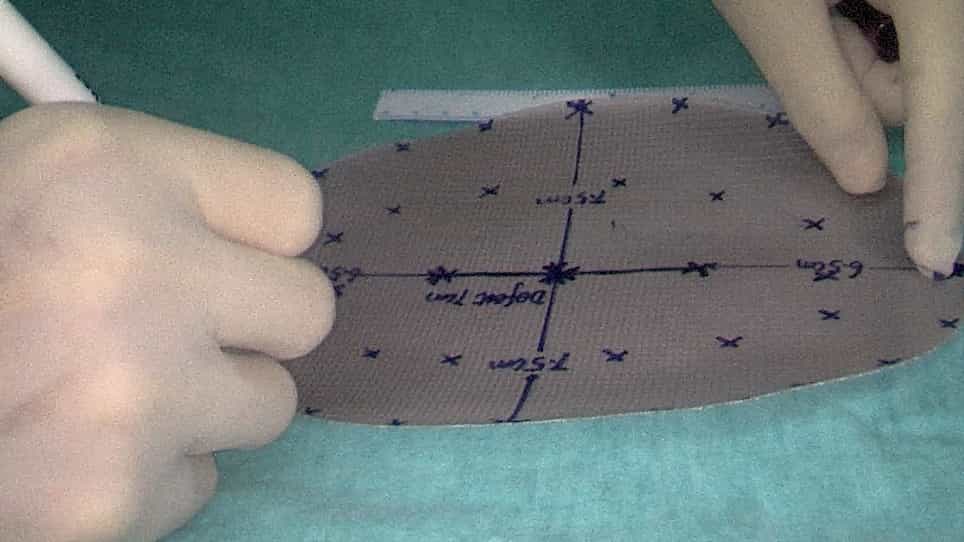
Application of a New Mesh Fixation Method in Laparoscopic Incisional Hernia Repair
Published on: December 23, 2022
Prosthetic mesh infection after abdominal wall hernia repair: a medico-legal analysis
Matteo Matteucci1, Sara Gioia2, Daniele Tesoro3
1General Surgery Residency Program, University of Milan, Milan, Italy. matteo.matteucci@unimi.it.

Background:
Mesh infection is a rare but potentially devastating complication of abdominal wall hernia repair, often requiring prolonged treatment, repeated surgery, and, in selected cases, mesh explantation. Although its clinical management has been extensively investigated, the medico-legal implications of mesh-related infections remain poorly explored. This study aimed to characterize the epidemiological, clinical, microbiological, therapeutic, and medico-legal features of Italian litigation concerning mesh infection following abdominal wall hernia repair.
Methods:
A retrospective review of publicly available Italian judicial decisions concerning mesh infection after hernia repair was performed. Clinical, microbiological, surgical, and legal variables were extracted, including patient and procedural characteristics, microbiological findings, treatment strategies, court-appointed technical expert (Consulente Tecnico d'Ufficio, [CTU]) assessments, judicial reasoning, and litigation outcomes.
Results:
Fourteen judicial decisions, corresponding to 13 distinct clinical episodes, were identified. Inguinal hernia repair was the most frequent procedure (38.5%), followed by incisional (30.8%), umbilical (23.1%), and femoral (7.7%) hernia repair. Staphylococcus aureus was the most isolated pathogen, while infection onset ranged from the early postoperative period to several years after implantation. Most patients ultimately required mesh explantation after failure of conservative treatment. A causal relationship between perioperative management and infection was established in 6 of 13 cases (46.2%) and excluded in the remainder. Across the judgments, CTU assessments consistently relied on temporal, topographical, and clinical criteria, together with evaluation of compliance with infection-prevention measures and perioperative documentation. Liability was more frequently associated with the inability to demonstrate adherence to accepted preventive standards than with the occurrence of infection itself. Alleged deficiencies in informed consent were common but did not independently result in compensation.
Conclusions:
Mesh infection should not be regarded as evidence of malpractice. Rather, judicial assessment depends on rigorous evaluation of causation, documentation of infection-prevention measures, and compliance with accepted standards of care. This study highlights the central role of multidisciplinary expert evaluation in medico-legal disputes involving mesh infection and underscores the need for greater integration between contemporary surgical evidence and medico-legal criteria when assessing healthcare-associated infections following hernia repair.
