Related Experiment Video
Updated: Oct 28, 2026
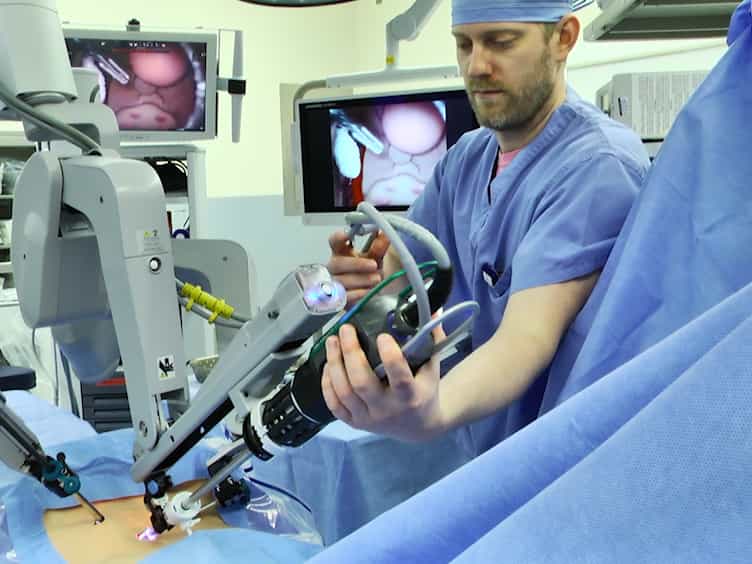
Emergency Undocking in Robotic Surgery: A Simulation Curriculum
Published on: May 20, 2018
Robotic Surgical Curricula Implementation Strategies for Trainees: A Systematic Review
Anna K Kieslich1, Ruari Jardine1, Hussain Ibrahim1
1NHS Highland, Raigmore hospital, Inverness, UK; University of Aberdeen, Aberdeen, UK.

Introduction:
Numerous curricula have been developed in response to the increasing use of robotic-assisted surgery (RAS). Less work has been done on strategies for implementation of RAS training into existing surgical training structures. We conducted a systematic review of implementation strategies across an international range of postgraduate training curricula.
Methods:
A systematic review of RAS curricula evidence and teaching was conducted on the platforms MEDLINE, PubMed, Embase, CINAHL, and PsycINFO in February 2024, updated in June 2025. Screening 10000 references using the population, intervention, comparator, outcomes framework for eligibility: surgical trainees, implemented curricula and educational interventions, reporting on curricula success or patient outcomes identified 33 studies reporting on 30 RAS educational interventions. Data were extracted and analyzed thematically, with NVivo 14 using Kern et al.'s curricula implementation framework: People, Time, Facilities, Funding, Administration, and Introduction. Quality was assessed using the Modified Medical Education Research Study Quality Instrument criteria (PROSPERO CRD42024566778).
Results:
Implementation strategies reported in the 33 publications were improved access, protected time, and mandatory training. The reporting on implementation methods was variable, unstructured, and anecdotal. The RAS educators, essential to curriculum success, may need specific training. For trainee progress, tracking simulator scores, operative steps, percentage of active time, and operative scores were important measures.
Conclusion:
The available evidence is of low quality. When implementing a RAS curriculum, the key areas for successful implementation are the RAS surgical educators, a relevant motivating simulation curriculum, RAS exposure, and performance tracking. Protected training time and good access to simulation facilities may also support trainees in preclinical training.