Related Experiment Video
Updated: Oct 28, 2026
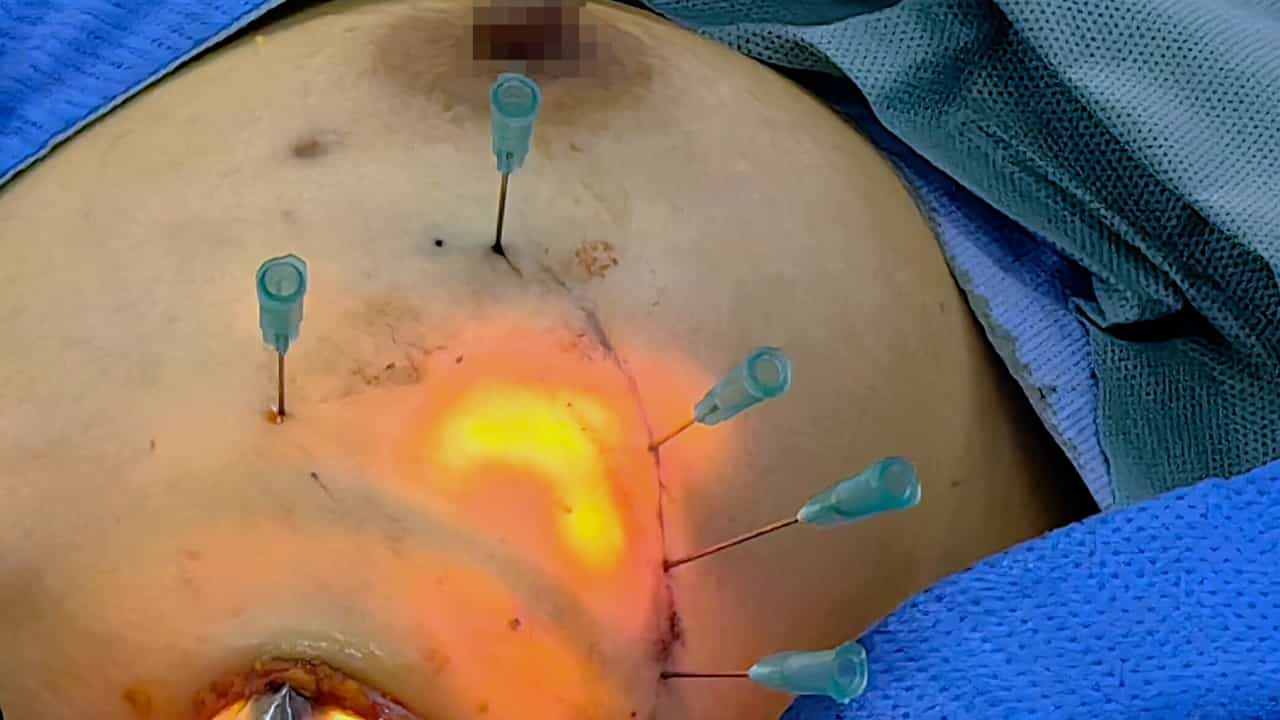
Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Izalontamab brengitecan for HR+/HER2- breast cancer in China (PANKU-Breast01): a randomised, phase 3 trial
Bo Lan1, Yehui Shi2, Xiying Shao3
1National Cancer Center/National Clinical Research Center for Cancer/Cancer Hospital, Chinese Academy of Medical Sciences and Peking Union Medical College, Beijing, China.

Background:
Patients with heavily pretreated hormone receptor-positive and human epidermal growth factor receptor 2-negative (HR+/HER2-) breast cancer have few treatment options. Izalontamab brengitecan (iza-bren) is a first-in-class, epidermal growth factor receptor and HER3 bispecific antibody-drug conjugate that contains a potent topoisomerase I inhibitor payload (Ed-04). The aim of PANKU-Breast01 was to compare the efficacy and safety of iza-bren versus chemotherapy in patients with pretreated HR+/HER2- breast cancer.
Methods:
In this randomised, phase 3, open-label, multicentre study in 72 hospitals in China, patients with HR+/HER2- breast cancer who had disease progression after endocrine therapy, cyclin-dependent kinase (CDK) 4/6 inhibitors, and one or two lines of chemotherapy were randomly assigned (1:1) to iza-bren (2·5 mg/kg, administered by intravenous infusion on day 1 and day 8 every 3 weeks) or physician's choice chemotherapy (eribulin, 1·4 mg/m2; vinorelbine, 25 mg/m2; or gemcitabine, 1000 mg/m2, all administered by intravenous infusion on day 1 and day 8 every 3 weeks; or capecitabine, 1000-1250 mg/m2, administered orally twice daily on days 1-14 of each 3-week cycle). Stratified block randomisation was performed by an independent vendor using an interactive web response system, with stratification factors of number of previous lines of chemotherapy, CNS metastasis, and HER2 expression status. Patients, investigators, and site personnel involved in patient care and performing trial procedures were not masked to treatment assignment. The primary endpoint was progression-free survival assessed by Blinded Independent Central Review per RECIST (version 1.1) in the modified intention-to-treat population, which consisted of all randomly assigned participants who had at least one dose of study drug. Median progression-free survival was estimated using the Kaplan-Meier method and hazard ratios (HRs) were calculated using a stratified Cox proportional hazards model. The trial was registered at ClinicalTrials.gov, NCT06343948, and is closed to recruitment.
Findings:
Between April 24, 2024, and June 6, 2025, 560 patients were screened, 177 were excluded, and 383 patients were randomly assigned and treated (190 were assigned to the iza-bren group and 193 were assigned to the chemotherapy group). All 383 participants in the study were female and of Chinese ethnicity. Median age was 54·0 years (IQR 47·0-60·0). At data cutoff (July 21, 2026), median follow-up for progression-free survival was 15·2 months (95% CI 13·9-16·8). Iza-bren significantly improved progression-free survival versus chemotherapy (log-rank p<0·0001), and median progression-free survival assessed by Blinded Independent Central Review was 8·2 months (95% CI 6·9-8·6) versus 4·0 months (2·9-4·3; HR 0·41 [95% CI 0·33-0·53]). Grade 3 or higher treatment-related adverse events occurred in 162 (85%) patients in the iza-bren group versus 127 (66%) patients in the chemotherapy group, and haematological adverse events were the most common in both groups. For the treatment of haematological adverse events, 138 (73%) patients in the iza-bren group received platelet-elevating agents, 28 (15%) patients in the iza-bren group received platelet transfusion, and 18 patients (10%) in the iza-bren group received a blood transfusion. Two patients in the iza-bren group died due to treatment-related adverse events.
Interpretation:
Iza-bren showed a significant improvement in progression-free survival versus chemotherapy in patients with HR+/HER2- breast cancer previously treated with endocrine therapy, CDK4/6 inhibitors, and one or two lines of chemotherapy (including taxanes). The overall survival data were immature, and an overall survival benefit has not been established. These results suggest that iza-bren could be a new treatment option for this population in China; however, further evaluation of iza-bren in global populations and in earlier lines of therapy for HER2-negative breast cancer is warranted.
Funding:
Baili-Bio (Chengdu) Pharmaceutical, CAMS Innovation Fund for Medical Sciences, Noncommunicable Chronic Diseases-National Science and Technology Major Project, National High Level Hospital Clinical Research Funding, and the National Natural Science Foundation of China.
