Related Experiment Video
Updated: Oct 28, 2026
Transtubular Endoscopic Posterolateral Decompression for L5-S1 Lumbar Lateral Disc Herniation
Published on: October 14, 2022
A Stepwise Navigation-Assisted Workflow for Lumbar Biportal Endoscopic Decompression Under Constrained Anatomical
Shinya Arataki1, Akiyoshi Miyamoto2, Tadashi Komatsubara2
1Department of Orthopaedic Surgery, Okayama Rosai Hospital, Okayama, Japan; Department of Orthopaedic Surgery, Japanese Red Cross Okayama Hospital, Okayama, Japan.

Background:
Preserving the ligamentum flavum (LF) provides a protective interface but does not create working space. In severe bony stenosis or degenerative spondylolisthesis, the space dorsal to the LF and dura may be insufficient during contralateral lateral-recess decompression, bringing instruments close to the dura.
Methods:
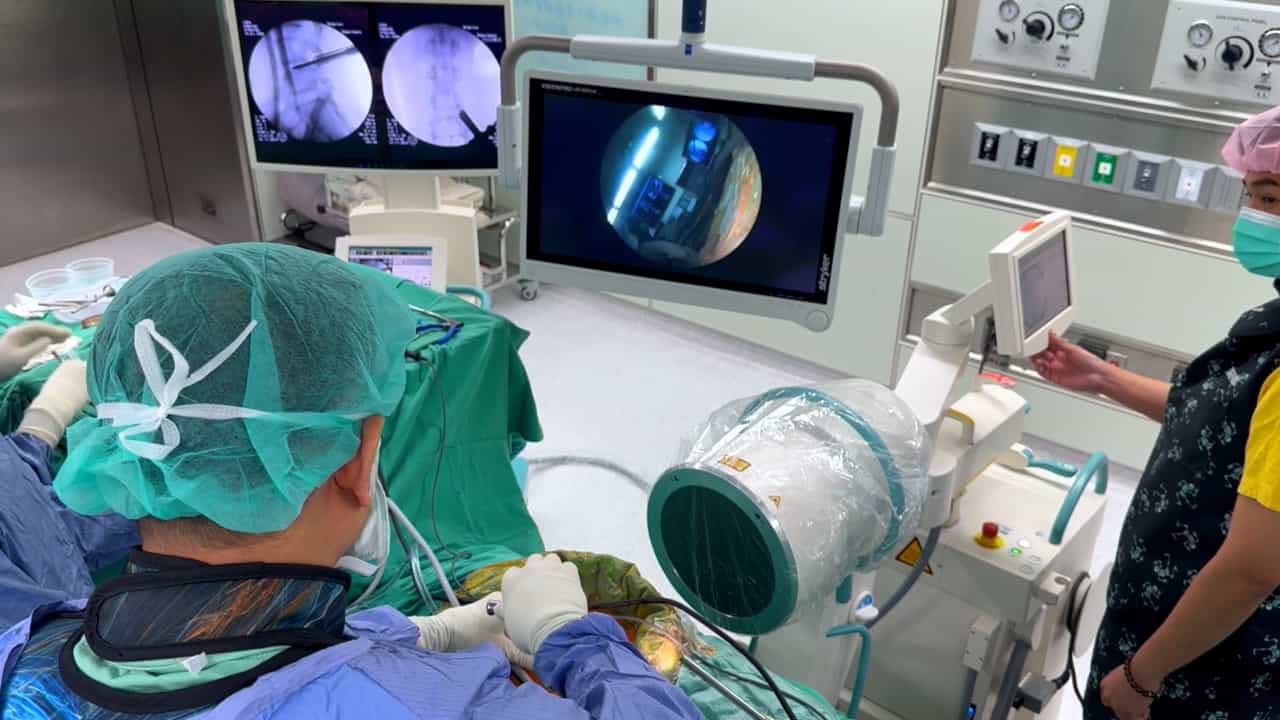
We describe this stepwise workflow for biportal endoscopic decompression under constrained lumbar anatomy. Contralateral cancellous-first drilling creates an intralaminar working recess while the ventral cortex and LF remain intact. The ventral cortex is progressively thinned with the LF preserved as a protective interface. If safely separable, the LF and residual thin cortex are removed; with severe LF-dural adhesion, only a very thin, mobile cortex-ligamentum flavum layer (cortex-LF layer) may remain after the intended bony decompression. Endoscopy guides tissue assessment and LF management; navigation provides adjunctive spatial information.
Results:
The workflow was applied to 13 consecutive cases by a single surgeon. Mean scores, retrospectively collected on a 0-100 mm visual analog scale, decreased from 75 ± 12 to 30 ± 12 for back pain and from 82 ± 9 to 25 ± 11 for leg pain at 3 months. Mean paired reductions were 45 mm (range, 15-70 mm) and 57 mm (range, 30-75 mm), respectively. No intraoperative dural tears or major complications occurred.
Conclusions:
This workflow organizes established protective-layer principles into a conditional sequence for limited dorsal working space. Navigation is adjunctive to endoscopic judgment. This series describes technical feasibility and early clinical experience but does not establish improved safety, reproducibility, or efficacy.