Related Experiment Video
Updated: Oct 28, 2026
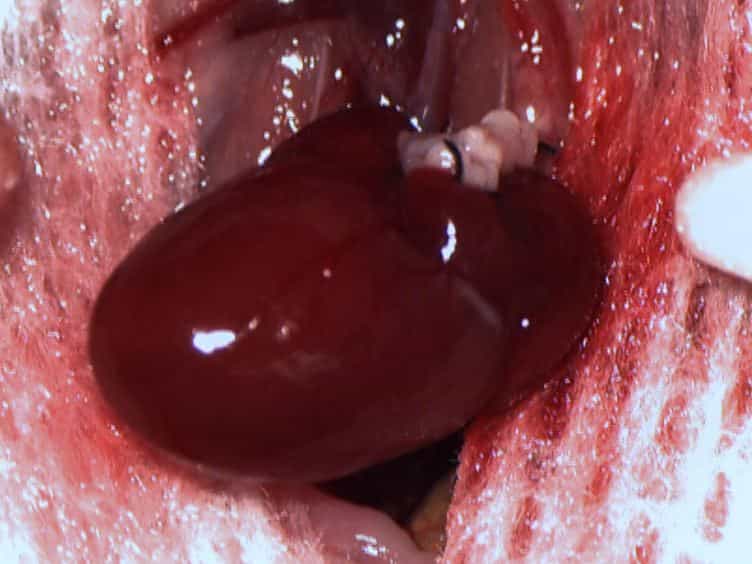
Transplantation of Pulmonary Valve Using a Mouse Model of Heterotopic Heart Transplantation
Published on: July 23, 2014
Mechanical Aortic Valve Replacement in Congenital Heart Disease Using the SJM Valve
Theresa Holst1, Tomislav Cvitkovic1, Murat Avsar1
1Hannover Medical School, Department of Cardiac, Thoracic, Transplantation and Vascular Surgery, Lower Saxony, Germany, Hanover.

Background:
Mechanical aortic valve replacement (mAVR) with the St. Jude Medical (SJM) prosthesis is an established treatment. However, data on prosthesis-related adverse events in patients with congenital heart disease (CHD) and aortic valve pathology are scarce.
Methods:
This single-center, retrospective, observational study included all CHD patients aged ≤ 45 years who underwent mAVR with an SJM prosthesis between 1993 and 2020. Survival and valve-related complications, including thromboembolism, bleeding, endocarditis, stenosis, regurgitation, and reoperation, were assessed. Kaplan-Meier analyses were performed to estimate time-dependent freedom from events.
Results:
A total of 54 patients (mean age at surgery: 21 ± 9 years; 80% male) with a mean follow-up of 8.9 ± 6.6 years were included. Survival was 95.5% at 5 years and 91.9% at 10 and 15 years postoperatively. Relevant, interestingly often only transient, valvular dysfunction defined as peak gradient ≥ 50 mm Hg and/or ≥ moderate regurgitation occurred in 22% of patients. Freedom from prosthesis explantation was 97.4% at 5 and 10 years and 93.1% at 15 years. Freedom from anticoagulation-related events at 5, 10, and 15 years was 95.3%, 88.9%, and 84.9%, respectively. Freedom from prosthetic valve endocarditis was 97.4% at 5 years, 94.7% at 10 years, and 90.4% at 15 years.
Conclusion:
SJM mechanical aortic valve replacement in pediatric and young adult patients with CHD demonstrated favorable midterm survival, low reoperation rates, and acceptable prosthesis-related morbidity. Prosthetic valve dysfunction was frequently transient and rarely required reoperation, supporting SJM valves as a durable option with appropriate prosthesis sizing, anticoagulation, and long-term follow-up.


Related Concept Videos
 01:22
Mitral Stenosis I: Introduction
 01:27
Mitral Valve Prolapse I: Introduction
 01:26
Mitral Stenosis III: Medical Management
 01:16
Heart Valves
The AV valves prevent the backflow of blood from the ventricles to the atria during ventricular contraction. These valves function with the assistance of the chordae tendineae and papillary muscles. When the ventricles are relaxed, the chordae tendineae are slack, allowing blood to flow from the atria into the...
 01:20
Mitral Regurgitation I: Introduction
 01:22
Mitral Valve Prolapse II: Assessment and Management