Related Experiment Video
Updated: Oct 28, 2026
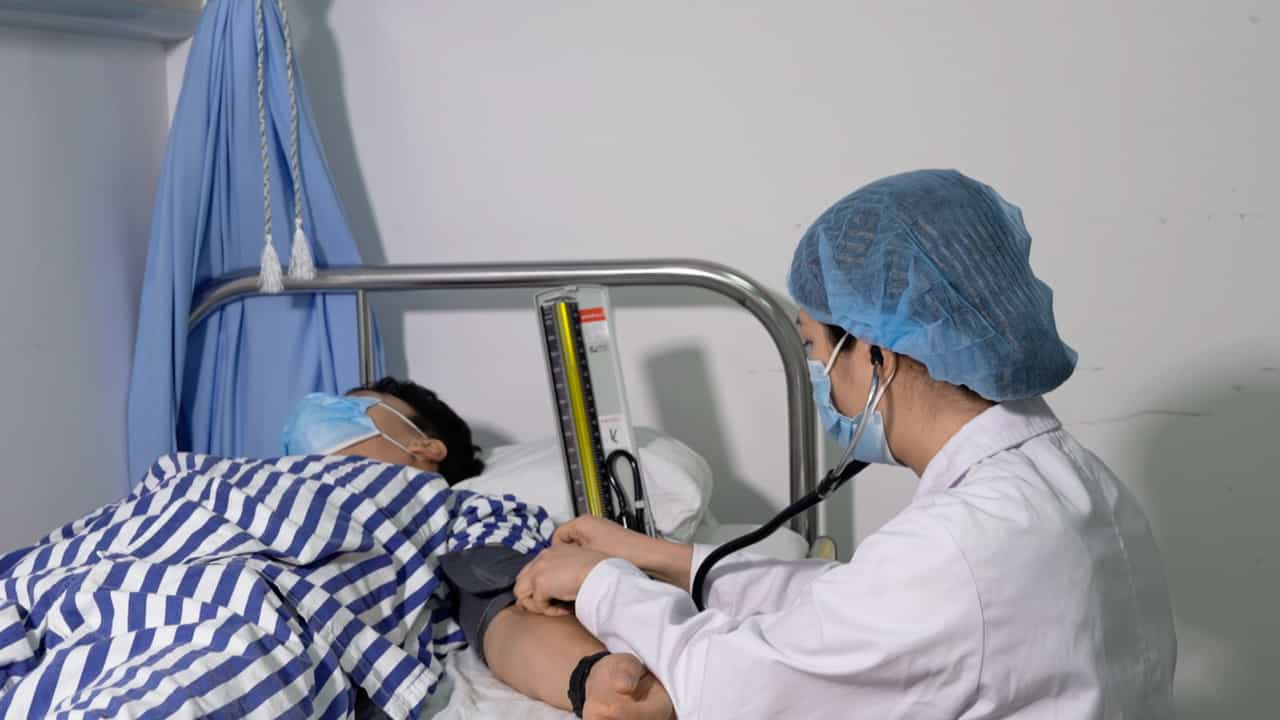
A Preliminary Study on Warm Acupuncture and Moxibustion for Treating Chronic Obstructive Pulmonary Disease with Abdominal Distension
Published on: September 1, 2023
[Chinese guidelines for the diagnosis and management of chronic obstructive pulmonary disease (2026 revision)]

Abstract:
The Chinese guidelines for the diagnosis and management of chronic obstructive pulmonary disease (2026 revision) were developed by the Chronic Obstructive Pulmonary Disease Groups of the Chinese Thoracic Society and the Chinese Association of Chest Physicians. Building on the 2021 edition, this revision incorporates evidence published over the past five years and experience from COPD prevention and management in China, and provides comprehensive updates on disease definition, etiology and pathogenesis, case finding, diagnosis and comprehensive assessment, stable COPD management, diagnosis and treatment of acute exacerbations, comorbidity management, and future research directions. The guideline primarily applies the Grading of Recommendations Assessment, Development and Evaluation (GRADE) approach, supplemented by the Oxford Centre for Evidence-Based Medicine Levels of Evidence, to assess the certainty of evidence and develop recommendations. It offers practical recommendations for the diagnosis and management of COPD across 22 clinical questions. It aims to promote early identification, standardized diagnosis and treatment, and comprehensive management of COPD, and therefore to improve the standardized care and reduce the disease burden of COPD in China.The 22 key clinical questions and corresponding recommendations are summarized as follows.Question 1: Given the current underdiagnosis of COPD, which strategies can improve early diagnosis?Recommendation 1: We recommend active and opportunistic case finding to identify individuals at high risk of COPD and facilitate early diagnosis. (1B/strong recommendation)Question 2: Which parameters should be assessed when selecting initial pharmacotherapy for patients with COPD?Recommendation 2: Patients with COPD should undergo individualized assessment based on symptom burden and exacerbation risk and be classified into groups A, B, or E. Additional assessments should include the severity of airflow obstruction on pulmonary function testing, comorbidities, and biomarkers such as the peripheral blood eosinophil count. (2B/strong recommendation)Question 3: How should the mMRC and CAT scores be used for symptom assessment in the ABE classification?Recommendation 3: Symptoms of COPD should be assessed using the modified Medical Research Council (mMRC) dyspnea scale and/or the COPD Assessment Test (CAT). Results from the two instruments may be discordant: the mMRC scale focuses on dyspnea, whereas the CAT is more suitable for a comprehensive assessment of multiple symptoms. (2B/strong recommendation)Question 4: Should chest CT be included in the initial assessment of COPD?Recommendation 4: Chest imaging should be included in the initial assessment of COPD, with chest computed tomography (CT) preferred. (2B/conditional recommendation)Question 5: What are the key preventive measures targeting exposure to risk factors?Recommendation 5: Smoking cessation interventions should be actively provided to all patients with COPD. Clean fuels, effective ventilation, nonpolluting stoves, and similar measures are recommended to reduce harmful environmental exposures; occupational protection should also be strengthened to avoid continued exposure to potential irritants. (1A/strong recommendation)Question 6: How should vaccination be recommended for patients with COPD?Recommendation 6: Annual influenza vaccination is recommended. Regular pneumococcal vaccination with PPSV23 is also recommended, with PCV20 or PCV21 as options for susceptible individuals; the specific pneumococcal vaccination schedule should follow product-specific prescribing information. (1A/strong recommendation). Vaccination against respiratory syncytial virus (RSV), tetanus, diphtheria, and acellular pertussis (Tdap), and herpes zoster is suggested. (1A/conditional recommendation)Question 7: How should initial pharmacotherapy be selected according to the ABE classification and the peripheral blood eosinophil count?Recommendation 7: Initial pharmacotherapy should be selected according to symptoms, exacerbation risk, and the peripheral blood eosinophil count. For patients in group E, regimens that reduce the risk of future exacerbations should be prioritized. When the peripheral blood eosinophil count is ≥300 cells/μl, triple inhaled therapy[inhaled corticosteroids(ICS) plus long-acting β2 agonists (LABA) plus long-acting muscarinic antagonists(LAMA)] is recommended to achieve a state of low disease activity characterized by freedom from exacerbations. (1B/strong recommendation)Question 8: What are the indications for adding an ICS to long-acting bronchodilator therapy?Recommendation 8: The addition of an ICS to long-acting bronchodilator therapy is recommended for patients with COPD who have any of the following features: (1)≥1 moderate or severe COPD exacerbation per year; (2) a blood eosinophil count ≥300 cells/μl, or ≥100 cells/μl during follow-up assessment; or (3) a history of asthma or concomitant asthma-like features. (1B/strong recommendation)Question 9: How should a standardized pathway for follow-up assessment and pharmacological treatment adjustment be established for patients with stable COPD?Recommendation 9: During follow-up pharmacotherapy, treatment adjustment should be guided by two core treatable traits: persistent dyspnea and the occurrence of exacerbations. For patients with persistently poor symptom control, bronchodilator therapy should be optimized stepwise after inhaler technique, adherence, and the effects of comorbidities have been assessed. For patients who continue to experience exacerbations, the addition, continuation, or cautious withdrawal of ICS should be guided by the current regimen and peripheral blood eosinophil count. Biologic therapy is appropriate for selected high-risk populations. (1B/strong recommendation)Question 10: How should treatment be optimized and adjusted for patients already receiving ICS+LABA therapy?Recommendation 10: Patients receiving ICS+LABA may continue the regimen if their condition is stable. If exacerbations persist, escalation to triple therapy with ICS+LABA+LAMA is recommended. For patients with COPD who are at high risk of pulmonary infection, including mycobacterial infection, withdrawal of ICS and a switch to dual bronchodilator therapy should be considered to reduce the risk of further infections. (1B/strong recommendation)Question 11: What are the indications for biologic therapy in patients with COPD?Recommendation 11: For patients who continue to experience recurrent exacerbations despite ICS+LABA+LAMA therapy, inhaled medication use, comorbidities and other contributing factors should be assessed, and biologic therapy should be selected on an individualized basis according to features such as the peripheral blood eosinophil count and the presence of chronic bronchitis. (1B/conditional recommendation)Question 12: How should an inhaler device be selected according to individual patient characteristics?Recommendation 12: The most appropriate inhaler device and medication should be selected according to whether the patient has adequate inspiratory flow, hand-mouth coordination, and the ability to inhale independently, as well as the characteristics of the device and medication. Training in inhaler technique and individualized assessment should be reinforced. (4/strong recommendation)Question 13: How should pulmonary rehabilitation be implemented for patients with COPD?Recommendation 13: Dynamic pulmonary rehabilitation assessment is recommended before treatment and at different stages during treatment, including clinical, functional, nutritional, and psychological assessments. Pulmonary rehabilitation should be initiated as early as possible in patients with stable COPD who have no absolute contraindications. For patients with acute exacerbations of COPD, pulmonary rehabilitation should be provided early during hospitalization and after discharge. An individualized rehabilitation prescription should be developed according to assessment findings and may include airway clearance techniques, breathing training, aerobic and resistance exercise, positioning, and respiratory support. (1A/strong recommendation)Question 14: What are the indications and treatment regimen for oxygen therapy in stable COPD?Recommendation 14: Long-term oxygen therapy is recommended for patients with COPD and severe resting hypoxemia, defined as either (1) PaO2≤55 mmHg(1 mmHg=0.133 kPa) or SpO2≤88% at rest, or (2) PaO2 of 55-60 mmHg or SpO2 of 88%-89% at rest together with pulmonary hypertension, peripheral edema suggestive of congestive heart failure, or polycythemia (hematocrit>55%). Oxygen should be administered for at least 15 h/day to maintain PaO2 ≥60 mmHg and/or SpO2 ≥90%. (1B/strong recommendation)Question 15: What are the indications for noninvasive ventilation in stable COPD?Recommendation 15: Long-term noninvasive ventilation (NIV) is suggested for patients with severe chronic hypercapnia and a history of hospitalization for acute respiratory failure, or for those with persistent daytime hypercapnia (PaCO2>53 mmHg). (1B/strong recommendation)Question 16: Which pharmacological and nonpharmacological interventions can reduce mortality in patients with COPD?Recommendation 16: Smoking cessation, pharmacotherapy (fixed-dose triple therapy), and nonpharmacological interventions, including pulmonary rehabilitation, long-term oxygen therapy, noninvasive ventilation, and surgical lung volume reduction, are recommended to reduce mortality in patients with COPD. (1B/strong recommendation)Question 17: How should bronchoscopic interventional therapies be selected for patients with COPD?Recommendation 17: Bronchoscopic interventions, including endobronchial valves and thermal vapor ablation, are recommended for selected patients with advanced emphysema and COPD. (1B/conditional recommendation)Question 18: What are the indications for lung transplantation in patients with COPD?Recommendation 18: For patients with very severe COPD (progressive disease with a BODE index of 7-10 who are not candidates for lung volume reduction surgery), referral for lung transplantation may be considered if at least one of the following is present: (1) a history of hospitalization for an acute hypercapnic exacerbation (PaCO2>50 mmHg); (2) pulmonary hypertension and/or cor pulmonale despite oxygen therapy; or (3) FEV₁<20% predicted together with DLCO<20% predicted or homogeneous emphysema. (3B/conditional recommendation)Question 19: How should systemic corticosteroids be used for acute exacerbations of COPD?Recommendation 19: For moderate or severe acute exacerbations of COPD, low-dose, short-course systemic corticosteroid therapy is suggested; routine prolongation of treatment or use of high-dose systemic corticosteroids is not recommended. Nebulized budesonide may be considered as an alternative for patients with contraindications to systemic corticosteroids or a high risk of adverse reactions. (Very low-quality evidence/weak recommendation)Question 20: How should high-flow nasal cannula oxygen therapy be used in the treatment of acute exacerbations of COPD?Recommendation 20: High-flow nasal cannula (HFNC) oxygen therapy is suggested for patients with an acute exacerbation of COPD who have persistent hypoxemia, cannot tolerate NIV or have contraindications to NIV, require sequential oxygen therapy after NIV, or require prevention of reintubation after extubation. In patients with acute hypercapnic respiratory failure who meet the indications for NIV, HFNC should not replace NIV as the preferred initial treatment. (1B/conditional recommendation)Question 21: What are the indications for noninvasive ventilation in the treatment of acute exacerbations of COPD?Recommendation 21: NIV is recommended for patients with an acute exacerbation of COPD who have any of the following: (1) respiratory acidosis (PaCO2 ≥6.0 kPa or 45 mmHg and arterial pH≤7.35); (2) severe dyspnea with clinical signs of respiratory muscle fatigue and/or increased work of breathing, such as use of accessory respiratory muscles, paradoxical thoracoabdominal motion, or intercostal retraction; (3) persistent hypoxemia despite oxygen therapy; or (4) a need for sequential invasive-noninvasive mechanical ventilation. (1A/strong recommendation)Question 22: What measures are recommended to prevent acute exacerbations of COPD?Recommendation 22: After an acute exacerbation, the management plans for COPD and its comorbidities should be evaluated, and appropriate measures should be implemented to prevent further exacerbations, particularly peri-discharge management, long-term standardized pharmacotherapy, smoking cessation, vaccination, and nonpharmacological interventions such as pulmonary rehabilitation. (4/strong recommendation).
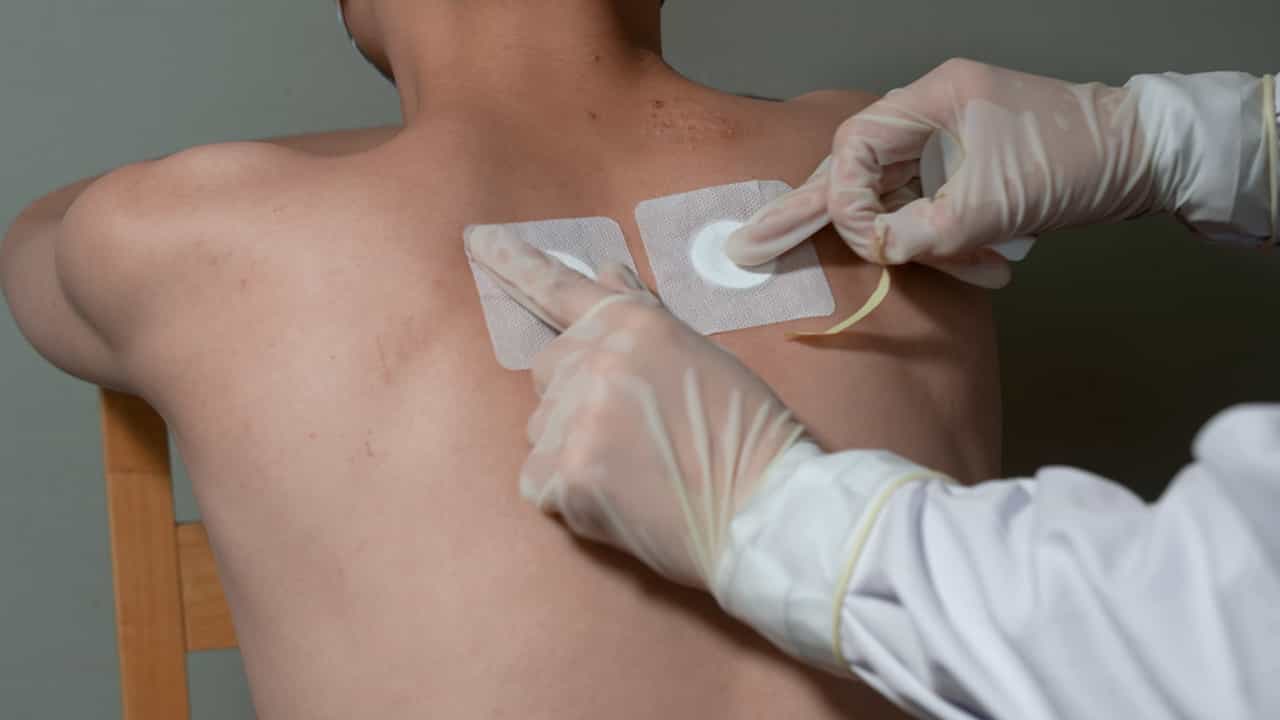
Related Concept Videos
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:30
Chronic Obstructive Pulmonary Disease-V: Nursing Management
Assessment
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations