Related Experiment Videos
Concurrent acute pancreatitis and splanchnic vein thrombosis in a heavy smoker: a dynamic D-dimer-based diagnostic
Ligang Liu1,2, Fenqiang Li3, Tingting Liu4
1Department of General Surgery, The First People's Hospital of Lanzhou City, Lanzhou, Gansu, China. liulg666@126.com.

Background:
Splanchnic vein thrombosis (SVT) concurrent with acute pancreatitis (AP) at initial diagnosis is rare and its pathophysiology remains unclear. We describe a heavy smoker who presented with AP with occult non-occlusive SVT, which paradoxically progressed to complete thrombotic occlusion.
Case Presentation:
A 52-year-old male heavy smoker (40-60 cigarettes/day for 30 years) presented with epigastric pain and was diagnosed with AP after excluding common etiologies. On admission, D-dimer was markedly elevated at 9.15 mg/L (18 times the upper limit of normal). By day 12, despite radiological resolution of pancreatic inflammation and a significant c-reactive protein (CRP) reduction (139.16 to 45.35 mg/L), he developed mesenteric ischemia. Laboratory findings revealed a paradoxical "dynamic decoupling": D-dimer further escalated to 9.52 mg/L, fibrinogen (FIB) was consumed to 2.72 g/L, and antithrombin III (AT-III) was critically depleted to 45%. Contrast-enhanced CT confirmed complete thrombotic occlusion of the superior mesenteric, splenic, and portal veins; retrospective review verified non-occlusive SVT at onset. Standard systemic anticoagulation failed to halt thrombotic progression, reaching a "pharmacological ceiling" due to profound AT-III depletion. Transjugular endovascular intervention (thrombus aspiration and catheter-directed thrombolysis) successfully reversed the intestinal ischemia.
Conclusions:
In heavy smokers with AP, an initial D-dimer exceeding 18 times the upper limit of normal should prompt early contrast-enhanced CT to exclude occult SVT. When standard systemic anticoagulation fails due to a "pharmacological ceiling" of depleted antithrombin, timely endovascular escalation is a key salvage strategy.
Related Concept Videos
 01:21
Chronic Pancreatitis II: Pathophysiology
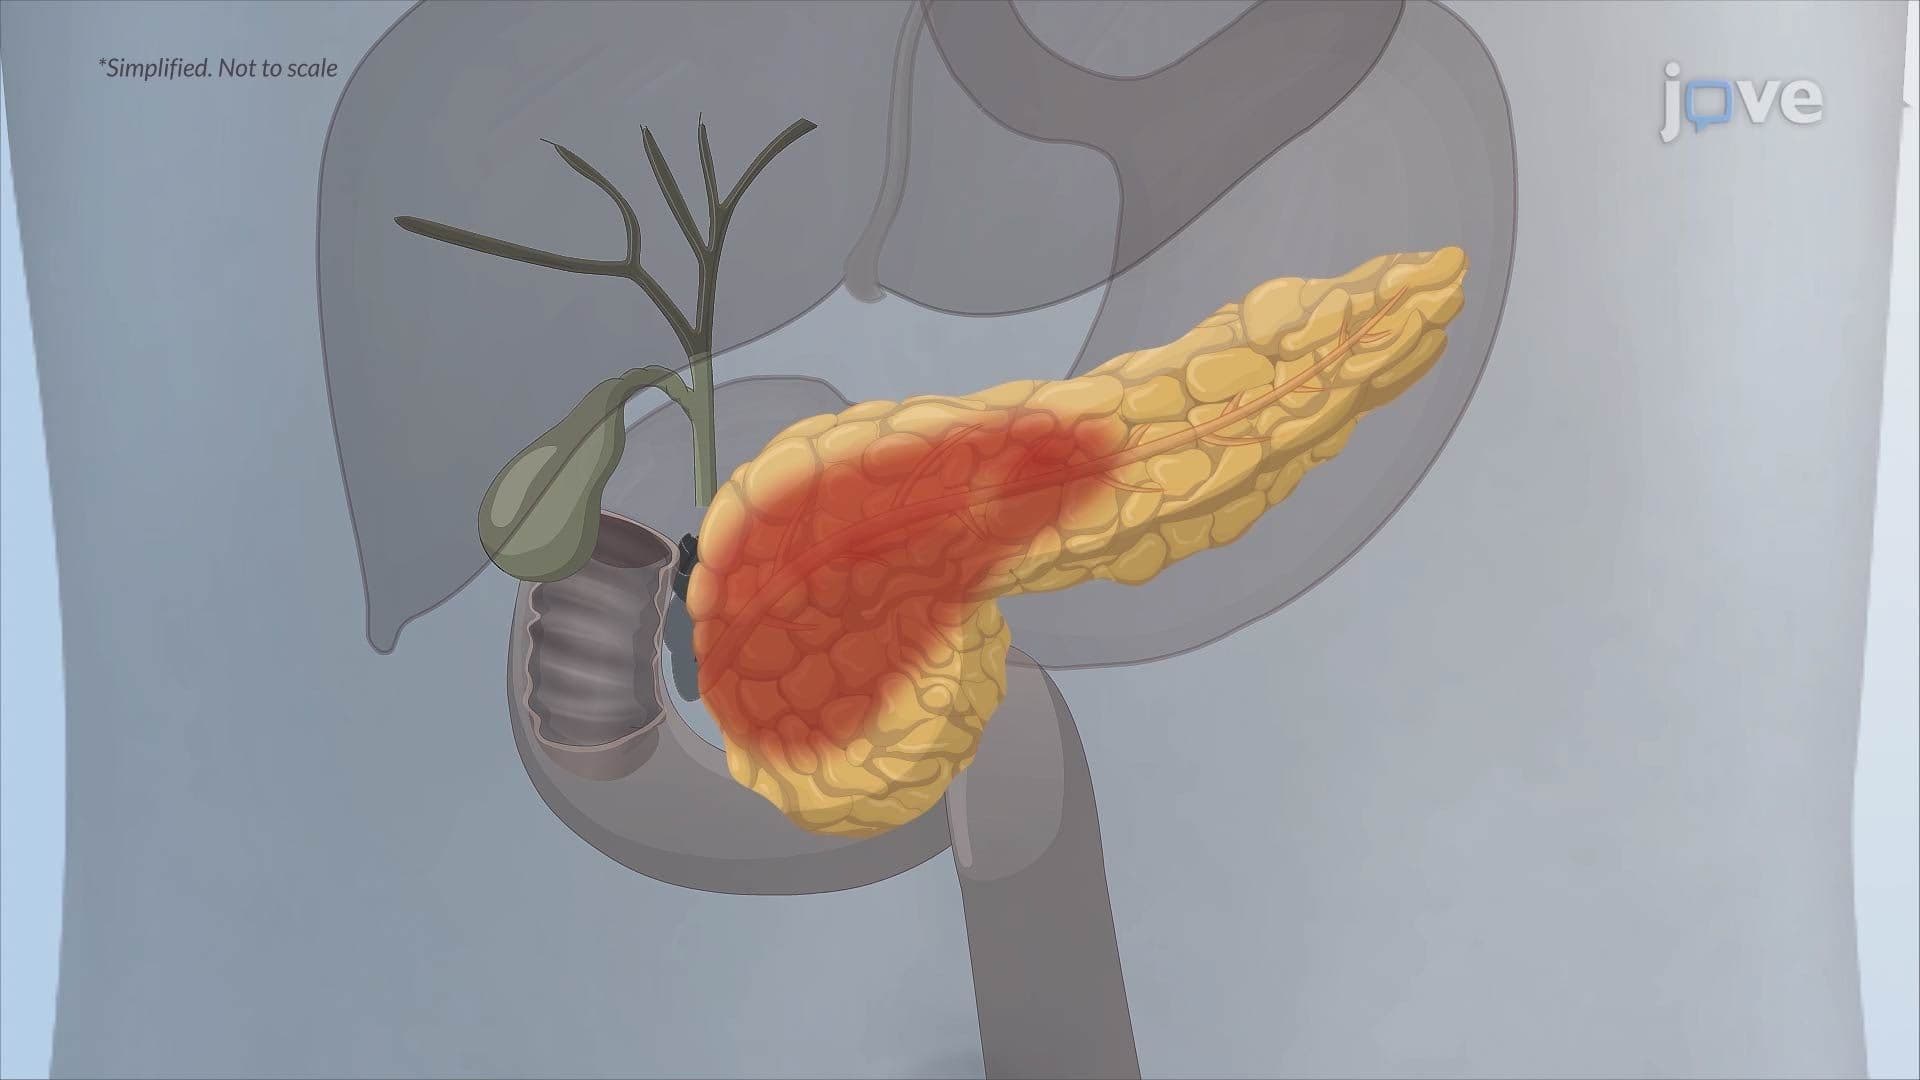 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include: