Related Experiment Video
Updated: Oct 28, 2026
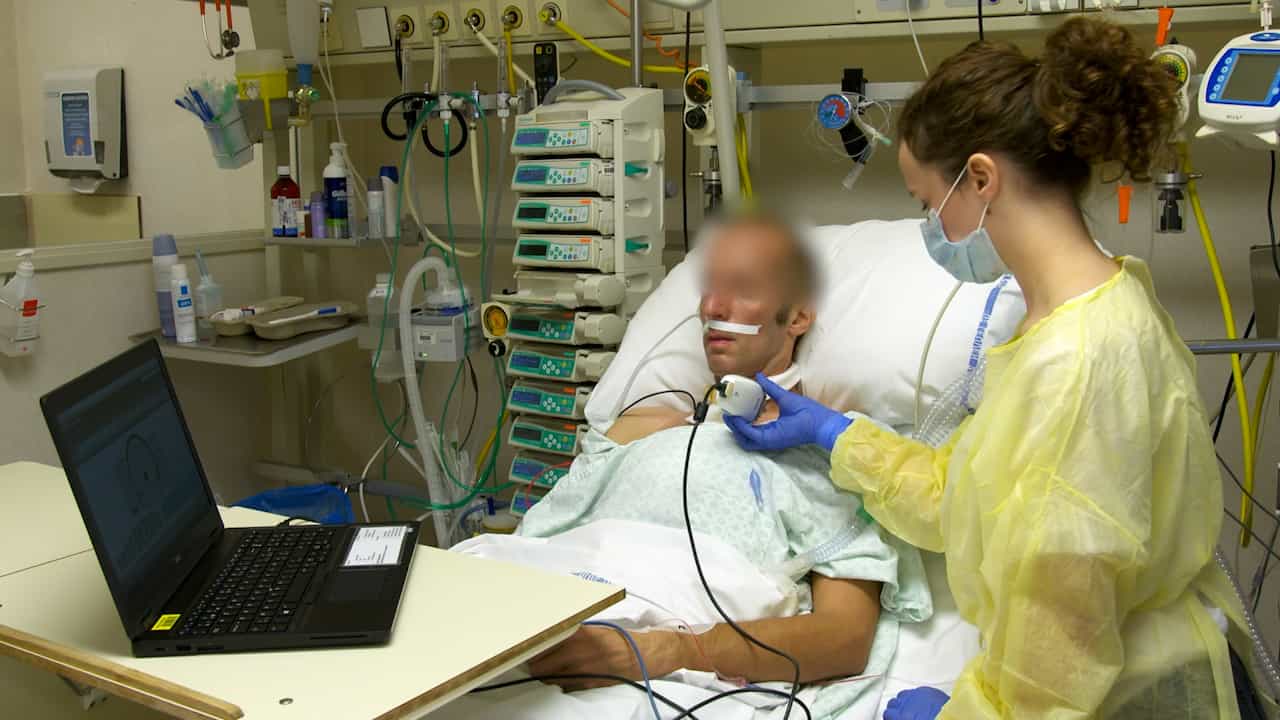
Inspiratory Muscle Training as an Adjunct to the Treatment of Weaning Failure in Critically Ill Patients: A Practical Guide
Published on: January 30, 2026
Preoperative inspiratory muscle training for patients undergoing cytoreductive surgery and hyperthermic
Olivia Sand1, Erebouni Arakelian2,3, Egidijus Semenas2
1Department of Surgical Sciences, Gastrointestinal Surgery, Uppsala University, Uppsala, Sweden. olivia.sand@uu.se.

Background:
Patients undergoing surgery due to peritoneal metastases (PM) are at high risk of postoperative pulmonary complications (PPCs). While several studies have provided promising results regarding the positive effects of preoperative inspiratory muscle training (IMT) regarding length of hospital stay and PPCs after other types of major abdominal surgery, its feasibility in the preoperative management of patients with PM is still unclear. The aim of the study was to evaluate the feasibility of preoperative IMT for patients scheduled for cytoreductive surgery (CRS) and hyperthermic intraperitoneal chemotherapy (HIPEC).
Methods:
A single-blinded randomized controlled feasibility study was conducted in Uppsala, Sweden, between 2016 and 2020. Inclusion criteria were age ≥ 18 years, surgery scheduled ≥ 2 weeks after inclusion, and proficiency in Swedish. Patients were randomized 1:1 to either IMT or positive expiratory pressure (PEP). Feasibility was evaluated using two domains: process feasibility (recruitment, intervention adherence, and patient acceptability) and scientific feasibility (ability to perform pre- and postoperative respiratory muscle and lung function assessments, reproducibility of assessments, and adverse events). Preliminary treatment effects and incidence of postoperative pulmonary complications (PPCs) were also evaluated.
Results:
Thirty participants were enrolled, with a recruitment rate of 11%. The median training period was 24.5 days, with adherence of 77% in the intervention group and 98% in the control group. Acceptability was high, with 87% rating the training program ≥ 5 on a scale of 1-10. Two participants withdrew due to discomfort at the postoperative assessments, and the reproducibility of assessments was 57-100%. One IMT participant withdrew due to a dry cough. The intervention group showed a larger increase in maximal inspiratory pressure (MIP) from baseline to follow-up and faster recovery of vital capacity (VC) than controls. PPCs were more frequent in the control group.
Conclusions:
Preoperative IMT was acceptable to patients and safe, but recruitment and attrition were identified as obstacles to address in a future full-scale RCT.
Trial Registration:
NCT05665257 . Registered 23 December 2022-retrospectively registered.