Related Experiment Video
Updated: Oct 28, 2026
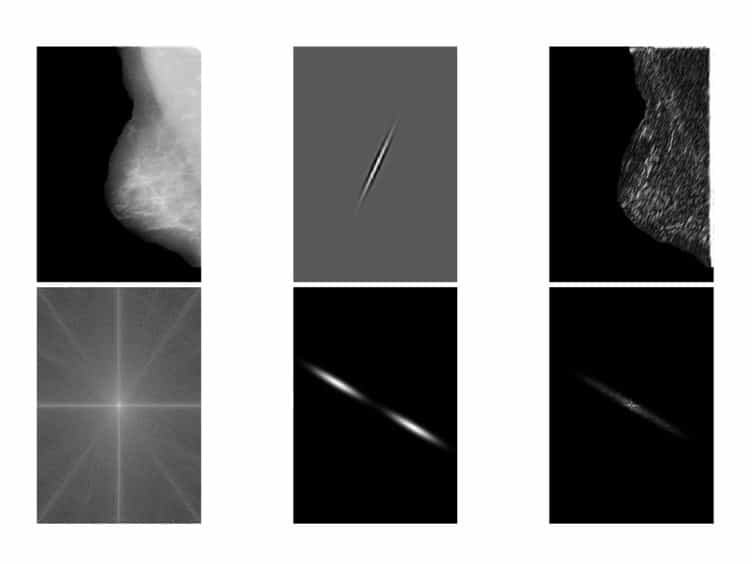
Detection of Architectural Distortion in Prior Mammograms via Analysis of Oriented Patterns
Published on: August 30, 2013
MammoDiff: weakly supervised mammographic anomaly detection via classifier-guided denoising diffusion models-a
Ahmad Nasayreh1,2, Nagham Osman3,4, Laila Tahoun5
1Department of Computer Engineering, Automation and Robotics, School of Computer and Telecommunication Engineering, University of Granada, Granada, Spain.

Introduction:
Early detection of malignant mammographic lesions is a critical clinical challenge, particularly where large annotated datasets are unavailable. Supervised deep learning achieves near-radiologist performance but requires large datasets with reliable labels and pixel/ROI annotations. Weakly supervised anomaly detection, requiring only image-level binary labels, offers an annotation-efficient alternative, yet prior GAN- and autoencoder-based methods have struggled to preserve fine anatomical detail in the mammographic domain.
Methods:
We present MammoDiff, to our knowledge the first application of classifier-guided denoising diffusion models to weakly supervised mammographic anomaly detection, trained and evaluated on 3,013 mammograms from 806 patients at King Hussein Cancer Center (KHCC), Jordan. MammoDiff encodes input anatomy through deterministic DDIM noise encoding and reconstructs a counterfactual healthy image guided by the gradient signal of a noise-conditioned binary classifier. The anomaly map is the pixel-wise absolute difference between input and reconstruction, and the image-level score is obtained by spatial mean pooling. A 3 × 3 ablation over noise level L ∈ {250, 500, 750} and gradient scale s ∈ {50, 100, 200} was performed on the validation set.
Results:
The optimal configuration (L = 750, s = 50) achieved AUROC = 0.7246 [95% CI: 0.6685, 0.7825] on the held-out test set (n = 304), compared with a simplified PatchCore-style baseline (AUROC = 0.6634) and a supervised ResNet-50 reference (AUROC = 0.8100), without pixel-level annotation. The proposed Healthy-Shift Index (HSI) was positive for 94.8% of malignant and 87.4% of normal cases, so it is the separation between the class distributions rather than the sign of the index that carries information.
Discussion:
This performance is not clinically deployable: at the Youden-optimal threshold the sensitivity is 0.6013, meaning that 61 of 153 malignant cases are missed, well below the approximately 87% targeted by FDA-cleared triage devices, and the study is single-centre without external validation. MammoDiff is therefore presented as a methodological proof-of-concept and a reproducible baseline for future work, not as a screening or triage tool..
