Related Experiment Video
Updated: Oct 28, 2026
Magnetic Resonance Derived Myocardial Strain Assessment Using Feature Tracking
Published on: February 12, 2011
Evaluating the impact of passive driver position on image consistency and repeatability in 3.0T cardiac magnetic
Jun Wang1,2,3, Shutian An1,2,3, Zhen Wang1,2,3
1Department of Radiology, The First Affiliated Hospital of Anhui Medical University, Hefei, Anhui, China.

Background:
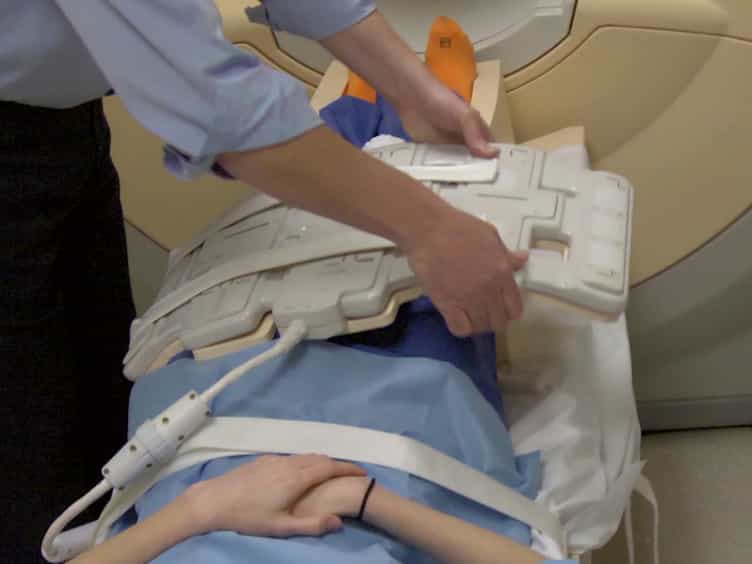
Cardiac magnetic resonance elastography (MRE) is a non-invasive technique that quantifies myocardial stiffness by tracking shear wave propagation through the heart. Shear waves are generated externally and delivered to the thorax through a passive driver placed on the chest. Passive driver position is a critical yet underexplored determinant of measurement quality.
Purpose:
To compare two passive driver positions in 3.0 T cardiac MRE - the apical surface projection (ASP) and the left lateral chest wall (LCW) - and to determine which yields more reliable left ventricular (LV) myocardial stiffness measurements.
Methods:
Twenty-three healthy volunteers (mean age 43.0 ± 17.0 years; 14 men, 9 women) underwent two cardiac MRE acquisitions, with the passive driver placed first at the ASP and then at the LCW. LV myocardial stiffness and the octahedral shear strain signal-to-noise ratio (OSS-SNR) were measured at both positions. Differences between positions were analyzed using paired t-tests with Cohen's d. Inter- and intra-observer reproducibility were assessed using intraclass correlation coefficients (ICC) and Bland-Altman analysis.
Results:
Myocardial stiffness was significantly lower at the ASP than at the LCW (9.0 ± 1.7 kPa vs. 14.7 ± 3.0 kPa; mean difference -5.8 kPa, 95% CI -7.2 to -4.3; ; Cohen's ). OSS-SNR was significantly higher at the ASP (1.72 ± 0.48 vs. 1.25 ± 0.29; ; Cohen's ). At the ASP, stiffness measurements demonstrated excellent intra- and inter-observer agreement, with ICCs of 0.962 and 0.963, respectively. At the LCW, stiffness measurements demonstrated good inter-observer agreement and excellent intra-observer agreement, with ICCs of 0.839 and 0.914, respectively.
Conclusion:
Passive driver placement at the ASP resulted in significantly higher OSS-SNR and superior reproducibility for LV myocardial stiffness measurements compared with LCW placement. Therefore, the ASP should be considered the preferred driver position for cardiac MRE in clinical and research settings.