Related Experiment Video
Updated: Oct 28, 2026
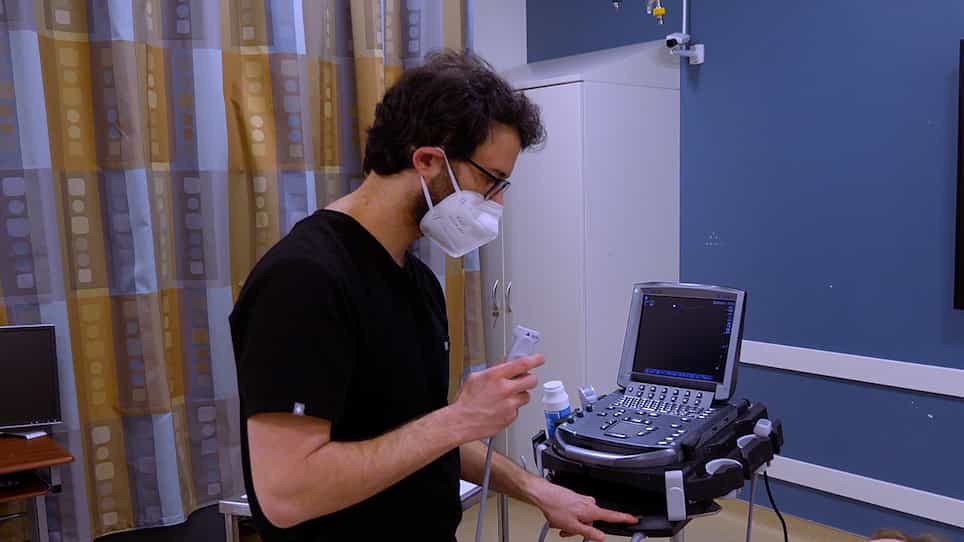
Point-of-Care Lung Ultrasound in Adults: Image Acquisition
Published on: March 3, 2023
Ultrasound-derived mean grayscale intensity for predicting malignant pleural effusion: A prospective study
Banu Kahriman1, Furkan Atasever1, Güliz Kizir1
1Department of Pulmonology, Yedikule Chest Disease and Chest Surgery Training and Research Hospital, Istanbul, Türkiye.

Background:
Early recognition of malignant pleural effusion is important for prognosis and treatment planning. Quantitative, noninvasive imaging parameters may aid in diagnosing pleural malignancy. This study investigated the diagnostic value of mean grayscale intensity (MGI) measurements obtained from thoracic ultrasound images for differentiating benign and malignant pleural effusions.
Methods:
In this prospective observational study, 101 patients with pleural effusion were enrolled. MGI measurements were performed on stored thoracic ultrasound images using ImageJ software. Patients were classified as having benign or malignant pleural effusion based on cytological and/or histopathological findings or, in patients without pathological confirmation, two negative pleural fluid cytology examinations, the absence of additional clinical or radiological findings suggestive of malignancy, and regression of the pleural effusion during follow-up. Independent predictors of malignant pleural effusion were evaluated using multivariable logistic regression analysis, and diagnostic performance was assessed using receiver operating characteristic (ROC) curve analysis.
Results:
Among the 101 patients, 59 had benign pleural effusion and 42 had malignant pleural effusion. The median MGI was significantly higher in malignant than in benign pleural effusions (21 vs. 18, P = 0.03). In multivariable logistic regression analysis, MGI remained independently associated with malignant pleural effusion (odds ratio: 1.052, 95% confidence interval [CI]: 1.003-1.103; P = 0.03). ROC analysis yielded an area under the curve of 0.62 (95% CI: 0.513-0.734). The optimal cutoff value was 24.25, with a sensitivity of 40.48% and a specificity of 79.66%.
Conclusion:
MGI values obtained from thoracic ultrasound images were significantly higher in malignant pleural effusions and remained independently associated with pleural malignancy. Although MGI should not be considered a standalone diagnostic tool, it may serve as a quantitative, noninvasive imaging parameter that complements clinical, radiological, and ultrasonographic assessment.
