Related Experiment Video
Updated: Oct 28, 2026
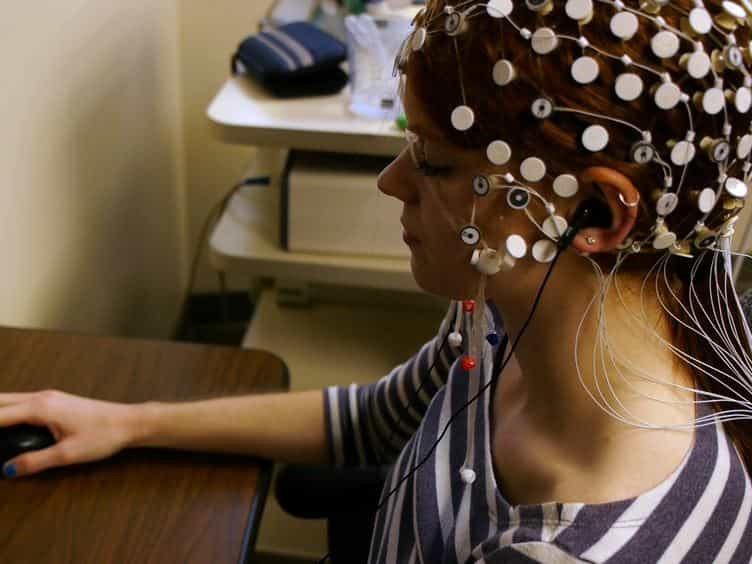
A Neuroscientific Approach to the Examination of Concussions in Student-Athletes
Published on: December 8, 2014
Functional Cognitive Disorder and Post-Concussion Memory Symptoms as Disorders of Distributed Memory Control: A
Ioannis Mavroudis1,2,3, Oindrila Das4, Foivos Petridis3
1Department of Neuroscience, Leeds Teaching Hospitals NHS Trust, Leeds LS1 3EX, UK.

Abstract:
Background: Memory problems are amongst the most troublesome and least understood of the symptoms in functional cognitive disorder (FCD) and in persistent post-concussion symptoms (PPCS). Standard neuropsychological testing typically shows only minor objective deficits, which results in a clear mismatch between the level of subjective distress and the actual degree of impairment. Current explanations of this discrepancy either attribute it to undetected hippocampal storage failure or regard it as a non-specific functional overlay; we believe that both of these explanations are incomplete. Methods: This is a narrative review incorporating an integrative hypothesis, not a systematic review. The literature was found using searches of databases and by tracing citations, and the sources were chosen on the basis of their conceptual relevance rather than according to a comprehensive protocolMethods of Literature Selection. The following three types of claims are distinguished throughout: those findings which have been established empirically in humans, those which are based on animal studies, and the hypotheses put forward in this paper. Results: Current evidence shows that episodic memory is spread out over a hippocampal-entorhinal-prefrontal-anteromedial thalamic-cortical control system, with the anteromedial thalamus being responsible for deciding which traces are stabilised and the prefrontal areas providing support for retrieval and for metacognitive evaluation. We suggest that the memory symptoms in both cases are due to a malfunction of this control system rather than to a failure of storage. In the case of FCD, entry is thought to occur in a top-down manner via abnormally precise priors of cognitive failure, impaired global metacognition, hypervigilant self-monitoring and overfitting of the self-model. With regard to PPCS, entry is believed to take place in a bottom-up way as a result of a real neurometabolic and network injury, after which fatigue, sleep disruption and hypermonitoring keep the symptoms going; in susceptible individuals, a concussion may serve as a gateway to FCD. Maladaptive, use-dependent plasticity is proposed as the common underlying mechanism. Conclusions: A unified framework incorporating metacognitive and systems consolidation processes is able to explain the discrepancy and makes eight predictions that can be tested together with provisional criteria for the transition from a primary-FCD to an organic-PPCS. The framework is put forward for future testing rather than being presented as a fully established explanation.

Related Concept Videos
 01:14
Role of Cerebellum and Prefrontal Cortex in Memory
 01:26
Higher Mental Functions of Brain: Learning and Memory
 01:27
Dissociative Disorders
Dissociative Fugue
A hallmark feature of dissociative disorders is the dissociative fugue...
 01:16
Interference and Decay
Interference occurs when competing memories hinder the retrieval of particular information. It can be classified into two types: proactive and retroactive interference. Proactive...
 01:13
Amnesia
The severity and duration of memory loss vary depending on the type and underlying cause. Amnesia is classified into two main types: retrograde and anterograde.
Retrograde amnesia is marked by the loss of memories formed before the onset of the condition. Patients may recall distant past events but often forget those occurring shortly before the incident.
Anterograde...
 01:21
Dissociative Amnesia