Related Experiment Video
Updated: Oct 28, 2026

Mouse Model of Oleic Acid-Induced Acute Respiratory Distress Syndrome
Published on: June 2, 2022
Oxidative Stress and Alveolar-Capillary Barrier Failure in Sepsis- and Severe Acute Pancreatitis-Associated ARDS
Sophia Rusch1, Patricia Mester1, Fabian Möller1
1Department of Internal Medicine I, Gastroenterology, Hepatology, Endocrinology, Rheumatology, Immunology, and Infectious Diseases, University Hospital Regensburg, 93053 Regensburg, Germany.

Abstract:
Acute respiratory distress syndrome (ARDS) is the final common phenotype of diverse insults, but the route to alveolar-capillary barrier failure matters. Sepsis and severe acute pancreatitis provide an informative contrast: sepsis begins with infection and pathogen-associated molecular patterns, whereas pancreatitis is initially driven by sterile acinar-cell injury, necrosis and damage-associated molecular patterns, before infected necrosis can superimpose sepsis biology. These differences are clinically relevant since they determine whether redox-related signals must be interpreted in the context of pathogen burden and antimicrobial host defense or of initially sterile necrosis with subsequent risk of infected necrosis. In this review, we discuss how these distinct pathophysiological contexts engage NADPH oxidase (NOX)-derived oxidants, mitochondrial reactive oxygen species, reactive nitrogen species (RNS), lipid peroxidation, regulated cell death and impaired antioxidant defenses. We focus on the pulmonary endothelium and epithelium as compartments in which inflammatory and redox signals converge to disrupt barrier integrity, impair alveolar fluid clearance and promote immunothrombosis. We also discuss coronavirus disease 2019 (COVID-19)-associated ARDS as a viral comparator, the analytical limitations of redox biomarkers, and the value of serial, compartment-aware measurements. The central message is that oxidative stress is not a single systemic deficiency that can be corrected by generic antioxidants. Its biological and therapeutic significance depends on oxidant source, cellular compartment, microbial burden and disease phase. However, evidence for many specific redox pathways remains predominantly preclinical, and their clinical relevance requires further validation. At present, no validated redox-directed treatment-selection strategy exists; future approaches will therefore require validated target-engagement markers and phenotype- and time-specific trial designs.

Related Concept Videos
 01:30
Acute Respiratory Failure-III
 01:21
Acute Pancreatitis II: Pathophysiology
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include:
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Inflammation
 01:23
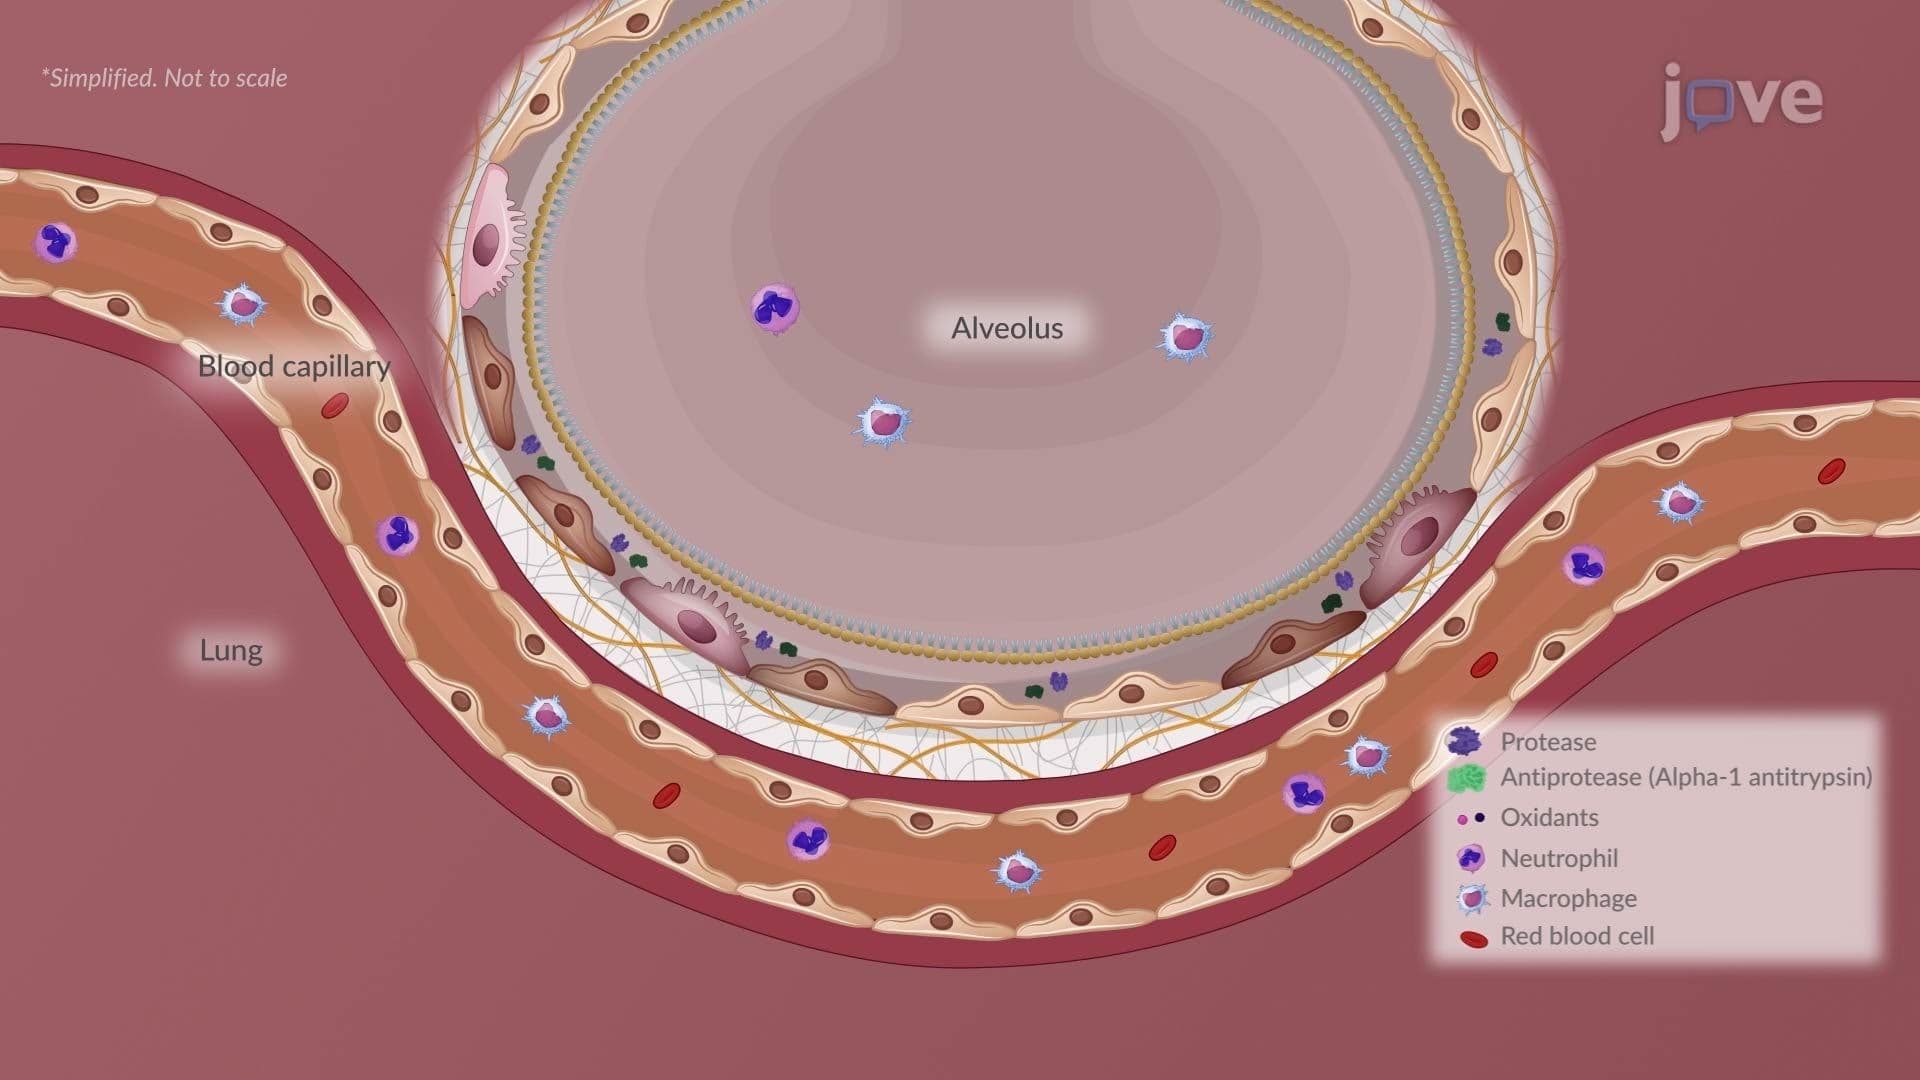
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:21
Chronic Pancreatitis II: Pathophysiology