Related Experiment Video
Updated: Oct 28, 2026
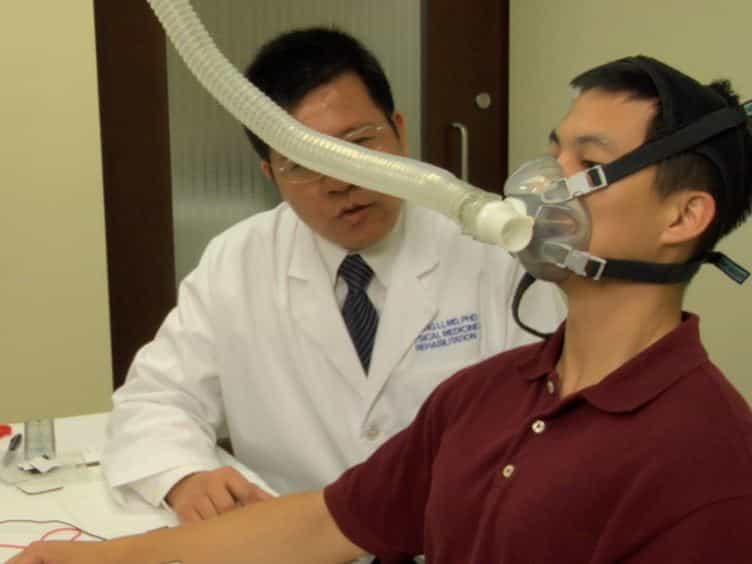
Breathing-controlled Electrical Stimulation (BreEStim) for Management of Neuropathic Pain and Spasticity
Published on: January 10, 2013
Baclofen for Spasticity in Multiple Sclerosis: A Comprehensive Narrative Review
1Elixa MediScience Ltd., 24-28 Brockenhurst Road, Ascot, Berkshire SL5 9DL, UK.

Abstract:
Baclofen, a GABA-B receptor agonist developed as an anticonvulsant in the 1960s and repurposed for spasticity in the 1970s, is recommended as a first-line oral treatment for spasticity in multiple sclerosis (MS) by UK NICE guidance and is used similarly, though not necessarily designated identically, in many other jurisdictions. It acts at two sites within the spinal stretch reflex arc: presynaptically on Ia afferent terminals in the dorsal horn, where it reduces excitatory neurotransmitter release, and postsynaptically on ventral horn interneurons and α-motoneurons, where it hyperpolarises the cell and suppresses firing. Only a small fraction of an oral dose crosses the blood-CNS barrier, so oral dosing requires high systemic doses that cause sedation, ataxia and CNS depression. Intrathecal delivery bypasses the barrier, allowing a much lower dose and fewer brain-mediated side effects. Other drawbacks include a short, variable half-life, GABA-B receptor downregulation contributing to adverse effects and intrathecal tolerance, and withdrawal that has proved fatal. The narrow efficacy-to-side-effect margin is probably intrinsic to GABA-B receptor activation. This narrative review covers baclofen's neuroanatomy, pharmacokinetics, administration routes, efficacy, comparators, long-term outcomes, interactions, special populations, and regulatory history. Long-term follow-up shows durable control without worsening sedation, but the one study using validated quality-of-life measures found no significant improvement despite clear spasticity reduction. Weighing benefit against harm, this review concludes that baclofen offers a net benefit, but conditionally: only for carefully selected, individually titrated, and actively monitored patients. Because this is a narrative rather than systematic review, source selection was not governed by a prespecified protocol, some clinical estimates rely on secondary or aggregate data, and the underlying literature is heterogeneous in design and quality.
Related Concept Videos
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:28
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
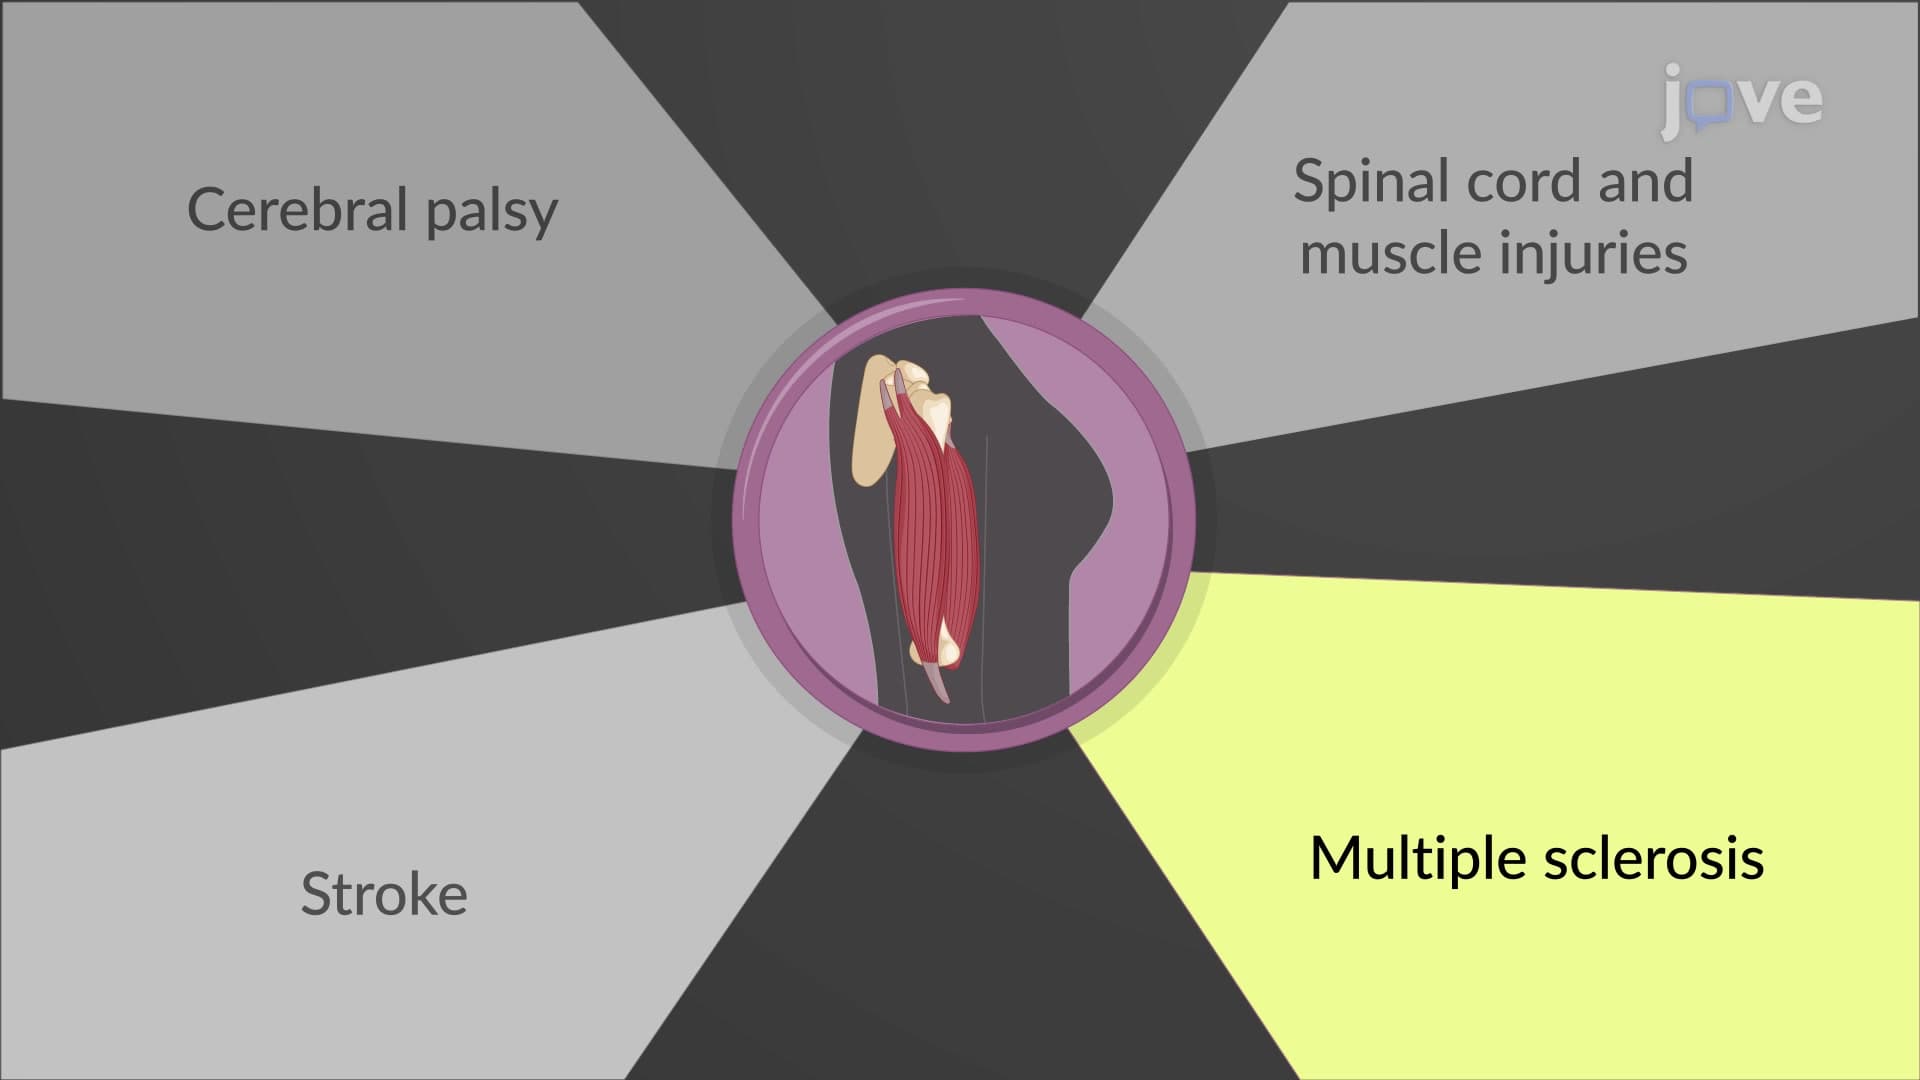
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...
 01:29
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also promote...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:19
Multiple Sclerosis l: Introduction