Organ Malperfusion and Mortality in Acute Type 1 Aortic Dissection with Iliac Extension: A Retrospective Single-Center Study Focused on Mesenteric Malperfusion and the Source-Clearance Hypothesis
Related Experiment Video
Updated: Oct 28, 2026
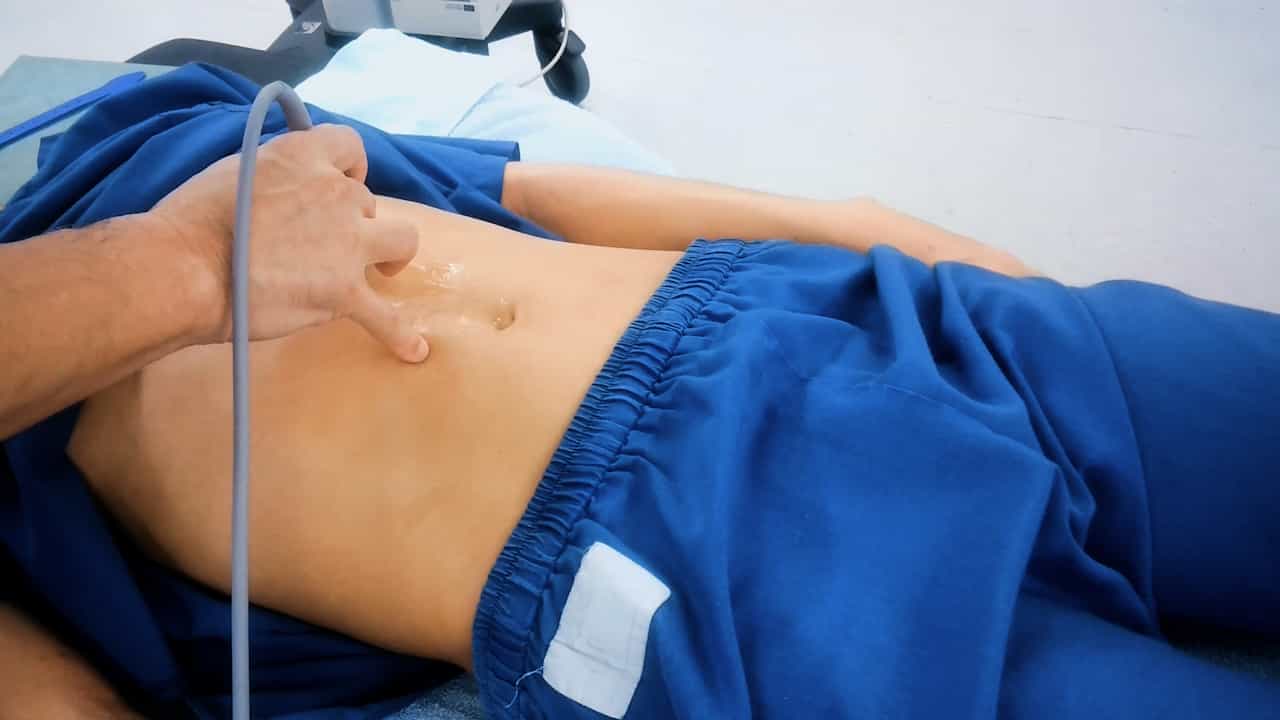
Multimodality Diagnosis of Mesenteric Ischemia
Published on: July 21, 2023
1Department of Cardiovascular Surgery, Bursa City Hospital, Bursa Faculty of Medicine, University of Health Sciences, 16110 Bursa, Türkiye.

Abstract:
Background/Objectives: Mesenteric malperfusion is the most lethal and least recognizable complication of acute type A aortic dissection. This study aimed to examine organ-specific malperfusion patterns and 30-day mortality in acute type 1 aortic dissection with iliac extension, and to evaluate whether the lactate-to-albumin ratio (LAR) and superior mesenteric artery (SMA) origin pattern add predictive value for mesenteric malperfusion syndrome within a "source-clearance" framework. Methods: In this retrospective single-center study, 80 consecutive patients with acute type 1 aortic dissection extending to the iliac arteries who underwent surgical repair between January 2020 and March 2026 were reviewed. Malperfusion (preoperative finding) and malperfusion syndrome (end-organ injury persisting despite central repair) were defined for six organ systems; visceral branch origin and planimetric true lumen ratio were assessed on computed tomography angiography (CTA). The primary endpoint was 30-day mortality. Results: Thirty-day mortality was 33.8%; 60% of patients had malperfusion, and mortality rose with the number of organs involved (0/1/≥2: 12.5%/32.1%/70.0%). Mesenteric malperfusion (n = 21) carried the highest mortality (71.4%); all nine patients who developed mesenteric syndrome died. Cerebral malperfusion was most frequent (n = 27); all nine who improved postoperatively survived, whereas mortality was 81.8% in the 22 who developed the syndrome. Preoperative shock or cardiopulmonary resuscitation (CPR) (odds ratio [OR] = 7.02), mesenteric malperfusion (OR = 6.24), LAR (OR = 1.07 per 0.01 unit) and Glasgow Coma Scale (GCS; OR = 0.75 per point) were independent predictors. LAR and SMA origin pattern were uncorrelated (r = -0.04) and together raised the area under the receiver operating characteristic curve (AUC) for mesenteric syndrome from 0.861 to 0.955; mortality was 75% with mixed SMA origin (n = 8). Conclusions: Malperfusion is a dose-dependent risk spectrum; mesenteric involvement is its most lethal component, increasing mortality six-fold independently of hemodynamic and metabolic status. Joint interpretation of LAR and SMA origin pattern offers a practical, validation-pending framework for perioperative management of the mesenteric circulation in centers without a hybrid operating room.
More Related Videos
 06:50
A Model of Acute Lung Injury Following Visceral Ischemia-Reperfusion by Supra-Coeliac Aortic Cross Clamping in Rats
Published on: August 15, 2025
 04:57
Controlled Reversible Visceral Arterial Ischemia, Venous Congestion and Combined Malperfusion via Midline Laparotomy in Rats
Published on: July 5, 2024