Related Experiment Video
Updated: Oct 28, 2026

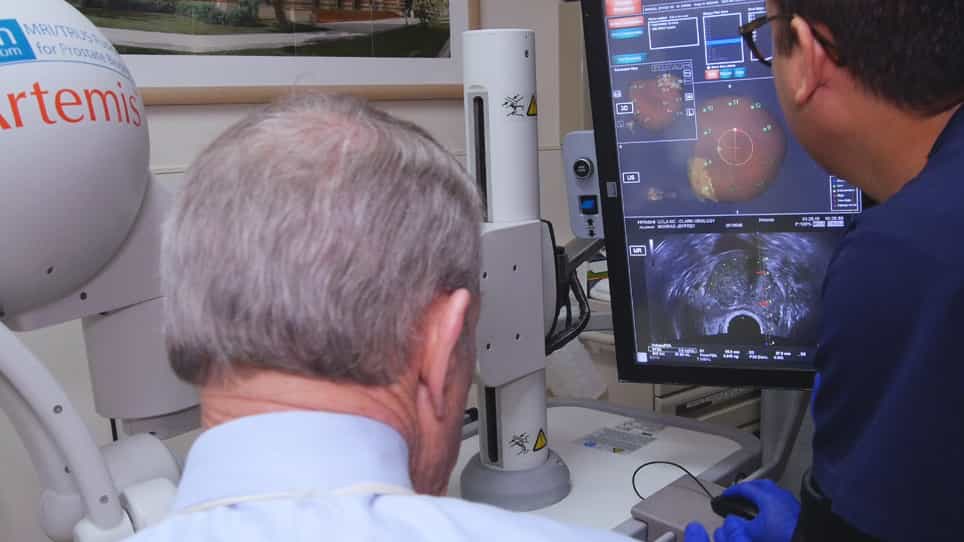
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
External Validation of MRI-Based Prostate Cancer Risk Calculators in a Contemporary Pre-Biopsy mpMRI Cohort
Hubert Grießner1, Sarah K Luck1, Julia K Peters1
1Department of Urology, Paracelsus Medical University Salzburg, 5020 Salzburg, Austria.

Abstract:
Background: Multiparametric MRI (mpMRI)-integrated risk calculators may improve individualized prediction of clinically significant prostate cancer (csPCa) before biopsy. We externally validated and directly compared the MRI-based Radtke and Alberts risk calculators (Radtke-RC and Alberts-RC) in a contemporary MRI-selected biopsy cohort, assessing discrimination, calibration, and clinical utility. Methods: Consecutive patients undergoing pre-biopsy mpMRI followed by combined MRI-targeted and systematic biopsy were retrospectively identified. The primary endpoint was csPCa, defined as ISUP Grade Group ≥ 2. Discrimination was assessed using receiver operating characteristic analysis, calibration using observed-to-expected (O:E) ratios, calibration-in-the-large (slope fixed at 1), calibration slopes, and calibration plots, and clinical utility using decision curve analysis. Radtke-RC validation was restricted to biopsy-naïve patients, while head-to-head comparisons were restricted to biopsy-naïve patients evaluable for both calculators. Threshold probabilities of 12%, 20%, and 30% were examined, with bootstrap confidence intervals for incremental net benefit. Results: Of 171 screened patients, seven had no evaluable biopsy outcome. The Radtke-RC validation cohort comprised 144 biopsy-naïve patients, including 55 (38.2%) with csPCa. The Alberts-RC was evaluable in 114 patients; 50 patients could not be assessed because age, prostate volume, or PSA values were outside the online calculator's permitted input ranges. The common biopsy-naïve cohort comprised 97 patients, including 34 (35.1%) with csPCa. In the model-specific cohorts, AUCs were 0.765 (95% CI 0.682-0.848) for the Radtke-RC and 0.767 (95% CI 0.672-0.861) for the Alberts-RC. In the common cohort, AUCs were 0.774 (95% CI 0.672-0.875) and 0.768 (95% CI 0.661-0.874), respectively, with no statistically significant paired difference (0.006, 95% CI -0.028 to 0.040; p = 0.726). Calibration differed substantially: the Radtke-RC overpredicted risk (mean predicted risk 48.2%; O:E 0.727), whereas the Alberts-RC underpredicted risk (18.0%; O:E 1.944). At thresholds of 12%, 20%, and 30%, the Radtke-RC classified zero, seven, and 25 patients below threshold and missed zero, zero, and four csPCa cases, respectively; corresponding values for the Alberts-RC were 42, 64, and 78 patients below threshold, with seven, 12, and 20 csPCa cases missed. Sensitivity analyses indicated less favourable Radtke-RC decision-analytic performance outside the common cohort, whereas restriction to PI-RADS 4-5 patients did not materially alter relative discrimination. Conclusions: No statistically significant difference in discrimination between the Radtke-RC and Alberts-RC was detected, although the study was not powered to establish equivalence. Despite similar discrimination, the calculators showed substantially different calibration and threshold-specific clinical consequences. In this MRI-selected population, interpretation of fixed risk thresholds should therefore account for calibration, patient selection, and the trade-off between biopsy avoidance and missed csPCa.