Related Experiment Video
Updated: Oct 28, 2026
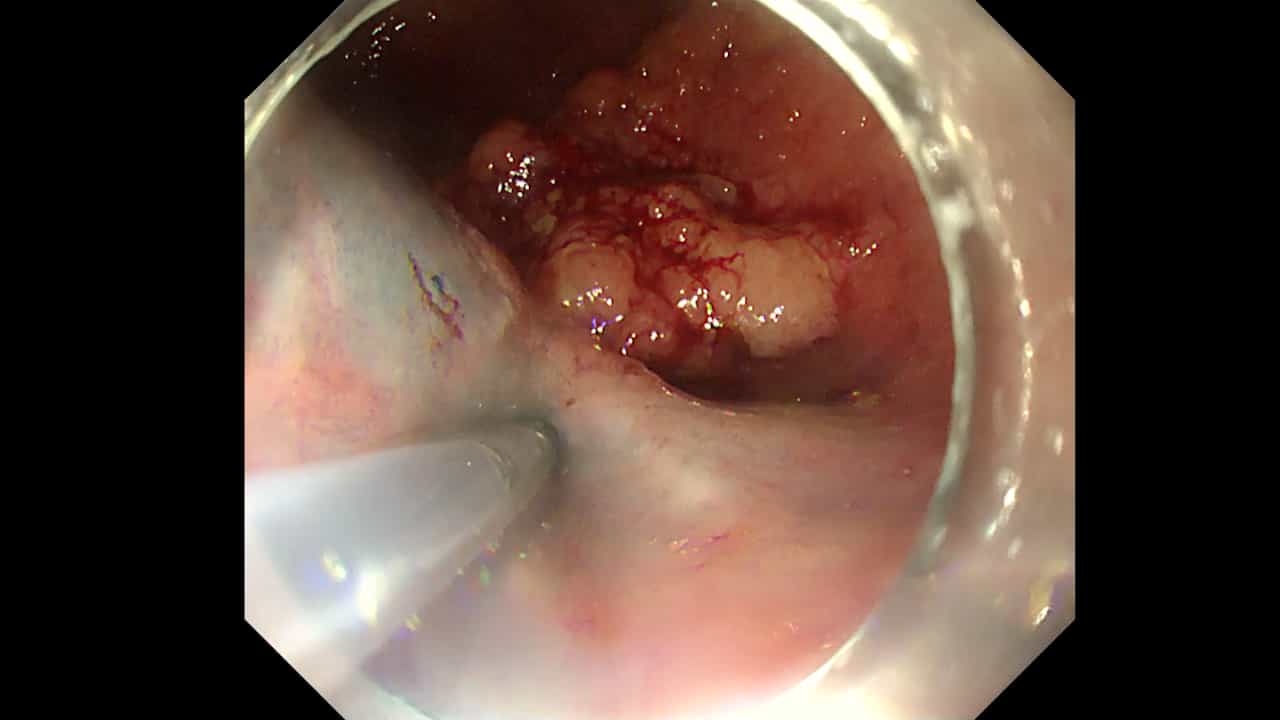
The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Undersaline ESD for Large Colorectal Lesions: A Narrative Review
Rodolfo Augusto Assis Rezende1,2, Roberto de Sire1,2, Antonio Di Martino1,2
1Endoscopy Unit, Gastroenterology Department, IRCCS Humanitas Research Hospital, Via Alessandro Manzoni 56, 20089 Rozzano, Italy.

Abstract:
Endoscopic submucosal dissection (ESD) is the standard of care for the en bloc resection of large colorectal lesions but remains technically demanding, with long procedure times, a steep learning curve, and complication rates that have constrained adoption outside expert Eastern centres. Undersaline ESD (UESD) has emerged as a modification in which gas insufflation is replaced by immersion in isotonic saline, exploiting the distinct physical properties of a liquid-filled lumen to address several limitations of the conventional technique. Although frequently described as "underwater" ESD, the term "undersaline ESD" is more precise, since its advantages derive specifically from the ionic content of saline rather than from submersion alone. This narrative review synthesises the mechanistic rationale and the accumulating clinical evidence on UESD for large colorectal lesions. Saline immersion alters monopolar electrosurgical behaviour towards a coagulation-dominant profile, generates intrinsic traction on the mucosal flap through differential buoyancy, magnifies the dissection plane, and dissipates thermal energy. Across observational series and two recent meta-analyses, UESD is associated with faster submucosal dissection without compromising en bloc resection, R0 resection or short-term safety. The randomised evidence is not uniform: two of three trials reported faster dissection, while the largest found no difference in its primary endpoint, with lesion position determining the relative advantage of each technique. The benefits appear concentrated in specific settings such as submucosal fibrosis, gravity-side lesions, and, on preliminary data, non-expert operators, rather than distributed across all procedures. Key evidence gaps include the East Asian concentration of randomised data, the heterogeneity of technical implementation, and an absence of long-term oncological outcomes.