Related Experiment Video
Updated: Oct 28, 2026
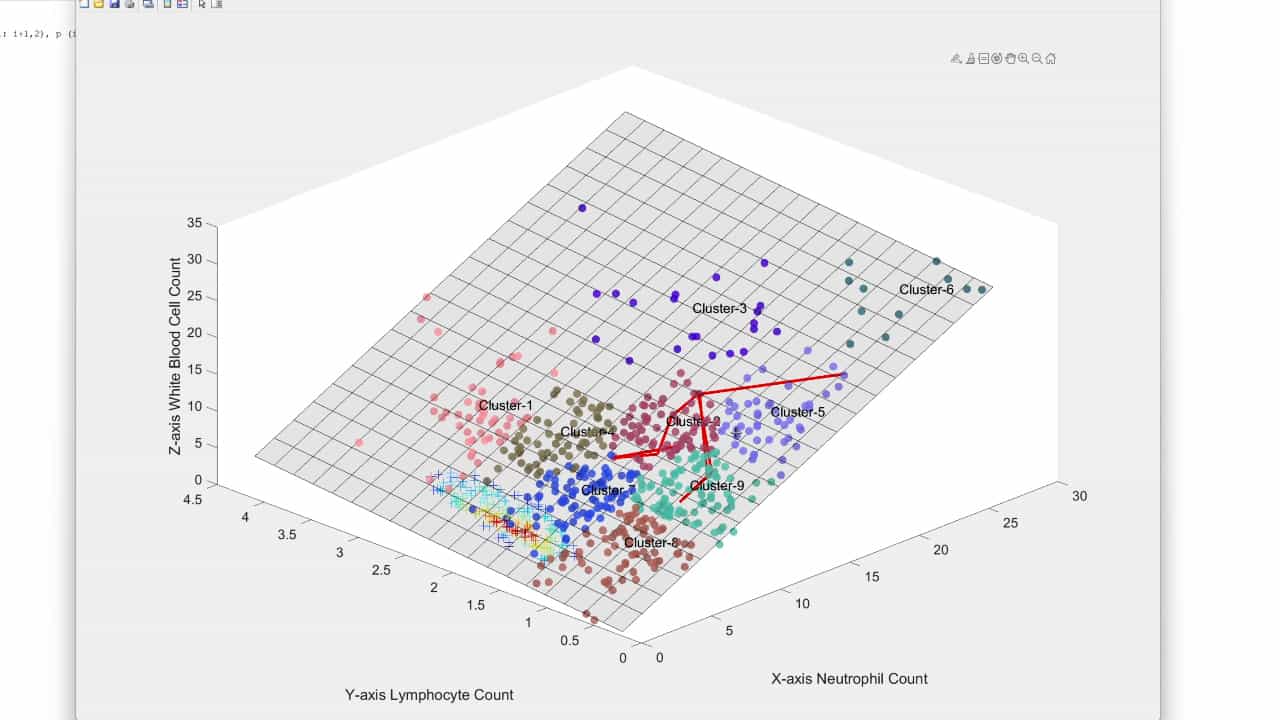
A Data-Driven Approach to Quantifying Immune States in Sepsis
Published on: February 7, 2025
Cell Type- and Phase-Dependent Immune Checkpoint Targeting in Sepsis: TIM-3 as a Model for Precision Immunomodulation
Jialiu Luo1, Peidong Zhang1, Shuaipeng Gu1
1Department of Trauma Surgery, Emergency Surgery & Surgical Critical, Tongji Trauma Center, Tongji Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430030, China.

Abstract:
Sepsis is a dysregulated host response in which hyperinflammation, immunoparalysis, lymphoid depletion, myeloid dysfunction, tissue injury and defective pathogen control frequently coexist and evolve over time. Immune checkpoint pathways have therefore attracted interest as candidates for immune restoration, but receptor upregulation alone is an unreliable therapeutic signal. This review develops a cell type- and phase-dependent framework for immune checkpoint targeting in sepsis, using TIM-3 as a model checkpoint node. We first discuss the conceptual pitfalls in translating checkpoint blockade from cancer and chronic infection to acute heterogeneous sepsis. We then examine why the immune phase should be defined by dynamic host response states rather than by the clock time and why checkpoint signals must be interpreted according to their cellular source, including effector lymphocytes, NKT cells, CD4+ T cells, monocytes/macrophages, dendritic cells and suppressive myeloid populations. TIM-3 illustrates this complexity. In sepsis-relevant studies, TIM-3 has been linked to NKT cell and hepatic CD8+ T-cell apoptosis, CD4/HMGB1/TIM-3-associated hyporesponsiveness, Galectin-9-related ligand effects and potential myeloid or tissue-resident functions involving phosphatidylserine-positive debris, extracellular vesicles and tissue homeostasis. These observations argue against treating TIM-3 as a single-purpose inhibitory receptor or assuming that antibody blockade, ligand administration, receptor mutation and Galectin-glycan interference perturb the same biology. We propose that future checkpoint-directed studies should enroll immune states rather than syndromic sepsis alone; integrate the inflammatory burden, innate immune competence, lymphoid function and ligand context; and prioritize mechanistic endpoints such as lymphocyte apoptosis, IFN-γ recovery, monocyte HLA-DR restoration, LPS-induced TNF responses, bacterial clearance and secondary infection. Future precision immunomodulation studies in sepsis should evaluate defined checkpoint-associated circuits rather than infer therapeutic relevance from receptor expression alone.


