Related Experiment Video
Updated: Oct 29, 2026
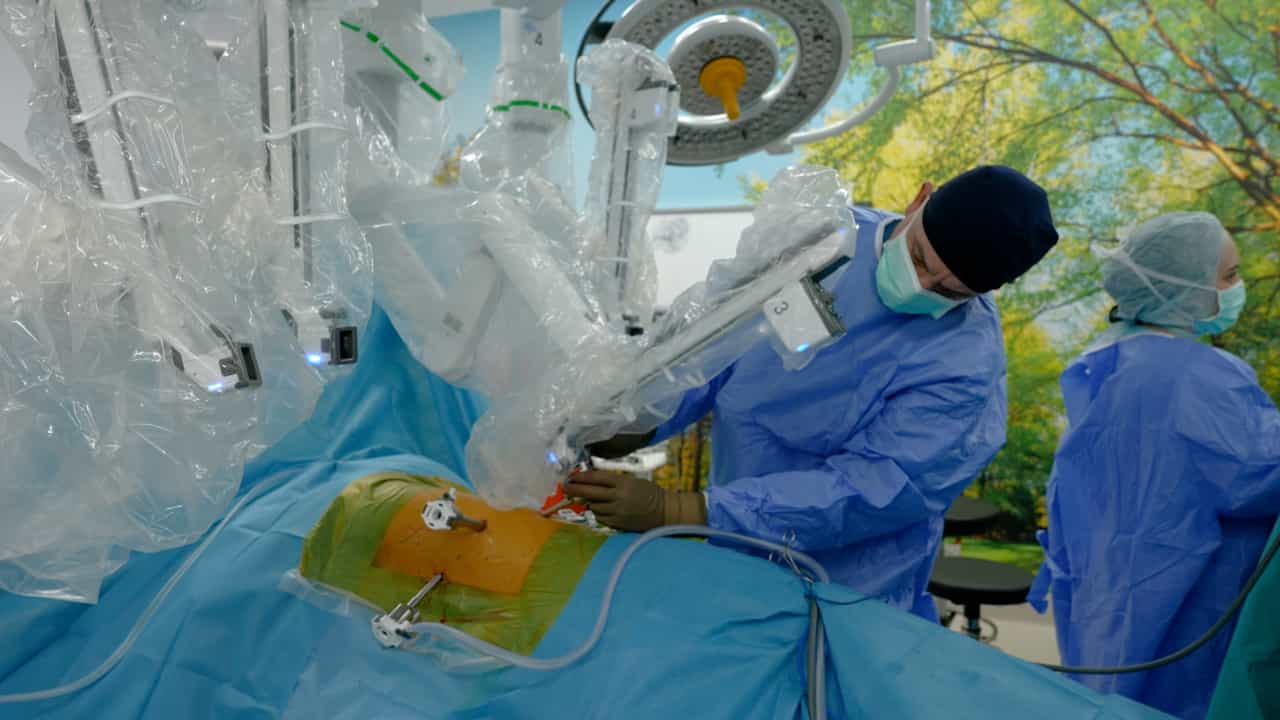
Subcostal Specimen Removal in Completely Portal Robotic Lobectomy
Published on: April 19, 2024
Body mass index and textbook outcome after robotic liver resection: A multinational cohort study across 30 centers
Zhihao Li1, Dimitri Aristotle Raptis2, Yong Ma3
1Department of Surgery and Transplantation, University of Zurich, Zurich, Switzerland; Division of Transplant Surgery, The William J. Von Liebig Center for Transplantation and Clinical Regeneration, Mayo Clinic, Rochester, MN.

Background:
Obesity is associated with worse outcomes after open and laparoscopic liver resection, but its independent contribution after robotic liver resection has not been formally interrogated in a large cohort. This study aims to determine whether body mass index predicts textbook outcome after robotic liver resection.
Methods:
Consecutive adult patients undergoing robotic liver resection at 30 international high-volume benchmark centers (2020-2023) were analyzed. Living donor hepatectomies were excluded from the primary analysis. The primary outcome was textbook outcome. Generalized estimating equations with center as the cluster provided cluster-robust standard errors for all multivariable models. Sensitivity analyses reincluded living donors, applied Asia-Pacific body mass index cut points, and restricted to high-contributing centers.
Results:
Among 2,905 nondonor patients (normal: 1,263; overweight: 1,007; obese: 427; and morbidly obese: 208) across 29 centers, the overall non-textbook outcome rate was 22.0% and differed little across body mass index strata unadjusted (19.6%, 24.2%, 23.0%, and 23.6%; P = .05). Center-level variation was substantial. After adjustment, body mass index was not an independent predictor (per 1 kg/m2, odds ratio, 1.00; 95% confidence interval, 0.98-1.02; P = .81; morbidly obese versus normal: odds ratio, 1.01; 95% confidence interval, 0.68-1.51; P = .96), and adding body mass index to the multivariable model left discrimination unchanged (area under the curve, 0.699 with and without body mass index). Dominant determinants of non-textbook outcome were malignant indication (odds ratio, 2.45, 1.70-3.52; P < .001), major hepatectomy (odds ratio, 1.57, 1.24-1.97; P < .001), and neoadjuvant therapy (odds ratio, 1.36; 1.13-1.63; P = .001). Higher body mass index showed a nonsignificant trend toward increased surgical site infection (odds ratio per 5 kg/m2, 1.18, 0.99-1.41; P = .06) but no association with major complications. Findings were robust across all sensitivity analyses, including reinclusion of the 1,180 living donors. No body mass index × IWATE interaction was detected (P = .82).
Conclusion:
Among patients selected for robotic liver resection at experienced centers, body mass index was not an independent determinant of textbook outcome or of major complications. Surgical complexity, indication, and extent of resection were the dominant drivers of perioperative outcome. These findings are conditional on a robotic approach having been offered and do not address the upstream choice between robotic, laparoscopic, and open surgery.